Introduction
The palliative care is “an approach that promotes the improvement of the quality of health of patients (adults and children) and their families facing problems associated with life-threatening issues. It prevents and alleviates suffering through early identification, correct assessment, and treatment of pain and other problems, whether physical, psychosocial, or spiritual.”1 The World Health Organization also argues that addressing suffering requires addressing issues beyond physical symptoms and is a human right explicitly recognized in the field of health. In addition, palliative care should be provided in integrated, person-centred health services, where special attention is given to the specific needs and preferences of individuals.
Spirituality is an intrinsic dimension of human beings, which means that attention and care in this dimension when accompanying people in palliative care requires a specific amount of space and time, as well as specific training, in order to respond to the challenge in a responsible and mature manner.
According to the initial research, this literature review is the only one of qualitative studies that explores the experiences, perspectives, and perceptions of healthcare professionals regarding the provision of spiritual care in palliative care.
Although, there are master’s theses and studies of spirituality in palliative care but the majority identify spirituality with religiosity/religious care and essentially explore the role of chaplains, there are also some studies and research on specific categories of spirituality such as hope, dignity, compassion, among others.2–4
There is still no concerted approach to spirituality in palliative care, as there is no consensus on how to address this issue in palliative care, which is often left out of clinical intervention, even though there are some studies and definitions. The most recent consensus of what Spirituality is from the Pulchalski group.
Although there is no consensus on how to evaluate and to address the existential suffering. As so the spiritual care is left out of the responses in palliative care and, in many cases, spirituality is only addressed through prayer, requests for assistance from a spiritual leader by the patient themselves, and also through the presence of volunteers in some cases.
Due to the inherent dignity of human beings and their inalienable rights, Spirituality is an integral part of Ethics. As a dimension of relationship with transcendence, is an ontological condition of human beings, it cannot be avoided at a time of extreme vulnerability, such as illness or a life-threatening health condition, or even proximity to death. Welcoming, knowing, and promoting the spiritual dimension of the person is essentially respecting each life in its potential for fulfilment, respecting its autonomy, continuing to have its choice; it is an act of doing good, of benefaction, and above all, of avoiding any and all avoidable harm, of non-maleficence. And of justice, giving each person what they need and require at each moment of their life. Since spirituality concerns the integrity of the person and since, in palliative care, we seek not only person-centred care but also the Aristotelian maxim of realizing the maximum of values in the course of one’s life, we are compelled and committed to offering a comprehensive response to the transcendent dimension of the human being. We are also aware that suffering can arise from a spiritual and existential component, which can manifest itself, in some cases, with refractory symptoms. In order to do that it is urgent to investigate and to look for a concerted answer for the existential and spiritual suffering that has a great imprint in the last walk in this earth.
The aim of this review is to understand the experiences, perspectives, and perceptions of healthcare professionals in providing spiritual care to adults in palliative care.
Method
Study design
This literature review followed the Joanna Briggs Institute (JBI) methodology for qualitative reviews of scientific evidence, and we considered meta-aggregation for the synthesis of findings.5,6
Eligibility criteria
Participants
Healthcare professionals, such as doctors, nurses, physical therapists, psychologists, social workers, among others, in a palliative care context, who had experience providing spiritual care to sick adults (aged 18 or older).
Phenomenon of interest
Experiences, perspectives, or perceptions of healthcare professionals when providing spiritual care in the context of palliative care.
Context
Any palliative care context, at home or in a clinical setting, such as palliative care units, hospices, hospitals, and home care, but not limited to these.
Type of studies
Qualitative studies, such as phenomenological, ethnographic, grounded theory, or descriptive studies that focus on the phenomenon, although it was not limited to these. Studies published in English, Portuguese, and Spanish were included, with no time limit.
Selection of studies
Following the search, all citations were entered into EndNote v. X7 (Clarivate Analytics, PA, USA). Duplicates were eliminated. Subsequently, eligible citations were entered into the Rayyan platform and a new analysis was performed, again eliminating some duplicates that had not been automatically identified by the bibliographic manager. Subsequently, the author of this dissertation read the titles and abstracts, including studies that met the inclusion criteria. Finally, the author of this dissertation read the full text of the included articles, eliminating all those that did not meet the inclusion criteria. In both phases of analysis (title/abstract and full text), in case of doubt on the part of the author of this dissertation, the same were discussed with the advisor of this dissertation and researchers with experience in systematic review.
Search strategy
A two-step strategy was used in this review.7
First, a preliminary search was conducted in Medline (via PubMed) to identify natural language words in the title and abstract, as well as indexed terms and descriptors. Second, the following databases were selected for the specific search: MEDLINE (via PubMed) and Scopus. The search for published studies was conducted on June 28, 2024 (
Table 1).
Table 1. Medline search term (via PubMed) and Scopus.
|
Medline (Pubmed)
|
Search results |
|---|
| ((((((Spiritual*[Title/Abstract]) OR ((“Spirituality”[Mesh]) OR “Spiritual Therapies”[Mesh])) AND (((((“Palliative Care”[Mesh]) OR “Terminal Care”[Mesh:NoExp]) OR “Hospice Care”[Mesh]) OR “Hospices”[Mesh]) OR (End-of-life [Title/Abstract] OR “end of life”[Title/Abstract] OR palliative [Title/Abstract] OR hospice*[Title/Abstract]))) AND (experience*[Title/Abstract] OR perspective*[Title/Abstract] OR perception*[Title/Abstract])) AND ((Qualitative [Title/Abstract] OR ethnograph*[Title/Abstract] OR phenomenol*[Title/Abstract] OR ethnonurs*[Title/Abstract] OR “grounded theory”[Title/Abstract] OR “grounded study”[Title/Abstract] OR “grounded studies”[Title/Abstract] OR “grounded research”[Title/Abstract] OR “grounded analysis”[Title/Abstract] OR “grounded analyses”[Title/Abstract] OR hermeneutic*[Title/Abstract] OR heuristic*[Title/Abstract] OR “action research”[Title/Abstract] OR “content analysis”[Title/Abstract] OR “thematic analysis”[Title/Abstract] OR “discourse analysis”[Title/Abstract] OR “focus group”[Title/Abstract] OR “focus groups”[Title/Abstract] OR “ethnological research”[Title/Abstract] OR ethnomethodolog*[Title/Abstract] OR interview*[Title/Abstract] OR emic [Title/Abstract] OR hermeneutics [Title/Abstract] OR heuristic*[Title/Abstract] OR semiotic [Title/Abstract] OR “lived experience”[Title/Abstract] OR “lived experiences”[Title/Abstract] OR discourse [Title/Abstract] OR “narrative analysis”[Title/Abstract]) OR ((((((“Qualitative Research”[Mesh]) OR “Interviews as Topic”[Mesh]) OR “Focus Groups”[Mesh]) OR “Narration”[Mesh]) OR “Personal Narrative” [Publication Type]) OR “Personal Narratives as Topic”[Mesh]))) NOT (((“Infant”[Mesh]) OR “Child”[Mesh]) OR “Adolescent”[Mesh])) NOT ((“Meta-Analysis” [Publication Type]) OR “Meta-Analysis as Topic”[Mesh] OR “Systematic Review” [Publication Type] OR “Systematic Reviews as Topic”[Mesh]) | 764 |
|
Scopus
| Resultados de pesquisa |
|---|
| (TITLE-ABS-KEY (spiritual*) AND TITLE-ABS-KEY (end-of-life OR “end of life” OR palliative OR hospice) AND TITLE-ABS-KEY (experience* OR perspective* OR perception*) AND TITLE-ABS-KEY (qualitative OR ethnograph* OR phenomenol* OR ethnonurs* OR “grounded theory” OR “grounded study” OR “grounded studies” OR “grounded research” OR “grounded analysis” OR “grounded analyses” OR hermeneutic* OR heuristic* OR “action research” OR “content analysis” OR “thematic analysis” OR “discourse analysis” OR “focus group” OR “focus groups” OR “ethnological research” OR ethnomethodolog* OR interview* OR emic OR hermeneutics OR heuristic* OR semiotic OR “lived experience” OR “lived experiences” OR discourse OR “narrative analysis”) AND NOT TITLE-ABS-KEY (“systematic review” OR “systematic reviews” OR meta-analysis) AND NOT TITLE-ABS-KEY (child* OR infant* OR adolescen* OR teen* OR pediatric* OR paediatric*)) AND (LIMIT-TO (LANGUAGE, “English”) OR LIMIT-TO (LANGUAGE, “Spanish”) OR LIMIT-TO (LANGUAGE, “Portuguese”)) | 875 |
Data extraction
The data were extracted from the studies included in this review by the author of this dissertation using a standardized instrument proposed by the JBI.8
The data extracted included specific details about the population, context, geographical location, phenomenon of interest, population, study method, and results relevant to the research question and objectives. The relevant findings from the included studies were extracted ipsi verbum with illustrations from participants to support and demonstrate the significance of the results. As the focus of this review was on healthcare professionals, only the experiences, perspectives, and/or perceptions of healthcare professionals were included. The findings were classified according to the JBI levels of credibility as unequivocal, credible, or unsupported; only unequivocal and credible findings were included in the final synthesis of results.5
Synthesis
The findings were grouped using the methods described in the JBI approach to qualitative studies of systematic reviews.5
This involved aggregating and synthesizing the findings to generate a set of statements representing this aggregation of findings; subsequently categorizing these findings based on similarity of meaning. Finally, these categories were subjected to a meta-synthesis to produce a set of synthesized findings that can be used as the basis for evidence-based practice.6
Results
Description of included studies
A total of 1,639 articles were identified in the databases used, of which 566 were removed because they were duplicates. Next, the titles and abstracts of the remaining 1,073 were analysed, with 81 being eliminated because they were duplicates and 972 excluded because they did not meet the inclusion criteria for the current research. Subsequently, after analysing the full text of the twenty selected articles, 16 were excluded because they did not meet the inclusion criteria; finally, the four selected studies were subjected to a careful analysis to obtain significant results for the current research. This process can be found in the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA)8 flow diagram (
Figure 1), which describes the research results and the process of selecting and including studies.
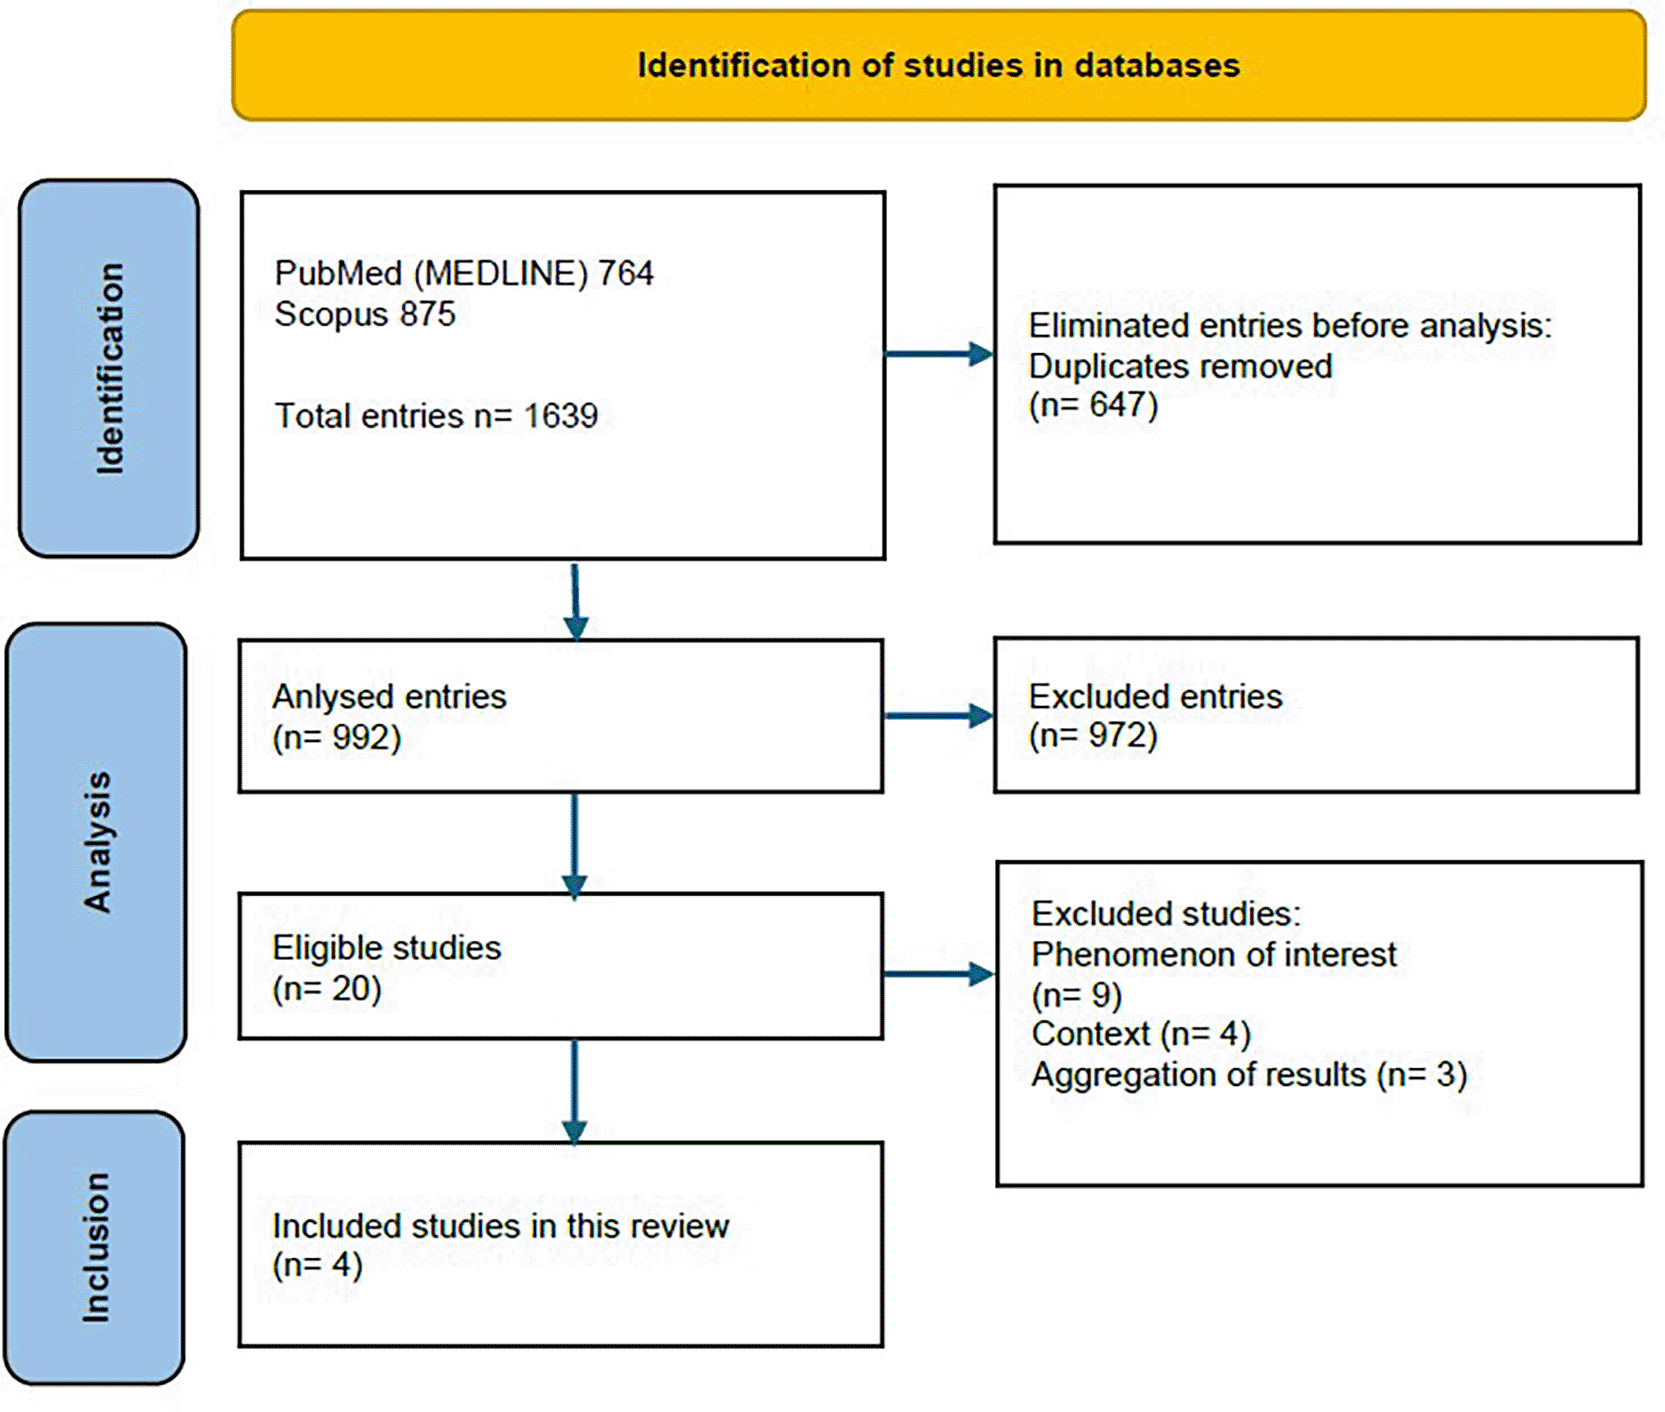
Figure 1. Search results, study selection, and inclusion process.
Characteristics of included studies
This study included four articles published between 2014 and 2024 on three different continents: Asia, Europe, and Oceania.9–12 All participants were healthcare professionals, with a particular focus on nurses with clinical practice in palliative care at the time of the study, one of them in a palliative care unit and the other three in a hospice setting. The data collection method was common to all four studies: interviews, semi-structured for three of them and narrative for one, with subsequent data analysis specific to each study.
Review findings
The meta-synthesis of the studies included in this review generated one synthesized finding, based on four categories and 23 findings, all unequivocal, extracted from the four studies included. This section presents a synthesis of the findings and categories included (
Table 2), with a summary of each category, supported by key illustrations that reflect the voice and experience of healthcare professionals in providing spiritual care in palliative care. Summary of findings: palliative care healthcare professionals who provide spiritual care reveal different conceptions and challenges to spiritual care, understand that assessment, documentation, and referral are significant steps in providing this care, and that spiritual care involves creating a connection with the sick person, knowing how to communicate and comfort, allowing the sick person to adapt to the disease process.
Table 2. Findings, categories, and synthesized findings.
| Findings |
Categories |
Synthesized findings |
|---|
| Making patients comfortable and relaxed | The perceptions and challenges that healthcare professionals experience in providing spiritual care, assessing spiritual needs, and documenting spiritual care in palliative care. | Palliative care healthcare professionals who provide spiritual care reveal different conceptions and challenges of spiritual care, understand that assessment, documentation, and referral are significant steps in providing this care, and that spiritual care involves connecting with the sick person, knowing how to communicate and comfort, allowing the sick person to adapt to the life-threatening illness process and prepare for their death. |
| spiritual care definitions |
| Challenges to spiritual care |
| Assessment of spiritual needs |
| Spiritual care documentation |
| Comfort through silence | The ‘tools’ that healthcare professionals believe are necessary for providing spiritual care – creating connection, touch and empathetic presence, communication, knowing how to comfort and refer. |
| Comfort through conversation |
| Spiritual consolation |
| Tuning in and opening up |
| Feel the atmosphere in the room |
| To be moved and touched |
| Connection |
| Love and compassion |
| Meaningful touch and presence |
| Communication |
| Provision of divine spiritual care and referral |
| Individuality and respect | The premises of spiritual care - legitimising human individuality, sharing religious rituals and recognising spiritual suffering. |
| Sharing the religious rituals of the sick |
| Recognition of spiritual suffering |
| Sources of spiritual suffering |
| Feeling spiritual and existential suffering |
| Preparation for death | Providing spiritual care involves preparing for death and includes post-mortem spiritual care. |
| Post-mortem spiritual care |
Healthcare professionals understand that spiritual care is related to different conceptions of this care. It is, in turn, dependent on the challenges inherent in this type of care. And, not unanimously, they recognize the importance of assessing spiritual needs, although they attest to the importance of documenting spiritual care as part of the care plan and referral to specialized professionals. They also argue that “tools” and certain practices are necessary for the provision of spiritual care and that there are some premises that must be respected, which can condition the entire process of adaptation of adults to their illness. They also reveal that preparation for death and post-mortem spiritual care are key elements in the provision of spiritual care. The summary of this finding is divided into four categories that emanate from 23 findings (
Table 2).
Category 1: The perceptions and challenges that healthcare professionals experience in providing spiritual care, assessing spiritual needs, and documenting spiritual care in palliative care
Participants reveal that they are more focused on quality of life than on prolonging the life of people with palliative care and list several practices that they consider to promote comfort, relaxation and, eventually, well-being. Thus, they also demonstrate that spiritual care helps people live in peace with their illness, accept it, adapt to it, alleviate suffering, and deal with symptoms more effectively. They testify that spiritual care includes the meaning of life, the patient’s values, beliefs, and the role of faith in the clinical circumstances they are experiencing. However, some healthcare professionals recognise that changes in consciousness or declines in the patient’s general condition are a challenge for spiritual care. On the other hand, there is no consensus on the assessment of spiritual needs, with some arguing that the use of specific instruments for assessing spiritual needs can be dehumanising. Others argue that any exploration of the subject must be genuine in order to establish a connection with the patient, conveying an interest in learning about their beliefs and ideas on the subject. However, they experience that spiritual care records are not always made due to a perceived lack of time, a lack of expression, writing and oral - specific language about this type of care, and a feeling that spirituality is undervalued in care. It is therefore crucial to encourage other members of the multidisciplinary team to provide spiritual care, as spiritual care records provide a unit of measurement for assessing the patient’s spiritual well-being and the effectiveness of the respective interventions.
“Spiritual care aims to improve the quality of life for our patients; we work to manage the annoying symptoms and decrease their suffering. When we provide spiritual care, we try to help patients adapt to illness.”
“And for some patients who are referred later, we predict that these patients will have some things that struggle to let go of, but his state of consciousness may also make it difficult for us to assess and help them in these aspects.”
“What’s not helpful is having a checklist in front of the patient … For some people it can be really off putting you know? “OK, I’ll just write that down.””
“With care plans, if they don’t have a care plan set up already about spirituality, then I would not tend to write anything.”
Category 2: The ‘tools’ that healthcare professionals believe are necessary for providing spiritual care – creating connection, touch and empathetic presence, communication, knowing how to comfort and refer
Healthcare professionals list some “tools” that they consider essential for providing spiritual care in palliative care. In their view, spiritual care depends on connecting with the patient’s spiritual truth, which then allows for a connection with spirituality. Similarly, silence and empathetic presence are important benefits for emotional consolation in existential suffering. Specifically, nurses emphasise that spiritual and existential care depends on the nurse’s ability to remain present, available and alert in a complex and unpredictable environment. They also reveal that they are sensitive to picking up on emotions in patients’ rooms, especially when family members are present. Consequently, they feel compelled and touched by patients’ encounters with their loved ones, allowing them to strengthen relationships of trust, alleviating suffering and helping patients and families on the path to peace, acceptance of death and reconciliation. In this sense, meaningful touch, understood as conscious physical contact with a humanistic connection, was considered part of spiritual care.
Physical presence, love, and compassion offer comfort, allow a connection between patient and nurse, and have been identified as an appropriate way to provide spiritual care. To the point that, in some cases, it is necessary to “sit with the pain”, that is, to witness a patient’s pain in order to create solidarity, comfort, and strengthen the relationship with them.
In turn, open communication and availability are essential ingredients in spiritual and existential care. Emotional consolation can take place through a conversation about the patient’s current situation, their ideas and feelings. On the one hand, it encourages patients to share their concerns without invading their autonomy and integrity; on the other hand, it opens up the possibility for families to share their grief, say their goodbyes and find the reconciliation they sometimes long for. Thus, some consider communication to be “the heart of spiritual care” because simply listening provides a safe environment for the patient to explore and vent their spiritual suffering. Nevertheless, for some participants, the possibility of referral to specialists, such as counsellors and chaplains, spiritual leaders and members of the patient’s family was presented not only as part of spiritual care but also as a common practice. Therefore, the spiritual care specialist should be accessible to patients and nurses after working hours, as is the case with specialist doctors who are on call/emergency duty; it is often at this time that patients experience greater spiritual suffering and require religious support.
“I think it is spiritual connection. It connected on different levels. It established a rapport and trust. But if you can then go on to make some comments around what they have said, that they recognize as being truth for them, then that to me is a spiritual connection.”
“Touch is very strength giving, it’s life giving, it’s love giving, it can smooth hurt, and it can take away fears.”
“It’s important to know, where the people you are caring for are at spirituality. It’s important to stop and listen. To talk if need be. But sometimes it’s just important to just be with the patient. You’re not there to do things to a patient. You are there to listen. You are there to let them say things to you which they need to get off their chest.”
Category 3: The premises of spiritual care – legitimising human individuality, sharing religious rituals and recognising spiritual suffering
Healthcare professionals emphasise that spiritual care should be tailored to each patient and that each person’s individuality should be recognised. They therefore consider that respect for adult patients and their personal beliefs is very important in the provision of spiritual care, regardless of their belief system. For some, spiritual care even includes helping patients with religious rituals, such as in situations where patients are unable to leave their beds or rooms. It may involve attending to the patient’s religious experience and spiritual beliefs related to the Divine; praying with patients or listening to their prayers, supporting patients in their own spiritual beliefs allows for a closer therapeutic relationship.
They emphasise that it is important to take time to establish a relationship with patients, to get to know them and to notice any changes in behaviour that may reveal spiritual suffering. They confirm that it is challenging to identify and interpret patients’ signs and warnings and that spiritual suffering is not always recognised and identified. They also point out that spiritual suffering can have a physical component, which can include a series of symptoms that add to the complexity, to the point where spiritual and existential suffering is so deeply rooted and entangled in the patient’s physical problems that it hinders their resolution. They also highlight that the subject of life after death is also a source of spiritual suffering.
“Spiritual care for me is identifying for the individual what is meaningful for them, what matters to them.”
“In some cases, I help patients perform Salah [prayer]; and patients need to concentrate while they were praying, so I close the room door and delay any procedure until they’re finished.”
“In clinical settings, we aren’t able to tell patients where they’ll go [after death] for sure. We can only listen to them, reassure them of all the good things they’ve done in theirs life that they really did them well.”
“I remember especially one man who was terribly restless and anxious. He couldn’t sleep. No matter how I asked him, he just said that he hurt all over. But it must have been more than physical pain because he was receiving strong analgesics through two different pumps, I often wonder if we could have done more for him. I got the impression of a very sad and lonely man.”
Category 4: The provision of spiritual care involves preparing for death and includes post-mortem spiritual care
With regard to death, participants experience that, in the dialogue about preparing for death, the patient’s spirituality and other spiritual issues become apparent. It is necessary to know what the patient is feeling in order to prepare them for death and to alleviate spiritual suffering. Even so, they consider that the role of caring for the spirit continues even after the patient’s death. It is necessary to care for the patient as if they were still alive, wash their body and talk to them as if they were still there. And possibly open a window to free the spirit, light a candle and pray for the patient’s soul.
““Is there something you need to do?” And a lot of people talk about their funerals. And interestingly enough spirituality comes into it then when you are talking to people. When you are talking about funerals and what they want and what they don’t want.”
“I’ll talk to them when I’m laying them out … sometimes, if I go into the room after they have gone and the rooms resting, I can still feel them … I’d say something like, “Oh! I’m just going to open the window to let them out”, I can still smell them, I can still feel them.”
Discussion
According to our knowledge and initial research, this literature review is the only one of qualitative studies that explores the experiences, perspectives, and perceptions of healthcare professionals regarding the provision of spiritual care in palliative care. This phenomenon under study generated one synthesized finding, which aggregates the perspective of palliative care health professionals who provide spiritual care on the different conceptions and challenges of spiritual care. Healthcare professionals understand that assessment, documentation, and referral are significant elements in spiritual care, and that spiritual care involves creating a connection with the sick person, knowing how to communicate and comfort, allowing the person to adapt to the life-threatening disease process and prepare for their death.
There is no unanimity or explicit indications of what is meant by spiritual care, and even less so about who will be responsible for providing this type of care in Palliative Care, which brings us to a reality that calls our attention to the lack of knowledge about this component, and the consequent need, of human beings, present in the various stages of life and, ultimately, of extreme relevance when faced with a life-threatening illness.
Some even speak of “awakenings of spiritual consciousness” when death is near. A crucial question therefore arises: given that spiritual intelligence is part of the human being and that our “ontological being” implies transcendence, can we neglect this dimension in the last stage of life, when our consciousness is recognized? Is this ethically and deontologically acceptable?
Healthcare professionals in palliative care are exposed to an extremely demanding reality that requires specific skills. Accompanying the “lived self” in palliative care represents a challenge that goes beyond clinical action, involving each professional’s own “self” and their own spirituality, fears, beliefs, and feelings. Are we willing to take these paths in our healthcare services?
Being confronted with a life-threatening illness or the lack of adequate treatment for a clinical condition and poor health is something that shapes the life and consciousness of any human being in so-called “first world” countries. Talking about this reality in places where there is a shortage of medicines and clinical resources—professionals, medication, and diagnostic and treatment techniques—would lead us to other issues.13 These are truly important issues related to justice, dignity, and solidarity that, although not addressed here, are worth noting.
In this context, we find the issue of spirituality and the provision of spiritual care in palliative care. Spirituality is recognized and included in palliative care, as we can see first in the World Health Organization definition and also in all the definitions and clarifications of various societies, associations, and entities. However, what is not clearly described is what spirituality means, whether there is an understanding of what the spirit is and what spiritual care entails. Therefore, and taking these assumptions into account, in a broad reading and without yet going into the details of the findings, we can identify that what healthcare professionals refer to as ‘experiences, perspectives, and perceptions’ mainly concerns their experience as healthcare professionals and not so much as professionals trained and prepared to accompany the process of transformation and adaptation that is desirable for a person with a life-threatening condition and/or proximity to death. The healthcare professionals in this study reveal that their experience fits into the current context of palliative care and spirituality in palliative care, however, they reveal the difficulty and even inability, at various times and for countless reasons, to address the dimension of spirituality with knowledge, specific skills, and availability.
The literature recognizes the need for investment and further exploration of the dimension of spirituality by healthcare professionals, especially since there is more literature in the American context than at the European level. However, even though there are at least three published definitions, these have not yet been appropriated by healthcare professionals and multidisciplinary teams, which consequently compromises spiritual care and its promotion.
Similarly, what is identified as spiritual care is consistent with the responses to a survey in the European context.13,14 However, it is outside the definition of spirituality in the French-Swiss context, which considers spirituality as the vector that permeates and concerns the whole of a person’s life.
In this review, healthcare professionals also identify some of the barriers to spiritual care, as has been the subject of recent studies.15 The lack of literacy on the subject is reiterated, as well as the availability for this type of support, which reinforces and underlines the need to rethink spiritual care. It may be necessary for specialists in the field to take early action in view of what we have seen, and it may be necessary to develop a spiritual care service, as is gradually happening in some centres worldwide. Referral, also mentioned by some participants in the review, as is the case at other levels of care, would thus become a reality, making specialists more accessible.
Spiritual suffering is consistently mentioned by healthcare professionals providing palliative care. However, it is identified as a source of enormous complexity and difficulty; while it is sometimes ignored, at other times it becomes impossible for healthcare professionals to manage. Pain is not always synonymous with suffering, and suffering does not always involve physical symptoms, as the literature supports.16 This is yet another indicator of the need to be advised by specialists and to consider the organization of care itself in order to respond to the human person in their entirety. “Sitting with pain,” as some healthcare professionals refer to it, reminds us of the “social friendship” that the Pope urges us to pursue in his encyclical Fratelli Tutti, which helps us to summarize everything that has been said above. Thus, “by recognizing the dignity of each human person, we can revive, among all, a worldwide desire for fraternity,” because “there is in them a value superior to material things and independent of circumstances, and it demands a distinct treatment. That every human being possesses an inalienable dignity is a truth that corresponds to human nature, regardless of any cultural transformation. Therefore, human beings possess the same inviolable dignity in every period of history, and no one can feel authorized by circumstances to deny this conviction or to act contrary to it.”17
Limitations
We consider that this review has some limitations. Only studies published in English, Portuguese, and Spanish were considered. Two databases of published literature were considered for the review, and grey literature was not considered. A comprehensive search strategy was developed, but only the first two steps (identification and analysis of keywords, analysis of text in titles and abstracts) were considered for this process, and no analysis of bibliographic references from the studies included in the review was performed to search for additional studies.
The studies selected for the review were not subject to methodological quality analysis, although the research team decided to accept any study regardless of this analysis. In this sense, it was not possible to transparently present the potential methodological weaknesses that each article might present.
We believe that these aspects may have limited the results, as other relevant reports may not have been considered in answering the review question. Due to the specificity of the phenomenon in studies and the few existing studies, the number of participants in the studies included in this review is small. This may represent a limited view of the experiences, perspectives, and perceptions of healthcare professionals who provide spiritual care in palliative care.
Strengths of this review
This qualitative literature review was conducted in accordance with JBI methodology, adapting the systematic literature review methodology process with the advice of researchers experienced in systematic reviews.
Currently, there are some studies on spirituality in palliative care; however, most existing reviews focus on clinicians’ perspectives on a topic, not specifically in the field of health, and reveal a less comprehensive view of the subject. In response to this concern, this literature review provides a broader and more in-depth view of the topic. And, despite being based on knowledge accumulated over tens, hundreds, and even thousands of years, it presents an innovative perspective on the topic and a new impetus for addressing an issue that is essential to human beings.
In turn, the relevance of the topic becomes very significant at a time when the population has a longer average life expectancy, situations tend to be prolonged over time, often revealing greater complexity in symptom control due to late referral, and there is a certain postponement of the end of life. And the ethical commitment, not only to the subject, recognized as part of bioethics insofar as it seeks to respond to a core dimension of human beings in the context of life, but also to clarity and integrity throughout the literature review process, providing the basis for identifying the ethical elements that should be scrutinized in an Systematic Literature Review.
Conclusion
We can refer to Spirituality as a fundamental dimension of palliative care. However, it is important to note that, to date, palliative care worldwide remains on the margins of what is desirable and necessary for the growing aging population and those with life-threatening illnesses, despite the countless scientific advances we are witnessing and the efforts of some academic communities, scientific associations, and health professionals.
Palliative care still needs organization and preparation to meet the anthropological challenge posed by the end of life and life-threatening situations, which anticipate the final moment and which many people still fear. This is an ethical challenge. And, as a result of the promise made by all doctors, through the Hippocratic oath, and consequently by all health professionals, to respect and accompany human life, we need specialists, at least for now. It may be that in a few centuries they will no longer be needed, when we are prepared and familiar with this subject. When our families talk about life and death with the same naturalness; when our schools teach about these topics; when our universities and schools give us opportunities to deepen and grow inwardly, through the full experience of living, which includes the process of living and accompanying death.
We believe that it is urgent to outline the profile of the specialist in this field and to develop a model of palliative care that addresses these issues, possibly closer to the well-known Anglo-Saxon hospice model of Ciceley Saunders, but without hesitation to adapt it to the culture of each country and each region of the world.
“The task of education, the development of habits of solidarity, the ability to think about human life in a more holistic way, and spiritual depth are necessary realities for giving quality to human relationships, so that society itself reacts to its own injustices, aberrations, and abuses of economic, technological, political, and media powers. There are liberal views that ignore this factor of human frailty and imagine a world that corresponds to a certain order that could, on its own, ensure the future and the solution to all problems.”17
Ethics and consent
Ethical approval and consent were not required.







