4.1 PA and HAL data outcomes and their implications for innovation
In PA and HAL, data are converted into societal value through four outcome channels: (i) publications (knowledge and methods), (ii) clinical studies (translation into interventions and evidence generation), (iii) patents (protectable technical inventions), and (iv) innovative products and services (devices, software, programmes, and care pathways). The continuity across these channels determines whether PA/HAL data ecosystems primarily generate publishable findings, or whether they also support scalable validation, protectable invention, and deployable solutions.
Publications. The PA/HAL literature is large and growing: a PubMed query using “physical activity” OR “healthy aging” returns
224,254 records overall,
198,127 over the last 20 years (2006–2025), and
144,976 in the last 10 years. The same results on the EU 27 countries are
68,511, 62,770 and
49,424 respectively (verified April 2026). These volumes indicate a strong evidence base, but publication output alone does not ensure comparability or downstream uptake: where data are not described with sufficient semantics and provenance, results accumulate without becoming easily interoperable, reusable assets.
Clinical studies and real-world evidence. A search of ClinicalTrials.gov for “Physical Activity OR Exercise” returns
28,760 registered studies overall and
20,861 over the 20-year window 2006–2025. The EU-27 share represents 9,457 trial-site registrations across 27 member states (see
Figure 3), with Spain (1,721), France (1,446), and Germany (968) accounting for 43% of EU-27 activity.
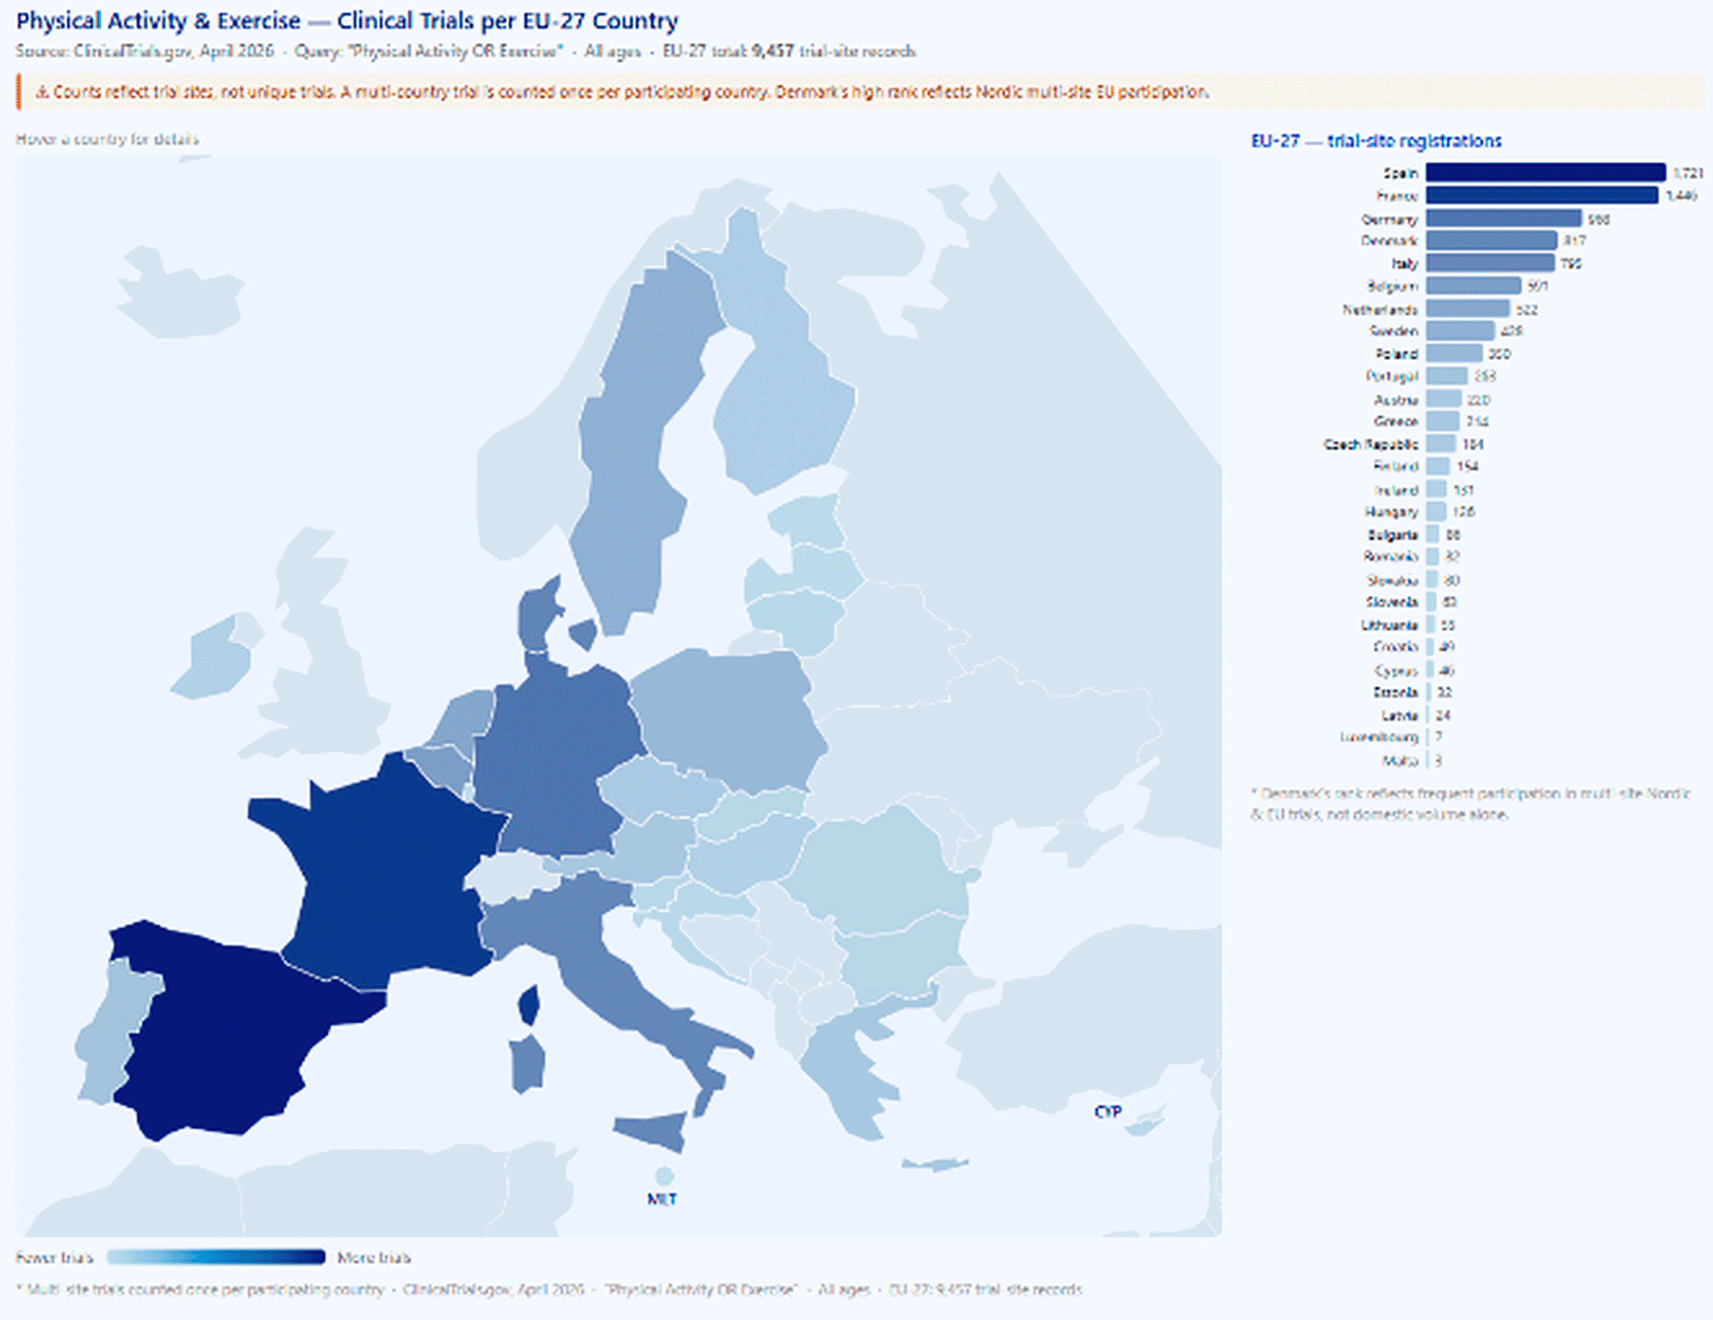
Figure 3. Clinical trial registrations by EU-27 country for interventions involving physical activity or exercise (ClinicalTrials.gov, April 2026; n = 9,457 trial-site records).
Counts reflect trial-site combinations: a multi-country trial is counted once per participating country. Colour intensity reflects trial volume on a logarithmic scale.
In practice, the translation value of this channel depends on whether PA/HAL variables and derived endpoints are specified consistently enough to support cross-study comparison and multi-site replication.
Patents. Patenting activity provides a proxy for conversion of PA/HAL measurement and analytics into protectable technical solutions. A Lens.org search using CPC class G16H20/30 (ICT for physical therapy/activity analytics) returns
48,874 patent records (16,714 simple families) overall, and
45,705 records (15,342 simple families over the 20-year window) (
Figure 4).8
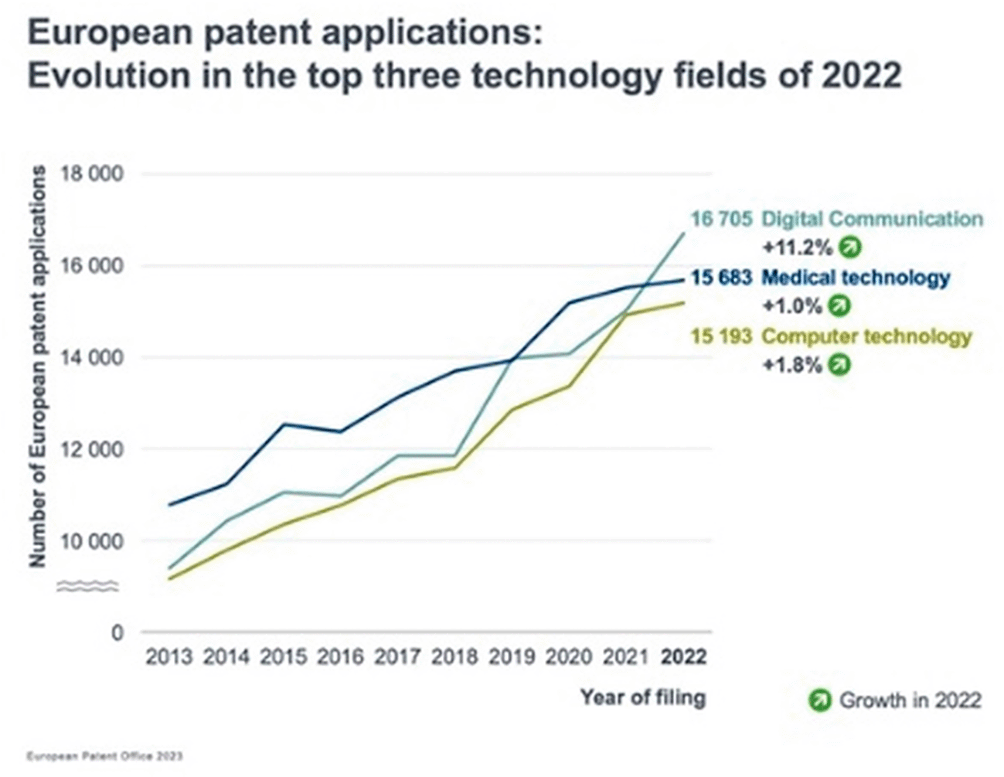
Figure 4.
European patent applications: evolution in the top three technology fields of 2022.
Source: EPO Patent Index 2024.8
An interactive version with country-level tooltips is available as Supplementary File S1.
However, where datasets and endpoints remain poorly comparable across contexts, incentives for standardisation and broad claims weaken, and invention-to-deployment cycles slow.
Innovative products and services. The innovation surface of PA and HAL extends well beyond consumer wearables. PA/HAL data underpin advances in sensing and measurement technologies, digital endpoints and biomarkers, clinical and public health decision support, intervention design and evaluation, and market-facing products ranging from devices to age-friendly environments. Globally, adjacent market evidence suggests that demand is shifting toward science-backed, data-driven wellness and fitness solutions, with McKinsey estimating a $1.8 trillion wellness market in 2024 and highlighting strong innovation momentum around products and services that combine personalization, efficacy, and measurable outcomes.9
In Europe, however, the competitive logic is more strongly mediated by regulation, interoperability, and evidence generation. European Commission analysis of digital health innovation, particularly in wearable medical devices, points to the strategic importance of standards, regulatory pathways, and industrial policy for scaling data-enabled health solutions.
At the ecosystem level, EIT Health’s 2024 results (12 new healthcare innovations, support for 372 start-ups and scale-ups, and €227 million raised by supported ventures) indicate that Europe has a strong innovation base, but one that depends on translating heterogeneous data assets into reusable, trustworthy, and interoperable evidence. Across these domains, the ability to convert PA/HAL data into scalable products and services depends less on data volume alone than on semantic clarity, provenance, and reuse conditions.10
EU position and implication. From a European perspective, the challenge is not a lack of PA/HAL research activity, but limited continuity across the four channels: data are frequently produced in ways that support publication, yet are less consistently described for reuse, cross-study synthesis, and scalable RWE. This raises the cost of replication and multi-site analytics, slows translation into protected inventions, and constrains product/service scaling, setting the context for the gap analysis (Section 5), including EU positioning relative to other major jurisdictions.
These patterns are summarised across the four innovation channels in
Table 2.
Table 2. PA/HAL innovation output across four channels: global volume and EU-27 position (verified April 2026).
| Innovation channel Source & query | Global total ll-time/20-yr | EU-27 volume ll-time/20-yr | EU-27 share f global | Key implication for PA/HAL interoperability |
|---|
Publications
PubMed: “physical activity” OR “healthy aging” | 224,254
198,127 (20-yr) | 68,511
62,770 (20-yr) | ~30.5%
Verified April 2026 | Strong output base but limited cross-study reusability. EU publications accumulate without becoming interoperable evidence assets in the absence of consistent metadata and semantics. |
Clinical trials
ClinicalTrials.gov: “Physical Activity OR Exercise” | 28,760
20,861 (20-yr) | 9,457*
trial-site records | ~33%
| EU trial density is high, but endpoint harmonisation is weak. PA/HAL variables are rarely described consistently across multi-site studies, limiting RWE generation and meta-analysis. |
Patents
Lens.org: CPC G16H20/30 (digital PA/HAL analytics) | 48,874
records; 16,714 families (all-time)
45,705/15,342 (20-yr) | ~40%
EPO member states’ share of global medtech filings (EPO Patent Index 2024) | ~40%
EU-specific PA/HAL families: verify via Lens.org/PATSTAT (A61B5 + G16H20/30) | Invention-to-deployment cycles slow when datasets and endpoints lack comparable descriptions. Weak semantics reduce incentives for broad standardised patent claims. |
Market & innovation
Wellness market + EIT Health 2024 | $1.8 trillion
global wellness market (McKinsey 2024) | 12
new innovations; 372 start-ups supported; €227 M raised (EIT Health 2024) | Strong base
EU share of global wellness market est. ~20–25% | EU innovation is regulation- and evidence-mediated. Scaling PA/HAL products requires interoperable, reusable data assets. The federation-first approach must be operationalised in practice. |
Data sources and why semantics are harder than “clinical data”
PA and HAL research combines heterogeneous data sources spanning clinical, behavioural, and environmental domains: (i) wearable and smartphone sensing (e.g., steps, accelerometry-derived activity measures, heart rate, sleep proxies, mobility indicators); (ii) clinical measurements (diagnoses, medications, biomarkers, functional tests); (iii) self-reported behaviour and context (activity type, setting, barriers, wellbeing); and (iv) environmental and social determinants (built environment, walkability, seasonality, work patterns). This breadth is a defining strength of PA/HAL research, but it also creates a distinct semantic challenge compared with traditional clinical data. Unlike many clinical variables, where shared terminologies, care pathways, and regulatory requirements impose a baseline level of standardisation, PA/HAL variables are highly sensitive to measurement context and analytical choices. “Steps” varies by device, firmware, and algorithm; “moderate activity” depends on calibration methods, cut-points, population characteristics, and study protocols; “sedentary time” depends on posture inference, wear location, and non-wear detection rules; and key HAL constructs such as “frailty” correspond to multiple operational definitions across clinical and population-health traditions.
As a result, PA/HAL is a metadata- and provenance-intensive domain. Meaningful interpretation requires explicit documentation of devices and placement, sampling and epoching, wear-time processing, feature extraction pipelines, and algorithm versions. Where such descriptors are absent, reuse barriers arise earlier and more sharply than in many clinical datasets, undermining comparability, reproducibility, and the feasibility of federated RWE workflows.
This semantic variability has direct practical consequences. In PA/HAL, innovation depends on the ability to compare results across studies, validate digital endpoints, aggregate evidence for regulatory or payer decisions, and scale products and services across settings. When semantics and processing choices are under-specified, results may be publishable but not reusable; comparable in name but not in meaning; and credible locally but not transferable across sites or jurisdictions.
These constraints propagate directly into the innovation pipeline, limiting the transition from data to validated endpoints, protectable inventions, and scalable PA/HAL products and services. The following sections examine how these issues manifest across the remaining layers of the interoperability stack.
Example:
MOBILISE-D - harmonising digital mobility outcomes across Europe.
The Mobilise-D consortium (IMI2, 2019–2024) illustrates both the scale of the PA/HAL semantic harmonisation challenge and what a structured response looks like. Spanning 34 organisations, 17 clinical sites in 10 countries, and four disease cohorts (Parkinson’s disease, COPD, multiple sclerosis, proximal femoral fracture), the consortium set out to validate real-world digital mobility outcomes (DMOs) from a single lower-back-worn inertial measurement unit (IMU).
Its data standardisation protocol (Bonci et al., Scientific Data, 202311) explicitly documents the heterogeneity problem encountered: different devices, firmware versions, sampling rates, wear locations, and gold-standard systems produced non-comparable raw signals even when measuring nominally identical constructs. Mobilise-D’s response — a standardised data format, device-agnostic algorithm framework, and shared lexicon for mobility outcomes — required dedicated infrastructure and sustained consensus effort across the full consortium over five years.
Key lesson for PA/HAL interoperability: harmonisation is achievable, but disproportionately costly when semantics, provenance, and processing metadata are not captured by design at the point of data collection. The Mobilise-D Technical Implementation Manual (Zenodo, 2025)12 now offers a transferable template for what a minimum viable metadata and provenance profile looks like for wearable mobility data.
4.3.1 Cataloguing practices: fragmented discoverability
In Europe, PA and HAL data are catalogued using a combination of generic data cataloguing standards, clinical terminologies, and research repositories. The dominant cataloguing approach is based on DCAT (Data Catalogue Vocabulary), which underpins many European data portals and is promoted for cross-domain dataset discovery within EOSC and national open data portals. However, DCAT is intentionally domain-agnostic
, effective for high-level discovery (“a dataset exists”), but unable to capture content-level characteristics required to meaningfully discover and compare PA/HAL datasets.
For clinically anchored data sources, cataloguing relies on SNOMED CT, ICD, and LOINC. These provide strong semantic control for diagnoses and laboratory measurements, but PA/HAL variables, particularly those derived from wearables, functional assessments, or behavioural instruments, are only partially covered. In research and observational data ecosystems, OMOP improves analytical interoperability but focuses on data already mapped into the model, leaving upstream discovery of heterogeneous PA/HAL datasets underserved. Repository-based cataloguing (Zenodo, OpenAIRE) relies on generic metadata schemas with limited support for domain-specific discovery.
As a result, current PA/HAL cataloguing practices exhibit recurring patterns:
• Dataset registration at a high, non-domain-specific level (e.g. DCAT-based records);
• Semantic description concentrated on clinical variables, with limited coverage of PA/HAL-specific constructs;
• Fragmented linkage between datasets, study protocols, code, and derived measures;
• Discovery dependent on project knowledge rather than systematic search.
Even when PA/HAL data are formally “open” or “shareable under conditions,” they are often not discoverable in a way that supports reuse, comparison, or innovation. This fragmentation directly affects the innovation pipeline: datasets that cannot be reliably found and characterised are unlikely to be reused across studies, incorporated into federated analyses, or translated into scalable PA/HAL products and services. The limitations of current cataloguing practices therefore form a critical bottleneck between data production and innovation outcomes. PA/HAL reuse depends on an ecosystem of cataloguing standards (e.g. DCAT), clinical terminologies (e.g. SNOMED CT, LOINC, ICD), research infrastructures (e.g. EOSC, OpenAIRE, BBMRI-ERIC
, ELIXIR), and federation tools (e.g. OMOP/OHDSI, DataSHIELD), but these components are typically adopted unevenly and rarely assembled into an end-to-end, domain-coherent discovery-to-compute pipeline (see Appendix).
4.3.2 Metadata: variable-level ambiguity and insufficient processing provenance
PA datasets frequently lack consistent metadata on the following elements: device make and model, firmware version, and wear location (e.g. wrist, hip, ankle); sampling frequency, epoch length, and calibration protocol; non-wear detection and data-cleaning rules; feature extraction pipelines (e.g. raw accelerometry → activity counts → intensity categories); and versioning of algorithms, models, and derived measures. Where metadata are mapped to healthcare standards (e.g. HL7 FHIR Observation resources or LOINC codes), this is typically limited to high-level clinical observations and does not capture the full processing context of PA/HAL variables. As a result, many datasets are technically findable and accessible, but fall short of the FAIR Reusability (R) requirements, which explicitly depend on rich metadata, provenance, and references to community standards.
These limitations lead to two recurring failures. First, comparability failure, where variables share a common label but differ in operational meaning (“same label, different meaning”). Second, reproducibility failure, where analytical pipelines cannot be reliably reconstructed, audited, or re-executed. Both directly constrain the reuse of PA/HAL data for cross-study synthesis, federated analysis, and innovation pipelines.
Example: UK Biobank — strengths and limits of large-scale wearable metadata
The UK Biobank accelerometry sub-cohort (Doherty et al., PLOS ONE, 201713) represents one of the most extensively documented wearable PA datasets in existence: over 100,000 participants, 7-day wear protocol, Axivity AX3 wrist-worn triaxial accelerometer at 100 Hz, with calibration procedures, non-wear detection rules, and feature extraction pipelines published in peer-reviewed literature and maintained in an open-source analysis tool.
This level of metadata documentation makes secondary analysis feasible at scale: studies linking MVPA to 697 incident diseases (Ye et al., npj Digital Medicine, 202214) and derivation of age-referenced centiles (Rowlands et al., JSHS, 202515) became possible because the processing chain was explicitly documented and traceable.
However, even UK Biobank illustrates the limits of current practice. Its accelerometry documentation explicitly notes that “data processing methods are under continual development, and so data processed with different versions of the tool and of models may not be directly comparable.” This version-sensitivity is the norm across wearable PA research, and underscores why machine-actionable provenance and algorithm versioning are minimum requirements for FAIR-compliant PA/HAL data, not optional enhancements.
4.4.1 Taxonomies and semantics: partial reuse, limited domain alignment
In practice, semantics are assembled ad hoc: some clinical variables may align with established biomedical vocabularies; behavioural and context descriptors are often free text or local codes; and intervention descriptions vary widely (frequency, intensity, delivery mode, adherence metrics). A “semantic gap” emerges where PA and HAL sit between clinical medicine, behavioural science, and public health. This is precisely the gap that federated data spaces must bridge as federation depends on shared meaning more than shared storage.
Across PA and HAL research, datasets frequently lack consistent, domain-relevant metadata, even when they are deposited in repositories or registered in catalogues that nominally support FAIR principles. In practice, metadata provision is often limited to generic schemas (e.g. Dublin Core, DataCite) and repository-level descriptors, while PA/HAL-specific metadata standards are rarely applied systematically.
Micro-case: ‘MVPA’ across three datasets — same label, three different meanings
Consider a researcher attempting to pool physical activity data from three European studies, each reporting “minutes of moderate-to-vigorous physical activity (MVPA) per day”:
▸ Study A (UK Biobank): MVPA derived from wrist-worn Axivity AX3 at 100 Hz, using ENMO (Euclidean Norm Minus One) ≥40 mg, 7-day continuous wear.
▸ Study B (Mobilise-D COPD cohort): MVPA proxied via walking speed ≥1.0 m/s from a lower-back IMU, bout-based detection using the Mobilise-D algorithm suite.
▸ Study C (RADAR-base deployment16): MVPA derived from Fitbit step count >100 steps/min via vendor API; no raw signal access; no calibration record.
Each dataset reports ‘MVPA’ but operationalises it through a different device, placement, signal type, threshold, algorithm, and processing chain. Without explicit metadata on each of these elements, federated queries return results that appear comparable but are not. No post-hoc statistical harmonisation can fully recover comparability when the underlying measurement semantics are undocumented. This micro-case illustrates why the metadata, semantic, and provenance layers of the interoperability stack are prerequisites, not options, for meaningful PA/HAL federation.
4.4.2 Taxonomies and semantics: partial reuse and limited domain alignment
Semantic annotation of PA/HAL data currently relies on a fragmented combination of clinical terminologies, research vocabularies, and local conventions. Established biomedical standards, such as SNOMED CT (clinical concepts), ICD-10/11 (diagnostic classifications), and LOINC (laboratory tests and clinical observations), are widely used where PA/HAL variables intersect with healthcare data. However, these terminologies provide limited and uneven coverage of PA/HAL-specific constructs, particularly those derived from wearables, functional assessments, and behavioural measures.
As a result, behavioural and contextual descriptors are often recorded as free text, study-specific variables, or local code lists, while intervention characteristics (frequency, intensity, duration, delivery mode, adherence) vary substantially in structure and meaning across studies. Even when observational data models such as OMOP are adopted, PA/HAL variables are frequently mapped in non-standard ways, or excluded altogether, due to the lack of agreed semantic representations.
This gap has direct implications for innovation and federation. Federated data spaces and compute-to-data approaches depend less on shared storage than on shared meaning. Where PA/HAL semantics are weak or implicit, federation becomes technically feasible but analytically fragile: queries may execute, but results are not comparable. Consequently, semantic misalignment limits the generation of robust real-world evidence and slows the translation of PA/HAL data into validated endpoints, interoperable services, and scalable innovations.
Europe already has strong, mature components for cataloguing (DCAT-AP), clinical semantics (SNOMED/LOINC/ICD), open science discovery (EOSC/OpenAIRE/Zenodo), biobanking infrastructure (BBMRI-ERIC), life science data management (ELIXIR), and observational federation (OMOP/OHDSI, DataSHIELD), and is now adding a major secondary-use governance and infrastructure layer via EHDS/HealthData@EU, but PA/HAL reuse remains limited because these components are rarely assembled into an end-to-end pipeline that preserves PA/HAL-specific meaning from capture to federated analysis (see Appendix).







