1. Introduction
Immersive virtual reality (IVR) constitutes a powerful paradigm for the experimental study of human behaviour in simulated environments (Bailenson, et al., 2025). Traditionally, IVR experiments are conducted in physical labs, which afford high experimental control, access to high-end hardware and close participant supervision. However, lab-based IVR experiments are also resource-intensive, as they require specialised equipment, dedicated infrastructure, coordinated participant scheduling and experimenter co-presence. These constraints impose high barriers to entry, limit achievable sample sizes and may introduce selection biases.
Remote IVR enables participants to complete IVR experiments using personal or researcher-provisioned head-mounted displays (HMDs) without on-site supervision. Because researcher involvement may still vary, we use the term remote IVR to include asynchronous self-administered studies, synchronous remotely supervised studies, and hybrid formats. By decoupling data collection from physical labs, remote IVR promises to address the limitations of traditional lab-based IVR experiments. Its advancement has been facilitated by the growing consumer adoption of HMDs (Radiah, et al., 2021), the availability of software tools for building and distributing IVR experiments (Adeniyi, Rosenberg, & Thomas, 2021; Cesanek, Shivkumar, Ingram, & Wolpert, 2024), and the proliferation of online participant platforms such as Prolific and MTurk, which provide access to larger and more geographically distributed participant pools than single-site laboratory recruitment protocols.
Notwithstanding the increasing uptake of remote IVR in empirical research, there is no recent systematic account focused specifically on how such studies are designed and implemented across HMD access models, deployment routes, recruitment practices, procedures, measures, and ethical safeguards, or assessment of whether they fulfil their methodological promises. This makes it difficult for researchers to ascertain the generalisability, robustness, and reproducibility of remote IVR.
This review extends prior work on remote VR by shifting the focus from feasibility guidance to a systematic empirical account of how remote IVR studies have actually been implemented and reported across the literature. Radiah et al. (2021) provided important early guidance for conducting remote VR studies via participant-owned HMDs, including different implementation and distribution paths as well as independent and remotely guided study formats. Building on this work, the present review examines a broader set of methodological issues, including recruitment, sample composition, HMD access, study deployment, experimental procedures, outcome measures, and ethical safeguards.
To support comparison across heterogeneous studies, we classify access and delivery arrangements along two dimensions: how participants access an HMD, and how the IVR study itself is delivered. This classification, described in the Methodology section, is used as an organising tool within a broader synthesis rather than as the central contribution of the review. Adjacent work on crowdsourced and online experimentation offers broader methodological lessons, but does not fully capture IVR-specific constraints such as headset ownership, device provisioning, embodied safety, spatial setup, platform restrictions, in-headset consent, and immersive behavioural data capture.
To address this gap, this systematic review synthesises recent empirical research involving remote IVR with the aim of characterising prevailing methodological, technical, logistical and ethical practices and assessing whether and how remote IVR broadens participation beyond traditional laboratory samples. Specifically, our review has the following objectives: i) identify the recruitment channels and sample characteristics reported in remote IVR studies, including demographic and geographic indicators, ii) categorise the HMD access models and study deployment routes used to implement remote IVR experiments, iii) examine the experimental paradigms, task designs, procedures, and outcome measures adapted for remote deployment, iv) analyse how ethical considerations, including informed consent, data privacy, participant safety, adverse effects, and support procedures, are handled in the absence of in-person experimenter supervision, and v) identify emerging practices, persistent reporting gaps, and future directions to guide more transparent, inclusive, and ethically sound remote IVR research.
The remainder of this systematic review is structured as follows. In
Section 2, we describe the methodology underlying our review. Then, in Section 3, we present the results, synthesising cross-study patterns regarding sample characteristics, recruitment channels, access and delivery, study design, and ethics. Based on these findings, we identify emerging practices, persistent gaps and future research directions (Section 4). Finally, we conclude by summarising contributions and acknowledging limitations (Section 5).
2. Methodology
This systematic review followed the PRISMA (Preferred Reporting Items for Systematic Reviews and Meta-Analyses) guidelines (Page, et al., 2021). A PRISMA flow diagram detailing the processes of study identification, screening, eligibility assessment and final inclusion is presented in
Figure 1.
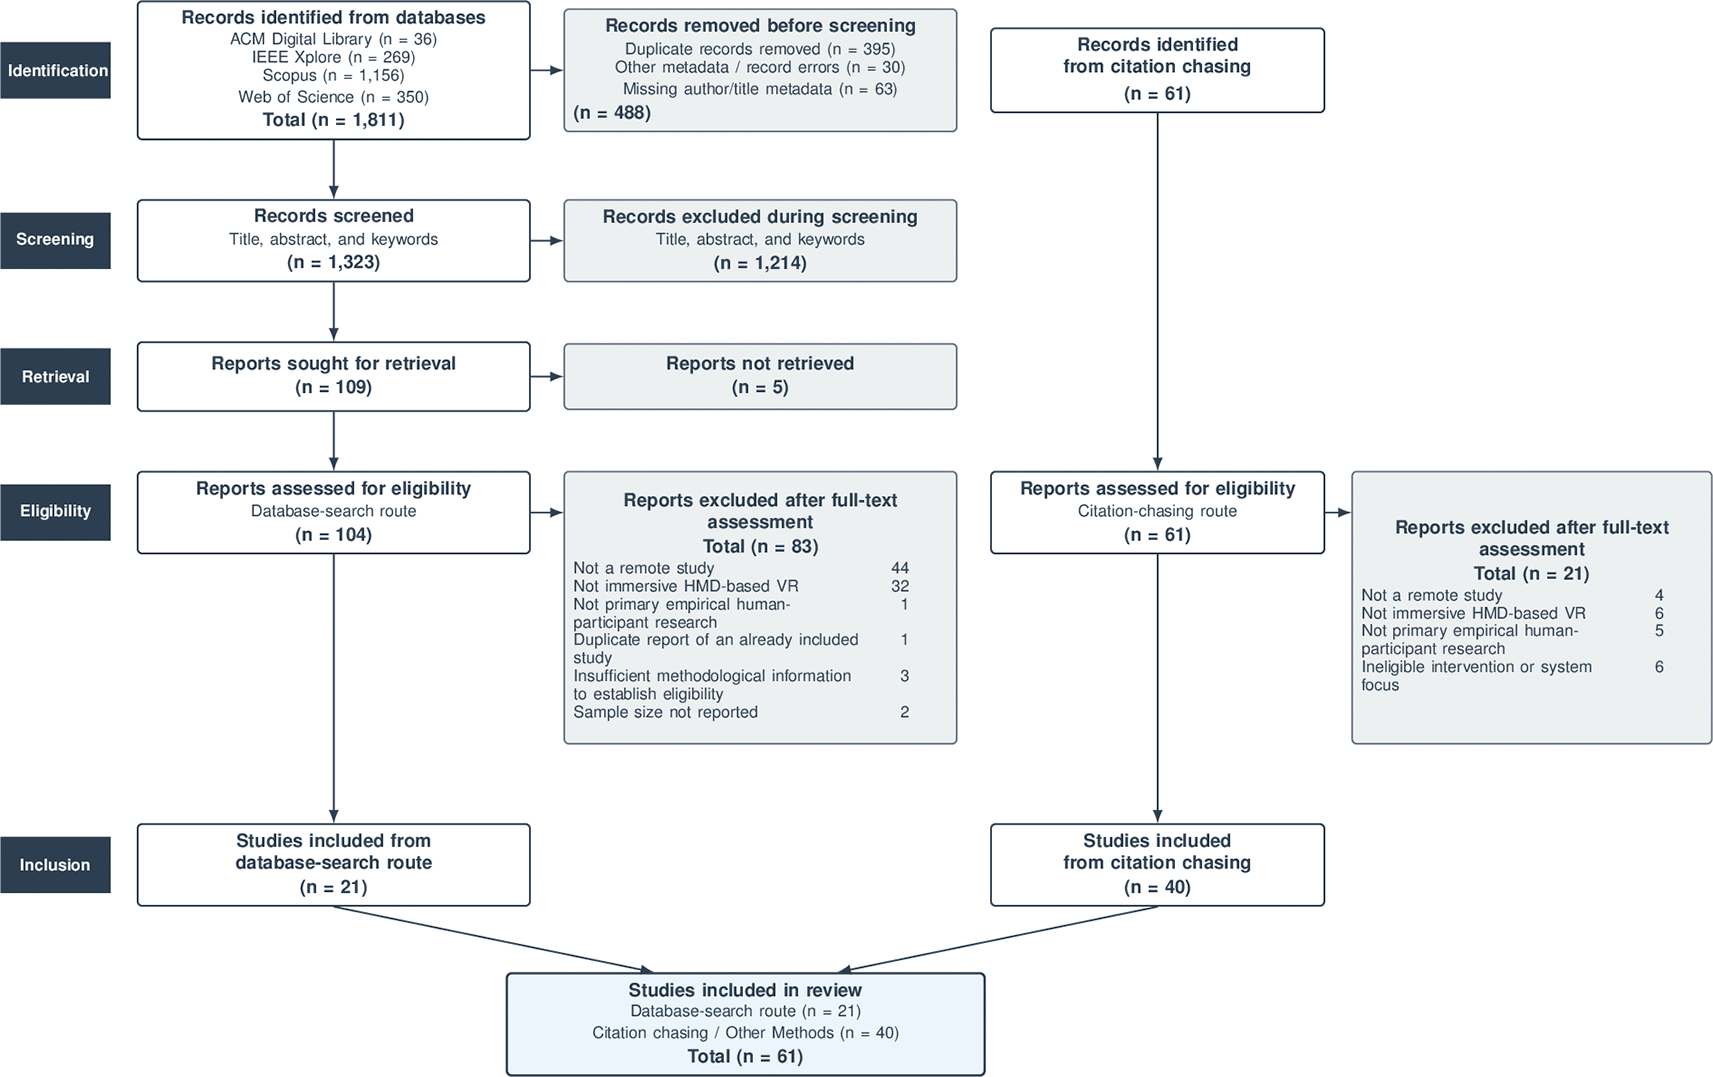
Figure 1. PRISMA flow diagram.
2.1 Search strategy
We searched four electronic databases: ACM Digital Library, IEEE Xplore, Scopus, and Web of Science. The final database searches were conducted on 9 July 2026. A publication-date limit of 1 January 2015 to 30 June 2026 was applied directly in each database interface, reflecting the widespread availability of consumer-grade IVR technologies after 2015. English was not used as a database-interface language filter; the English-language eligibility criterion was applied during screening.
The same core Boolean logic was implemented using database-specific search fields: Anywhere in ACM Digital Library; All Metadata in IEEE Xplore, with grouping parentheses removed as required by the interface; Article title, Abstract, Keywords in Scopus; and Topic in Web of Science. The search combined terms for immersive virtual reality, remote or decentralised experimentation, and empirical human-participant research. The final executed search strategies are reported in Appendix A of the PRISMA supporting document deposited in the accompanying Zenodo data repository (Thomsen, Glage, & Krueger, 2026). The search also used a NOT block containing review-related terms and the domain terms rehabilitation, education, training, teleoperation, and collaboration. These exclusions were used to reduce the large volume of intervention/application literature unrelated to the methodological review question and to maintain a focus on remote experimentation. Their possible effect on search sensitivity is acknowledged as a review limitation.
2.2 Inclusion and exclusion criteria
Primary empirical reports were eligible regardless of publication format when they described remote immersive HMD-based research with human participants, without an experimenter physically co-located during the eligible study session, and contained sufficient methodological information to extract characteristics relevant to the review. Remote participation was understood as study participation outside a conventional locally supervised laboratory session, including participant-owned or researcher-provisioned HMDs used at home or another remote site; placing the moderator elsewhere while the participant remained at a controlled laboratory station did not by itself constitute an eligible remote study. Eligible reports could address behavioural, perceptual, cognitive, affective, interaction, feasibility, recruitment, deployment, usability, data-quality, or related methodological outcomes. Reports were required to be written in English and dated from 1 January 2015 to 30 June 2026.
We excluded reviews, theoretical or position papers without eligible original human-participant data, studies conducted only in fully supervised laboratory settings, studies that did not use immersive HMD-based VR for the eligible remote component, reports without a usable sample size for the eligible remote-IVR component, and reports without sufficient methodological information to establish eligibility and support the planned extraction. Consistent with the domain exclusions in the executed search, reports centred substantively on rehabilitation or clinical intervention delivery, education or training, teleoperation, or collaboration applications were also excluded when those application goals defined the report’s primary empirical contribution rather than remote-IVR experimentation itself. This application-scope boundary was applied at report level rather than by the mere occurrence of a domain term in a task or outcome.
2.3 Screening and study selection
All retrieved database records were exported and deduplicated prior to screening. Two researchers independently screened titles and abstracts, followed by full-text assessment of potentially eligible reports. Disagreements were resolved through discussion.
To reduce the risk of missing relevant work using non-standard terminology, forward citation chasing via Google Scholar was conducted from two seed publications, Mottelson and Hornbæk (2017) and Ma et al. (2018). The final citation-chasing search was completed on 10 July 2026. Identified records dated from 1 January 2015 to 30 June 2026 and written in English were deduplicated and screened using the same eligibility criteria and independent-review procedures as the database records.
The database search identified 1,811 records, of which 1,323 remained after removal of 488 records before screening. Following title, abstract, and keyword screening, 1,214 records were excluded and 109 reports were sought for retrieval. Five reports could not be retrieved, leaving 104 database-route reports for full-text assessment. Eighty-three reports were excluded after full-text assessment and 21 studies were included from the database-search route. Citation chasing identified 61 additional records, all of which were assessed for eligibility; 21 were excluded and 40 studies were included from this route. In total, 61 studies were included in the systematic review. The 21 excluded citation-chasing publications and their primary exclusion reasons are documented in the accompanying review-data workbook alongside the database-route full-text decisions.
2.4 Data extraction and classification
For each included publication, we extracted publication metadata, technical implementation details, HMD access and study-delivery information, study design characteristics, sample characteristics, recruitment, task and measurement information, and reported ethical procedures. Each included publication was treated as one study record.
The two reviewers divided the included publications between them for extraction. One reviewer subsequently verified the complete extracted dataset, and disagreements or ambiguous classifications were resolved through discussion. Study authors were not contacted to clarify missing or unclear information. The coding framework was developed and refined iteratively during coding. Where a publication contained multiple applicable task, self-report, behavioural, recruitment, or ethical categories, all applicable categories were retained; these variables are therefore non-exclusive. Information absent from a report was coded as “not reported” and was not imputed.
Age and gender were retained as reported sample- or experiment-level values where publications reported multiple samples or experiments. For Huber and Gajos (2020), the eligible HMD sample comprised 27 participants across the two online experiments; age, gender, and geographic statistics reported for the broader mixed-device sample were not used in the HMD-only demographic aggregates.
To support consistent coding of access and delivery arrangements, we coded each study along two dimensions. The first dimension captures how participants accessed the HMD: participant-owned HMDs, researcher-provisioned HMDs, or mixed access models. The second dimension captures how the IVR study itself was delivered: native applications, existing IVR platforms, browser-based/WebXR studies, or mixed delivery routes. Combined codes such as PO-NA, PO-PL, and RP-WX are used as shorthand for these two coding dimensions; they do not imply that all combinations are equally common or technically distinct deployment architectures.
2.5 Synthesis methods and review-level assessments
The review was designed as a descriptive methodological synthesis addressing how remote IVR studies have been conducted and reported, rather than as a comparative synthesis of intervention effects. The publication was the principal study-record unit and the denominator for publication-level percentages was 61 unless stated otherwise. Non-exclusive coding categories were counted once per publication within each category. Sample size was summarised from the eligible remote-IVR sample for each publication. Age and gender summaries used all eligible reported sample- or experiment-level values and were calculated as unweighted means; missing values were not imputed.
Results were synthesised using counts, percentages, descriptive distributions, unweighted means where appropriate, figures, a study-characteristics table, and narrative synthesis across recruitment, sample composition, access and delivery, study administration, tasks and measures, and ethics. No intervention effect measure was selected or synthesised, and no meta-analysis, formal heterogeneity investigation, or sensitivity analysis was conducted. No formal study-level risk-of-bias assessment, reporting-bias assessment, or certainty-of-evidence assessment was undertaken because the review focused on methodological and reporting characteristics rather than comparative intervention effects. Consequently, conclusions should not be interpreted as estimates of intervention effectiveness or as formal ratings of the methodological quality or certainty of the included evidence.
3. Results
A study-level summary of the included studies is reported in Appendix B of the PRISMA supporting document deposited in the accompanying Zenodo data repository (Thomsen, Glage, & Krueger, 2026). In the following subsections, we highlight key patterns identified regarding sample characteristics, recruitment channels, access and delivery, study design and ethics.
The review corpus also included the following publications, which are not otherwise cited individually in the narrative synthesis: Angerbauer et al. (2024), Arora et al. (2021), Barton et al. (2024), Batmaz and Stuerzlinger (2021), Bovo et al. (2022), Ch et al. (2023), Chen and Li (2025), Cowan et al. (2023), Cui and Mousas (2021), Grinyer and Teather (2022), Kelly et al. (2022), Korshunova-Fucci et al. (2024), Kumle et al. (2025), Li et al. (2021), Liu et al. (2021), Mathis et al. (2022), Moinnereau et al. (2022), Mottelson and Hornbæk (2020), Ogawa and Narumi (2026), Ragozin et al. (2020), Ratcliffe and Tokarchuk (2022), Ribeiro et al. (2021), Riches et al. (2024), Saffo et al. (2020), Samimi and Teather (2022), Scavarelli et al. (2023), Steed and Lai (2025), Teo et al. (2022), Vindenes and Wasson (2021), Wagener et al. (2024), Warsinke et al. (2024), and Wolfe et al. (2022, 2023).
3.1 Sample characteristics
3.1.1 Sample sizes
Across the included studies, sample sizes range from 4 to 282 participants, with a mean of 59.2. Although most studies include modestly sized samples, some consider substantially larger international samples (e.g. Mottelson, et al., 2021a; Mottelson, Petersen, Lilija, & Makransky, 2021b).
Figure 2 visualises the distribution of reported sample sizes.
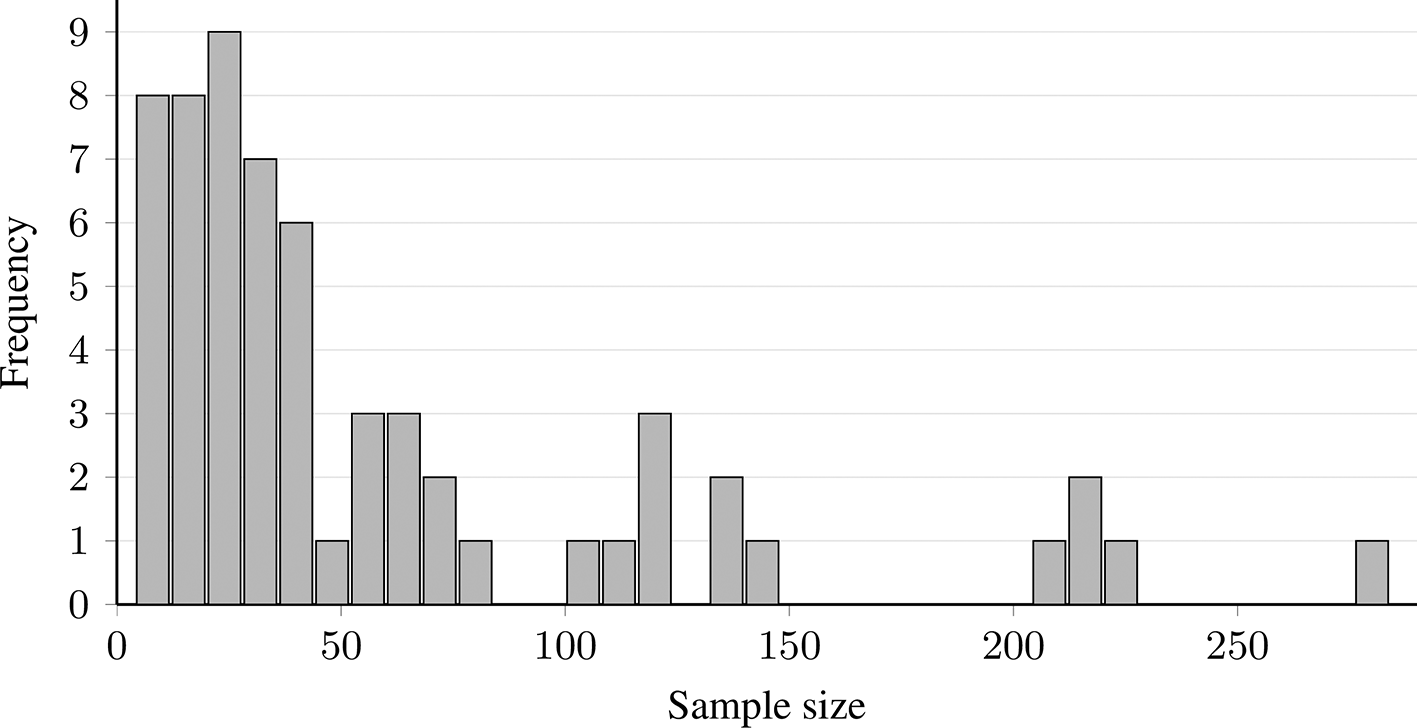
Figure 2. Histogram of reported sample sizes across the included studies.
3.1.2 Sample composition
Gender information is reported in 53 of the 61 publications. Across 55 eligible reported sample- or experiment-level male-share values, the unweighted mean male share is 66.2%; across 59 eligible female-share values, the unweighted mean female share is 34.2%. Because reporting availability differed, these two unweighted means are not complementary proportions. Mean age is reported in 41 publications, corresponding to 49 reported sample- or experiment-level mean-age values, with an unweighted average of 28.3 years. This gender skew is somewhat stronger than that reported by Peck et al. (2020), who found 61% male and 39% female participants in human-subject studies from the IEEE VR Proceedings. Consistent with the broader assessment of VR research by Bailenson et al. (2025), these findings suggest that remote deployment alone has not resolved longstanding challenges in achieving representative participant samples.
Broader socioeconomic and sociodemographic variables beyond age and binary gender are reported in nine of the included publications. These include education and employment status (Kissel, Rechowicz, & Shull, 2023; Mottelson, et al., 2021a; Plechatá, Morton, Perez-Cueto, & Makransky, 2022; Saffo, Di Bartolomeo, Yildirim, & Dunne, 2021), while one publication also reports residence, educational attainment, and household income bands (Ma, Cackett, Park, Chien, & Naaman, 2018). Four additional publications report variables including grade or student status, race or ethnicity, education, native language, and employment status (Björling, et al., 2022; Han, et al., 2023; O’Meara, et al., 2024; Duan, Valmaggia, Fennema, Moll, & Zahn, 2023). Geographic information applicable to the eligible HMD samples is provided in 29 publications, with samples ranging from single-country cohorts to international pools. The widest explicitly reported eligible distribution includes participants from 32 countries (Pohl & Mottelson, 2022).
Figure 3 summarises the uneven reporting coverage across sample-composition variables, highlighting that geographic and broader sociodemographic information remains much less consistently reported than gender and age.
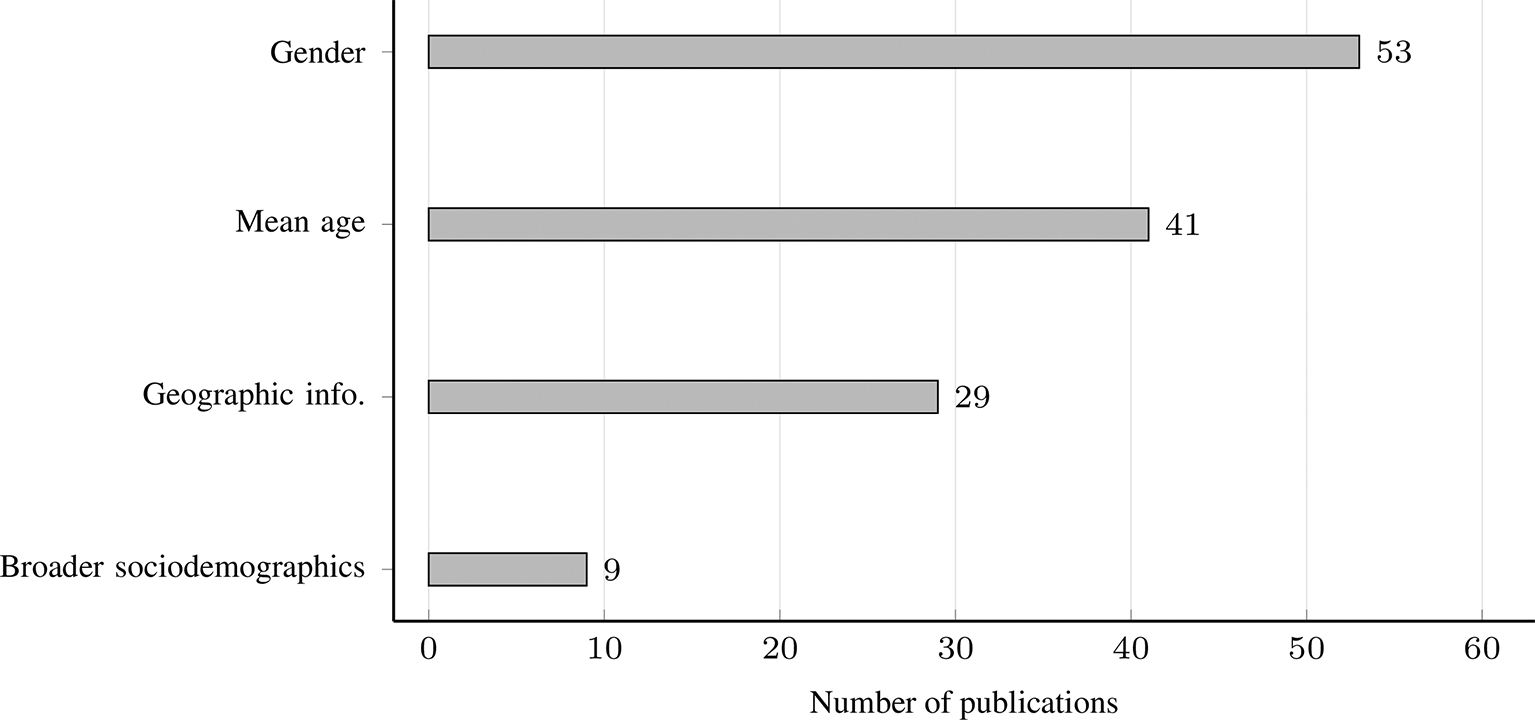
Figure 3. Reporting coverage for sample-composition variables.
Counts are publication-level reporting counts; broader sociodemographics refers to variables beyond age and binary gender.
3.2 Recruitment channels
Across the included studies, social media is the most commonly reported recruitment approach (54.1%), often through IVR-focused communities such as Reddit or VRChat. Other channels, including mailing lists or internal participant pools, are reported in 24 studies (39.3%). Online participant platforms are used in 13 studies (21.3%), with Prolific referenced most frequently. Recruitment method is not reported or not applicable in 10 studies (16.4%). Because recruitment categories are non-exclusive, some studies combine multiple recruitment strategies. Yet, none of the included publications reports the relative contribution of specific recruitment channels to sample size, sample composition, or dropout.
3.3 Access and delivery
We classified access and delivery using the classification described above, distinguishing how participants accessed an HMD from how they accessed the IVR study itself (
Table 1). Most publications use participant-owned HMDs (65.6%). Researcher-provisioned HMDs are used in 17 publications (27.9%), typically through loaned, shipped, laboratory-owned, or pre-configured devices. Four publications (6.6%) use mixed HMD access models.
Table 1. Access and deployment classification used to code remote IVR studies.
Glossary: PO = participant-owned HMD; RP = researcher-provisioned HMD; NA = native application; PL = existing IVR platform; WX = web-based immersive VR/WebXR; MX = mixed access or delivery.
| Native application (NA)
Installed standalone or PCVR application
| Existing IVR Platform (PL)
Study hosted on commercial IVR platform
| WebXR Study (WX)
Immersive browser-based study
|
Participant-Owned (PO)
Participant uses their own HMD and completes setup on their own
| PO-NA
Participant installs and launches a study-specific application
| PO-PL
Participant enters the study through an existing IVR platform
| PO-WX
Participant opens a browser-based IVR study |
Researcher-Provisioned (RP)
Research team supplies and configures the HMD before use
| RP-NA
Researcher provides an HMD with the study application installed
| RP-PL
Researcher provides an HMD set up to access an IVR platform
| RP-WX
Researcher provides an HMD set up to access the WebXR study
|
Study delivery is dominated by native applications, used in 45 publications (73.8%). Existing commercial or social IVR platforms account for 10 publications (16.4%), while browser-based immersive VR deployments, including WebXR, account for five publications (8.2%). One publication (1.6%) uses a mixed deployment route. When access and delivery are considered jointly, the dominant configuration is participant-owned HMD access with native application delivery, whereas researcher-provisioned, platform-based, and WebXR/browser-based combinations occur much less frequently. Native applications offer substantial control over the experimental application and data pipeline, but place installation, compatibility, and some safety burden on participants. Researcher-provisioned deployments can increase control over hardware and software configuration, but require additional logistical support, device management, and return procedures. Platform-based and browser-based routes can reduce installation burden, but may constrain interaction design, performance, compatibility, or access to behavioural data.
Figure 4 summarises the HMD access models, study delivery routes, and combined access–delivery codes across the included studies.
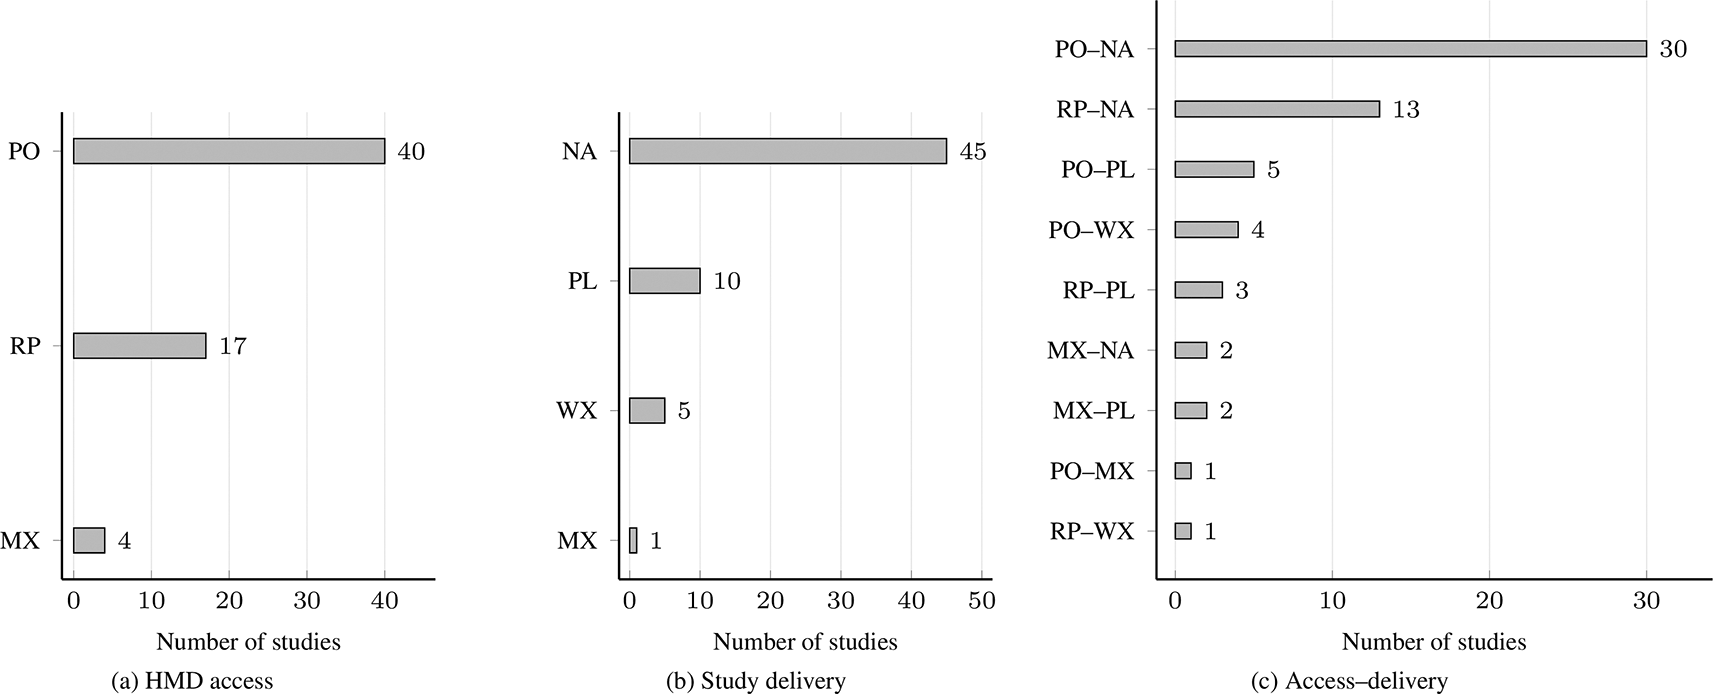
Figure 4. HMD access models, study delivery routes, and combined access-delivery codes across the included studies.
To assess whether browser-based deployment represents an emerging shift, we examined the publication-year distribution of browser-based/WebXR studies. Browser-based deployment remained uncommon overall, appearing in 5 of the 61 included publications. The temporal pattern does not indicate a clear monotonic increase across the 2015–2026 review window: browser-based/WebXR deployments appeared in 2018, 2020, 2023, and 2024, with two publications in 2023. Thus, the current evidence is too sparse to support a strong trend claim, but it suggests that WebXR is a visible alternative deployment route rather than a well-established shift away from participant-installed native applications.
3.4 Study design
Approximately 45.9% of studies examine behavioural questions related to perception, cognition, motor activity, or social interaction. The remaining 54.1% focus on feasibility and proof-of-concept objectives, evaluating remote usability, deployment workflows, or data quality.
Most reviewed studies are conducted without live researcher involvement: 67.2% are unsupervised, 29.5% are supervised, and 3.3% use a hybrid approach. Most studies are asynchronous (65.6%), whereas 31.1% are synchronous and 3.3% adopt a hybrid format. Hybrid studies comprise multiple experimental components, of which only some meet the present review’s remote-IVR inclusion criteria.
Figure 5 summarises these study administration modes.
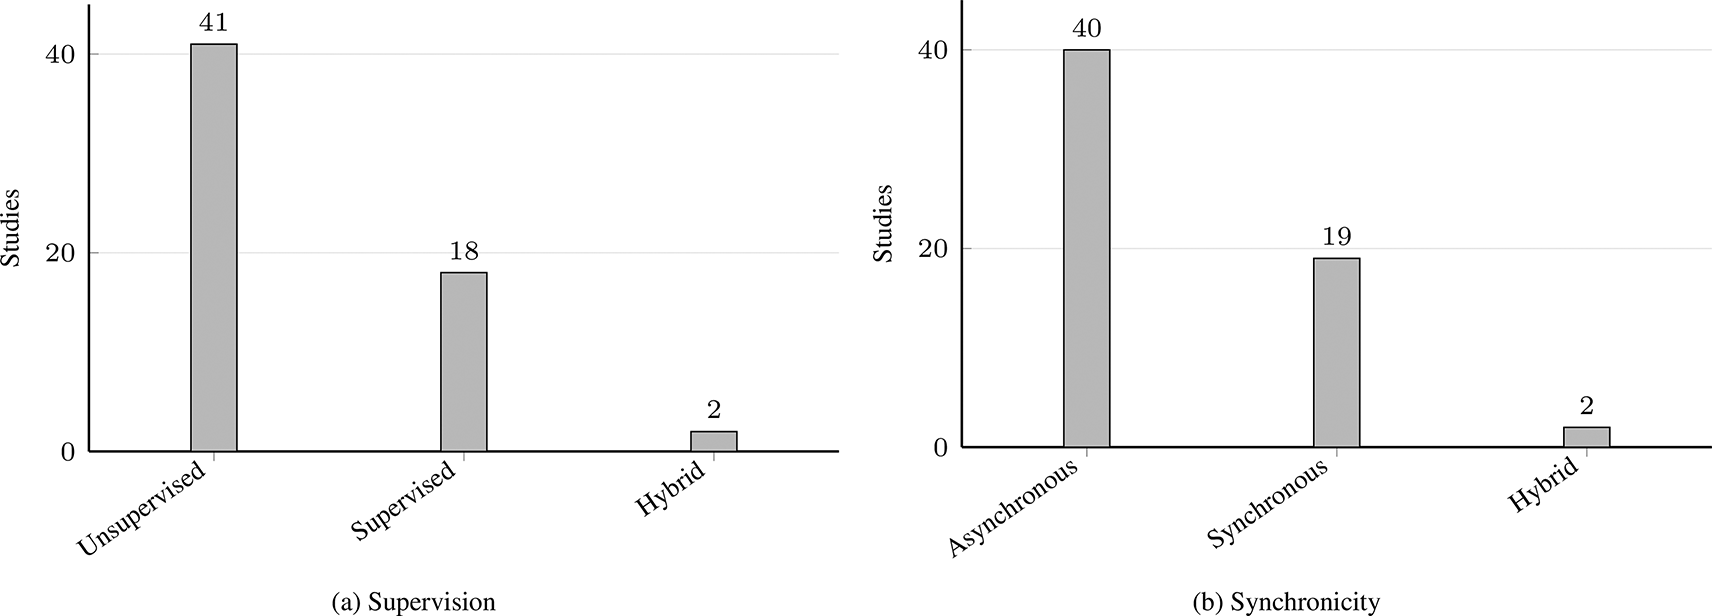
Figure 5. Study administration modes.
3.4.1 Task design and outcome measures
Ten task categories are identified (
Figure 6). Therapeutic/behavioural scenario engagement and strategic reasoning/cognitive process tasks are the most common categories, each appearing in 21.3% of included studies. Movement/spatial navigation tasks appear in 19.7% of included studies. Social interaction/collaborative problem solving and basic selection/pointing movements each appear in 18.0% of included studies. Complex object manipulation or procedural task execution accounts for 14.8%, while rapid response tasks account for 8.2%. Fine motor control and judgements of perceptual/sensory stimuli each represent 6.6%, while gesture elicitation and generation is the least frequent category at 4.9%. Several publications also incorporate more than one task category within a single experimental protocol.
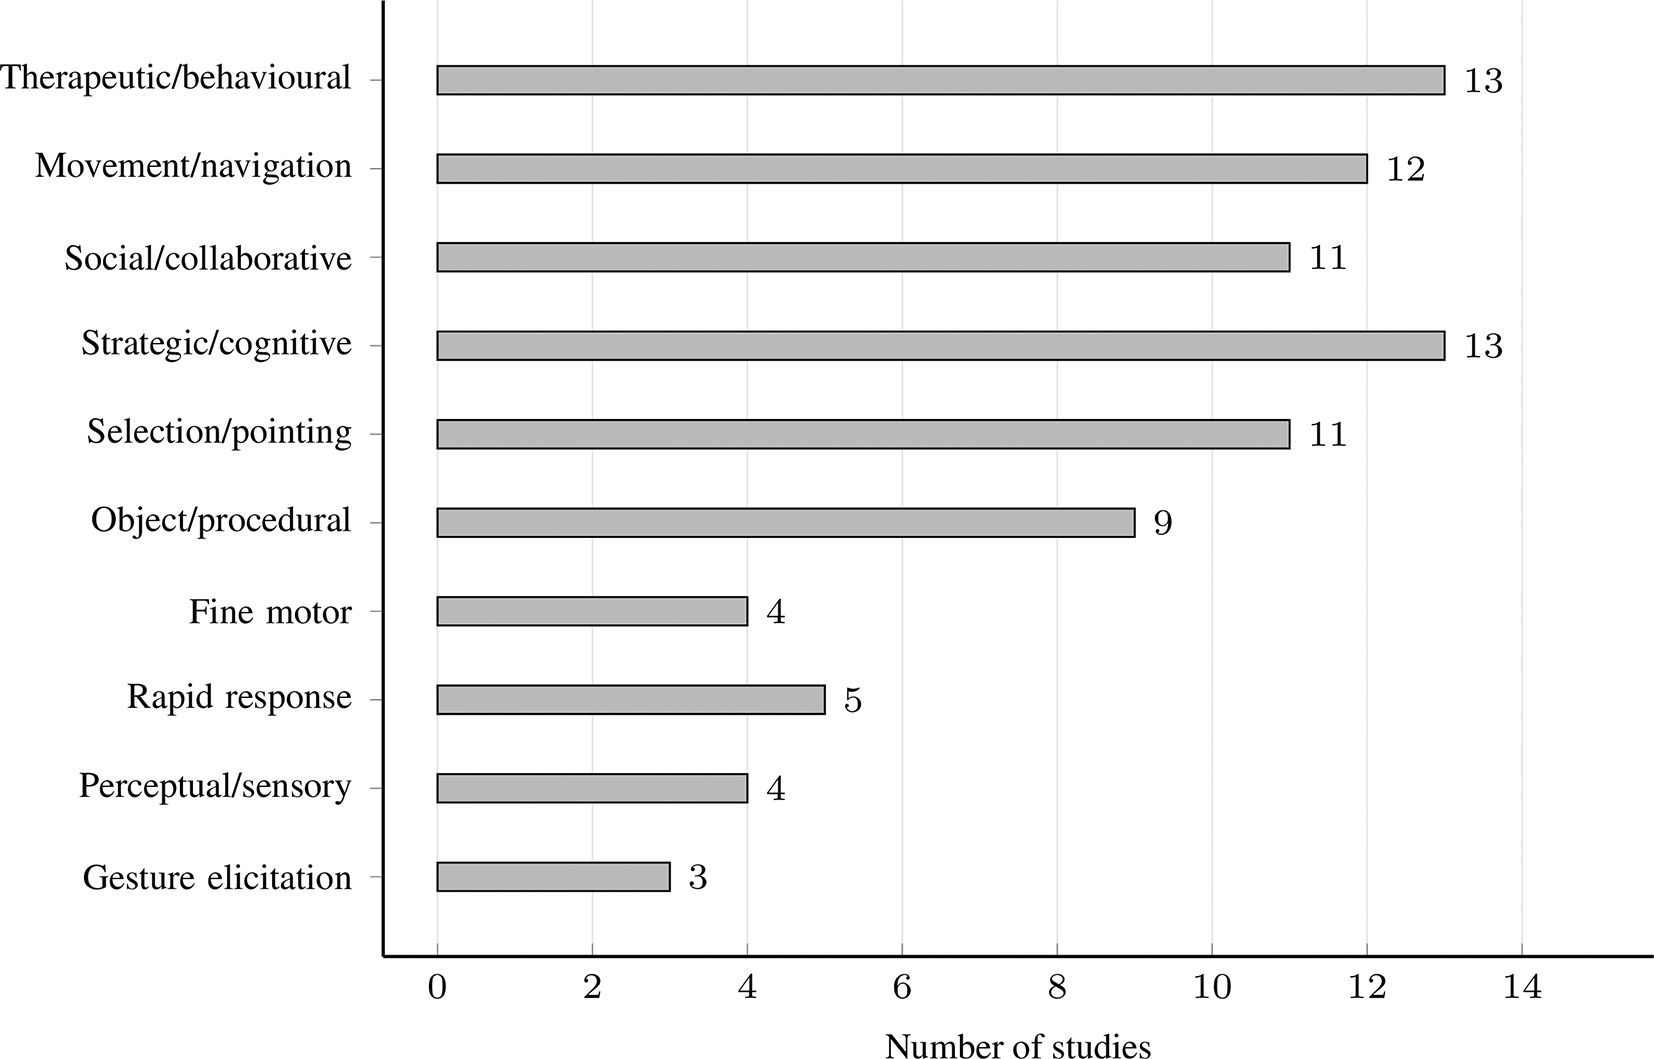
Figure 6. Task categories represented in the included studies.
Categories are non-exclusive because several studies used more than one task type.
Of the included studies, 44 report collecting behavioural data, while 17 studies (27.9%) do not report behavioural data. We divide the reported behavioural measures into seven categories (
Figure 7). Task performance & interface efficiency is the most common category, appearing in 29.5% of included studies. Spatial cognition & navigation measures account for 11.5% and include trajectories, path efficiency, and distance estimation, consistent with the prevalence of navigation-oriented tasks. Social interactions & collaboration outcomes and motor control & kinematics each represent 11.5% of included studies, capturing multi-user behaviour such as interpersonal distance, verbal exchanges, and collaborative coordination, as well as fine-grained movement measures such as reach angle, hand rotation, and gesture execution. Cognitive processing & affect accounts for 8.2%, while decision-making & real-world outcomes accounts for 6.6% and captures discrete choices or actions, often in response to moral dilemmas or persuasive interventions. Only 3.3% record physiological responses.
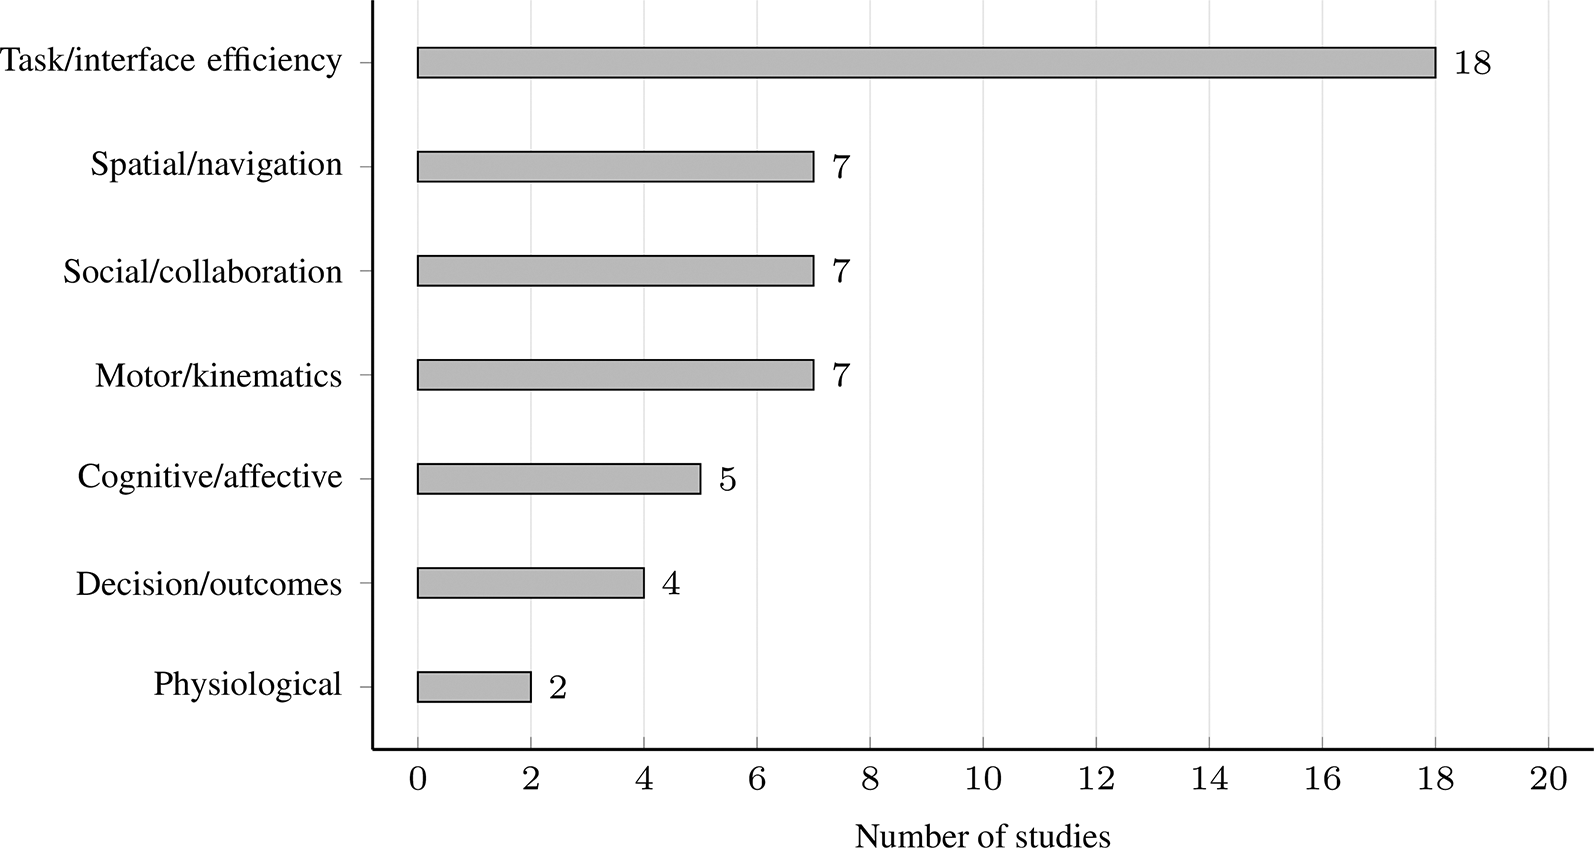
Figure 7. Behavioural outcome categories reported across the included studies.
Categories are non-exclusive and are shown as study-level counts.
Seven self-report domains are identified (
Figure 8). Demographic self-reports are most common (65.6%). Among outcome-relevant categories, usability & experience quality is the largest (55.7%). Emotional & affective states appear in 37.7% of included studies, cognitive load & self-assessment in 32.8%, and physical sickness & discomfort in 29.5%. Embodiment & self-identity appears in 23.0%, while attitudes, intentions, & external beliefs are less frequent, accounting for 11.5%.
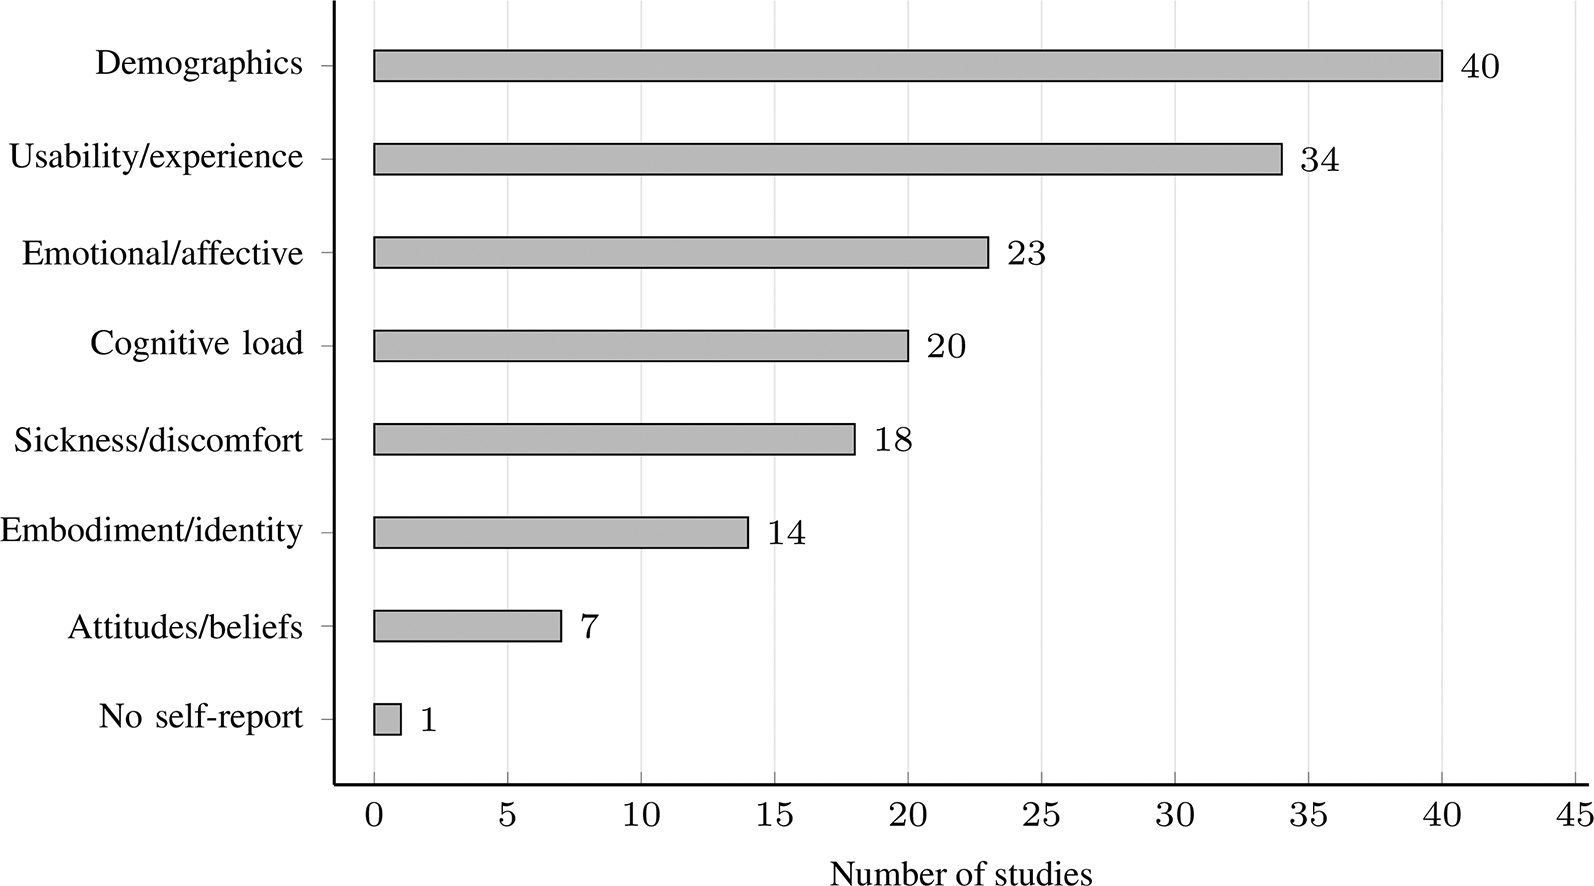
Figure 8. Self-report domains represented in the included studies.
Categories are non-exclusive except for the “no self-report measures” category.
3.5 Ethics
Reporting of ethical safeguards beyond informed consent is uneven. At least one such safeguard was coded in 28 of the 61 publications (45.9%). The most common additional measures are motion-sickness screening (e.g., Kissel, Rechowicz, & Shull, 2023; Loetscher, Jurkovic, Michalski, Billinghurst, & Lee, 2023; Ouverson, Jasper, Gilbert, Wilson, & Wu, 2021), physical-space guidance (e.g., Perera, Gedeon, Adcock, & Haller, 2021; Perera, Gedeon, Haller, & Adcock, 2023), adverse-effect monitoring (e.g., Clements, et al., 2023; Dresel & Jochems, 2021; Quirós-Ramírez, Feineisen, Streuber, & Reips, 2025), privacy-preserving data handling, and hardware verification, each reported in only a small number of studies. Structured debriefing or access to support resources is reported least often. This pattern suggests that ethics reporting in remote IVR remains centred on consent rather than on the distinctive risks of unsupervised immersive participation. These gaps are consequential because participants complete studies without in-person supervision, often in heterogeneous home environments and on different HMDs. In such settings, cybersickness, collisions, unsafe movement, technical failures, distressing content, and unclear withdrawal or support procedures cannot be managed immediately by an on-site experimenter. More consistent reporting of screening, spatial requirements, adverse-event procedures, privacy safeguards, hardware verification, and debriefing would therefore make it easier to assess whether remote IVR studies provide adequate protection as well as valid data.
4. Discussion
In this section, we highlight key findings of our review and identify emerging practices, gaps and future directions across essential steps of remote IVR research, including recruitment, access and delivery, procedures, measures and ethics.
Table 2 synthesises our discussion.
Table 2. Summary of key findings, emerging practices, gaps and future directions.
| Theme | Findings | Emerging practices | Gaps | Future directions |
|---|
| Recruitment
| Remote IVR can support scalable, geographically distributed data collection, but samples remain skewed. | Multi-channel recruitment; online participant platforms | Little evidence on the relative contribution of specific channels to sample size, sample composition, or dropout rates | Inclusion strategies and recruitment-channel comparisons |
| Access and delivery
| Participant-owned HMD access and native application delivery dominate; researcher-provisioned access, mixed access models, platform-based delivery, browser-based/WebXR delivery, and mixed delivery routes are less common. | Pre-configured HMDs, platform-hosted studies, WebXR/browser-based deployment | Access model and deployment route are often reported imprecisely | Report categories and compare routes by accessibility, dropout, data quality, control, and safety |
| Procedures
| Most studies are unsupervised and asynchronous. | Structured onboarding workflows, integrated workflows, hybrid support models | No common workflow models | Effects on dropout and data quality |
| Measures
| Self-reported data and performance-oriented metrics are most common. | Kinematic tracking, interaction logs, and multimodal biosensing | Limited use of rich behavioural and physiological data streams | Multimodal data collection |
| Ethics
| Additional ethical safeguards beyond informed consent are reported unevenly (28/61 publications; 45.9%). | Safety screening, physical space requirements, monitoring adverse effects, privacy-preserving data handling, structured debriefing | Sparse privacy and risk reporting | Evidence-based ethical guidelines |
To make these recommendations actionable, we propose a draft minimum reporting checklist for remote IVR studies. At minimum, authors should report: recruitment channels and channel-specific yields; participant demographics and geographic information; HMD access model and deployment route; headset model, hardware generation, software version, tracking setup, input modality, and mixed-reality use; onboarding, consent, calibration, training, task, questionnaire, and debriefing workflow; supervision and troubleshooting procedures; dropout, exclusions, and data-quality checks; behavioural, self-report, tracking, and physiological measures; and safety, privacy, cybersickness, spatial, adverse-event, and participant-support procedures.
4.1 Emerging practices
Several recurring practices appear promising for improving the feasibility, consistency, and robustness of remote IVR research.
•
Recruitment: Remote IVR studies commonly rely on multi-channel recruitment, often combining IVR-focused social media, online participant platforms, and other channels such as mailing lists or internal participant pools. These approaches support scalable recruitment while also broadening access beyond single-site laboratory samples. Only one publication develops and uses a dedicated participant panel of verified IVR users (Ma, Cackett, Park, Chien, & Naaman, 2018).
•
Access and delivery: Our classification clarifies that remote IVR requires two coupled decisions: how participants access an HMD and how they access the study. Participant-owned HMD access and native application delivery remain dominant, while researcher-provisioned access, mixed access models, existing IVR platforms, browser-based/WebXR deployments, and mixed delivery routes offer alternative balances between control, scalability, participant burden, and technical complexity.
•
Procedures: One notable practice is the use of systematic initial screening procedures to verify participants’ technical and environmental requirements for safe and effective participation. These approaches include brief tracking-quality tests that prompt participants to adjust their physical environment (Mottelson, Petersen, Lilija, & Makransky, 2021b) and photographic verification of headset ownership (Ma, Cackett, Park, Chien, & Naaman, 2018). Safety considerations are addressed similarly, with some studies applying exclusion criteria for relevant medical conditions, such as epilepsy or susceptibility to cybersickness, or specifying minimum spatial requirements as part of participant eligibility (e.g., Soave, Bryan-Kinns, & Farkhatdinov, 2022; Cummins & Schofield, 2023; Ouverson, Jasper, Gilbert, Wilson, & Wu, 2021; Perera, Gedeon, Haller, & Adcock, 2023). Several studies (e.g., Zhao, et al., 2021; Perera, Gedeon, Adcock, & Haller, 2021; Perera, Gedeon, Adcock, & Haller, 2025; Cesanek, Shivkumar, Ingram, & Wolpert, 2024) provide comparatively detailed onboarding workflows, offering structured written instructions, voice-assisted guidance, and in-VR demonstrations to support installation and training without researcher supervision, thereby lowering setup barriers and promoting more consistent task engagement across diverse home environments. Likewise, multiple publications adopt integrated workflows that embed consent, instructions, training, experimental tasks, and questionnaires into a continuous IVR- or web-based pipeline, helping reduce tool switching and supporting procedural continuity (Mottelson, et al., 2021a; Cummins & Schofield, 2023; Perera, Gedeon, Adcock, & Haller, 2021; Perera, Gedeon, Adcock, & Haller, 2025; Cesanek, Shivkumar, Ingram, & Wolpert, 2024). Offering a balance between scalability and participant support, a small number of publications implement hybrid support models that combine predominantly asynchronous participation with limited synchronous contact, such as brief intake calls or on-demand troubleshooting sessions (e.g., Quirós-Ramírez, Feineisen, Streuber, & Reips, 2025; Kroma, Al Kassm, & Teather, 2021; Kyian & Teather, 2021). Only one study introduces and deploys a dedicated experimental toolkit (Cesanek, Shivkumar, Ingram, & Wolpert, 2024).
•
Measures: Although consumer IVR systems provide access to rich behavioural and physiological data streams, few studies incorporate such measures into their analyses. Those that did utilise kinematic tracking, interaction logs, or multimodal biosensing to capture behavioural responses (e.g., Zhao, et al., 2021; Cesanek, Shivkumar, Ingram, & Wolpert, 2024; Perera, Gedeon, Adcock, & Haller, 2021). These examples indicate that remote IVR can support richer measurement strategies than are currently typical in the literature.
•
Ethics: Additional ethical safeguards beyond informed consent were reported unevenly: at least one such safeguard was coded in 28 of 61 publications (45.9%). Reported measures included motion-sickness screening (e.g., Kissel, Rechowicz, & Shull, 2023; Loetscher, Jurkovic, Michalski, Billinghurst, & Lee, 2023; Ouverson, Jasper, Gilbert, Wilson, & Wu, 2021), guidance regarding physical space requirements (e.g., Perera, Gedeon, Adcock, & Haller, 2021; Perera, Gedeon, Haller, & Adcock, 2023), and monitoring of adverse effects (e.g., Clements, et al., 2023; Dresel & Jochems, 2021; Quirós-Ramírez, Feineisen, Streuber, & Reips, 2025). More comprehensive practices, such as privacy-preserving data handling, hardware verification, structured debriefing, or access to support resources, were reported only infrequently, but they provide useful examples of how ethical safeguards can be extended in unsupervised settings.
4.2 Gaps
At the same time, the reviewed literature reveals persistent gaps in reporting, implementation, and evaluation that limit comparability and constrain methodological progress.
•
Recruitment: Reporting on recruitment practices remains limited. Although many publications identify the platforms used to recruit participants, they rarely specify the relative contribution of each channel or the demographic profiles associated with them. Consequently, it remains unclear whether the observed demographic skews reflect broader population-level patterns in remote IVR participation or biases introduced by specific recruitment methods. More generally, while age and gender are commonly reported, socioeconomic characteristics and geographic distribution are much less frequently included. This lack of demographic detail hinders assessment of sample representativeness.
•
Access and delivery: Despite the range of access and delivery models used in remote IVR, these details are often reported unevenly. Studies do not always specify headset access, installation route, software configuration, device constraints, or home-environment requirements in enough detail to support comparison or replication.
•
Procedures: Although several promising onboarding and workflow practices are visible, no common workflow models have yet emerged for remote IVR studies. As a result, studies vary substantially in how they organise consent, installation, calibration, task execution, questionnaire administration, and participant support. This makes it difficult to assess which procedural choices are most effective for reducing dropout, improving compliance, or maintaining data quality.
•
Measures: Behavioural data collection is concentrated in performance- and interaction-oriented metrics, whereas rich kinematic, cognitive, and physiological streams are reported less frequently. Self-reported outcomes are also common, with the strongest emphasis on usability and experience quality, affective states, and cognitive load, whereas embodiment-related measures and attitudinal or intention-based outcomes appear less often. Accordingly, current measurement practices do not yet fully exploit the multimodal data possibilities afforded by IVR.
•
Ethics: Additional ethical safeguards beyond informed consent are reported unevenly: at least one such safeguard was coded in 28 of 61 publications (45.9%). Few studies report safety screening, spatial requirements, or privacy protections. Consequently, current reporting provides little basis for assessing how researchers addressed the risks inherent in unsupervised IVR use. Sparse reporting on debriefing, adverse-event handling, and data protection further limits the field’s ability to evaluate whether existing ethical safeguards are adequate.
Taken together, these gaps point to a broader need for more standardised reporting of sample characteristics, recruitment processes, access and delivery conditions, procedures, measures, and ethical safeguards in remote IVR studies.
4.3 Future directions
Building on the emerging practices and identified gaps, several priorities can guide the design and evaluation of future remote IVR experiments.
•
Recruitment: Comparative studies are needed to determine whether current sample skews stem from recruitment channels, accessibility constraints, or broader population-level patterns in IVR usage. The generally young samples suggest limited representation of older adults, while socioeconomic characteristics and prior IVR experience were reported too inconsistently to determine how well lower-resource participants and IVR novices were represented. The dominance of participant-owned HMD access also raises an important accessibility question for future research. Procedural adaptations such as device loan schemes or simplified onboarding may broaden participation, but their effects on recruitment diversity have not yet been established in this literature. Future work should examine which interventions meaningfully broaden participation.
•
Access and delivery: Future studies should report both the HMD access model and the study deployment route, using this classification or a comparable reporting scheme. Direct comparisons are needed between participant-installed native applications, researcher-provisioned HMD deployments, platform-hosted studies, and WebXR/browser-based studies. These comparisons should examine accessibility, dropout, data quality, hardware compatibility, participant burden, researcher control, privacy, safety, and reproducibility. Future studies should also account for the development trajectory of consumer IVR hardware. As standalone headsets, hand tracking, and passthrough-based mixed reality become more common, remote IVR studies will face new forms of hardware heterogeneity. Researchers should therefore report headset model and generation, firmware or operating-system version, tracking setup, input modality, and whether mixed-reality features were used. These details are important for evaluating accessibility, calibration, task validity, data quality, privacy, safety, and comparability across devices.
•
Procedures: Integrating all components of the experiment (i.e., consent, instructions, calibration, task execution, questionnaires, and debriefing) into a single, continuous workflow can reduce dropout and minimise potential issues arising from participants having to navigate between multiple links or platforms. Researchers may also incorporate remote environment and device verification, for example in the form of brief calibration tasks. Monitoring dropout and compliance through built-in logging can help identify common failure points and support the continuous refinement of remote workflows. Studies with higher technical complexity may also benefit from hybrid support models, offering onboarding sessions or real-time troubleshooting while preserving the scalability of asynchronous participation. Future work should evaluate these procedural choices more systematically, particularly in relation to dropout and data quality.
•
Measures: Future studies would benefit from incorporating multimodal data collection, combining behavioural or sensor-based measures with self-report data. IVR enables access to high-resolution tracking, interaction logs, and physiological proxies, which can meaningfully complement subjective measures. Integrating complementary data streams can support triangulation and help mitigate the limitations of relying on any single measurement modality.
•
Ethics: Researchers should implement and report on systematic cybersickness and safety-screening procedures. Basic screening for relevant medical conditions, such as epilepsy or concussion, motion sickness susceptibility, and spatial constraints is both feasible and necessary in unsupervised IVR contexts. Simple safety checks integrated into the study workflow, such as confirming that participants have adequate space or providing brief reminders about safe movement, can help reduce risk while remaining unobtrusive to participants. More broadly, the field requires more comprehensive ethical frameworks for unsupervised IVR research. Empirical work examining participant risks, adherence to safety guidance, and the effectiveness of different protective measures would support the development of evidence-based ethical guidelines.
5. Conclusion
Remote IVR research has expanded considerably over the past decade, but this systematic review shows that the field remains methodologically heterogeneous. The core contribution of this review is a cross-disciplinary synthesis of how remote IVR studies are recruited, deployed, administered, measured, and ethically reported. We find substantial variation in recruitment channels, technical infrastructure, study procedures, task designs, outcome measures, and ethical reporting; only partial realisation of remote IVR’s potential to broaden participation, with clearer evidence of geographic reach than demographic representativeness; and limited reporting of safety and privacy practices beyond basic digital consent.
To support comparison across studies, we classified access and delivery arrangements by distinguishing how participants access an HMD from how they access the IVR study. This classification shows that remote IVR is currently dominated by participant-owned HMD access and native application delivery, while researcher-provisioned access, mixed access models, existing IVR platforms, browser-based/WebXR deployments, and mixed delivery routes represent smaller but important alternatives. At the same time, the reviewed studies demonstrate that remote IVR can support diverse behavioural paradigms and scalable, geographically distributed data collection. Several publications provide concrete methodological examples, including initial screening, structured onboarding, integrated workflows, hybrid support models, and richer behavioural measurement, that offer a practical foundation for improving the transparency, robustness, safety, and inclusiveness of future remote IVR research.
Several limitations of this systematic review must be acknowledged. First, our synthesis depends on the level of methodological detail reported in the publications themselves. Insufficient reporting may therefore have led to underestimation of the prevalence of some practices. Second, remote IVR research is distributed across multiple disciplines and uses inconsistent terminology, so some technically eligible studies may not have been retrieved. The executed search intentionally used NOT terms for rehabilitation, education, training, teleoperation, and collaboration to reduce large volumes of domain-specific intervention/application literature and maintain focus on remote experimentation; this choice may have reduced search sensitivity for otherwise relevant reports in those domains. Third, no formal study-level risk-of-bias, reporting-bias, or certainty-of-evidence assessment was undertaken because the synthesis focused on study conduct and reporting rather than comparative intervention effects. Finally, the rapid pace of consumer-IVR development means that the capabilities and constraints represented in the reviewed literature may not fully reflect current technology.
Registration and protocol
This systematic review was not registered, and no formal review protocol was prepared.
Ethics and consent
Ethical approval and consent were not required for this study because it is a systematic review based on previously published research.









