III. Study characteristics
A detailed overview of the primary empirical studies included in this systematic review is presented in Tables 1 and 2 (underlying data). The publication range of the 40 unique studies eligible for inclusion dates from 2007 to 2022. The majority (n=28/40)29–56 of studies assessed the sharing behavior of DTC-GT consumers (see Table 1) (underlying data), while 13 studies29,57–68 reported on the experiences of health care professionals with DTC-GT consumers sharing their test results (see Table 2 underlying data). Almost 90% of the identified records originated from research projects that were carried out by research teams based in the USA (n=35/40)15,28–47,49,50,52–55,57–59,61,63,64,66–71. Most studies used quantitative research methods (n=33/40)29,30,32–35,37,38,40–47,49,50,52–68, whereas a smaller number used qualitative (n=3/40)31,36,39 or mixed methods approaches (n=4/40)48,49,51,68. Most articles (n=21/28) included study participants who had paid out-of-pocket for their DTC-GT29,30,33,36,37,40–55. In contrast, three studies had provided a DTC-GT for free to study participants31,32,39 and ten had offered a DTC-GT at a subsidized rate as part of a research project34,35,38,40–42,44–46,56. Within the studies assessing sharing behavior of DTC-GT consumers, six articles were the result of the ‘Impact of Personal Genomics (PGen)’ where consumers of two DTC-GT companies (23andMe and Pathway Genomics) based in the USA were surveyed40–42,44–46 and three articles resulted from the American ‘Scripps Genomic Health Initiative (SGHI)’, which was a research project where study participants received the Navigenics Health Compass at a subsidized rate34,35,38. An overview of key characteristics of study participants from the primary studies included in this review is available as in Table 1 and 2 (Extended data).
IV. Main findings
A. Sharing behavior
Sharing behavior of DTC-GT consumers with health care professionals
A total of 28 studies reported study findings of research projects that had assessed the extent to which DTC-GT consumers shared their genetic test results with healthcare professionals, with the number of participants included in the studies ranging from 20 to 30385 (see Table 3A) (underlying data)29–56. The proportion of participants who shared their DTC-GT test results with a health care professional ranged from 1%32 to 57% (median=30%, IQR=11-41%)37. Overall, the rate of sharing appears to have remained relatively stable over the years. Between 2007 and 2011, the sharing rate ranged from 10% to 53%29,30. From 2012 to 2016, it fluctuated from 1% to 57%31–33,37,40– 44, and between 2017 and 2022, it ranged from 6% to 45%45,47–50,53–55. Among participants who paid out of pocket, the sharing rate ranged from 6% to 57%29,30,33,37,43,47–50,53–55. For those who received a subsidized test, the sharing rate was between 19% and 39%34,35,38,40–42,44–46,56, while participants who received a free test shared their results at a rate ranging from 1% to 42%31,32,39.
A more detailed analysis of the data on sharing behavior with specific healthcare professionals revealed that DTC-GT consumers most commonly reported sharing their results with a primary healthcare professional, with the proportion ranging from 8% to 78% (median=27%, IQR=20-39%)33,34,36,38,39,41,44–47,49–51,54,56. Interestingly, those that received a subsidized or free DTC-GT more often shared their DTC-GT with a primary health care professionals (range 27%–78%)34,38,39,41,44–46,56 compared to those that paid out of pocket (8–25%)33,36,47,49–51,54. To a lesser extent, data were shared with a trained genetic professional(median=2%, IQR=1-3%, range=1-3%))41,44,45,49 like a genetic counselor (median=4%, IQR=1-14%, range=0.4-19%)33–36,38,46,47,50,54 or a clinical geneticist (median=5%)36,50,54. Participants in the Scripps Genomic Health Initiative, where genetic counseling was provided at no cost by a Navigenics counselor and proactive outreach was conducted based on their test results, reported a slightly higher frequency of sharing their results with a Navigenics genetic counselor compared to participants in other studies that specifically examined sharing behavior towards trained genetic professionals34,35,71 (see Table 3A) (underlying data). Finally, some DTC-GT consumers also reported to have shared their DTC-GT results with other health care professionals (e.g. oncologist, nurse practitioner, etc.) (median=16%, IQR=7-17%, range=1-19%)33,36,41,44–47,49,50,52,54 (see Figure 2).
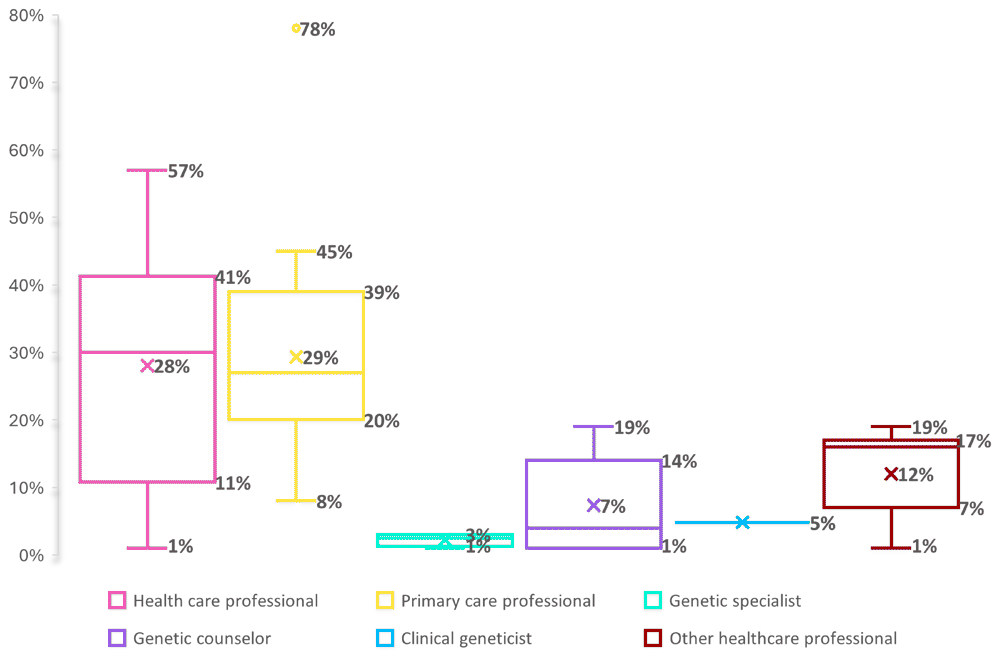
Figure 2. Sharing behavior of DTC-GT consumers with health care professionals.
* For the boxplots shown, the line inside the box indicates the median value, whereas the ‘x’ marks the mean.
* Categories are not mutually exclusive but were retained as defined in the original studies for consistency.
Motivations behind sharing behavior of DTC-GT consumers
Only a small proportion of the primary studies we identified examined the actual motivations behind DTC-GT consumers' sharing behavior (n=4/28)31,35,44,47. In the Scripps Genomic Health Initiative study, participants who were given the opportunity to consult a Navigenics counselor free of charge provided several reasons for utilizing the offered service35. These included the desire to take advantage of a free service, seeking additional information on risk calculations, the fact that they were actively contacted by a genetic counselor, seeking guidance on managing their health, the chance to discuss family history, and addressing a perceived lack of understanding regarding their genetic results. On the other hand, those who chose not to utilize the free genetic counseling service often felt they already had a clear understanding of their results and did not perceive a need for further explanation, or they planned to consult with the genetic counselor in the future35. Similar patterns were observed in a study by Gordon et al. (2012), where some DTC-GT consumers shared their results with their general practitioner in order to gain assistance with the interpretation of their DTC-GT results or to receive advice on how to reduce their risk, while others informed their general practitioner without expecting any follow-up or further testing. Other participants chose not to share their results, as they considered the information to be of limited relevance to their healthcare provider31. Another study by van der Wouden et al. (2016), reported that while many participants who discussed their DTC-GT results with primary care professionals or other health care professionals cited health improvement as a key motivation, a substantial proportion expressed concerns about the potential inclusion of genetic results in their medical records44. Furthermore, 42% of participants did not consider their results important enough to share, while 38% intended to discuss their results with a health care professional but had not yet done so due to time constraints44. Finally, in a study by Wang et al. (2017), the likelihood of sharing DTC-GT results with medical professionals was influenced by the consumers' reasons for using third-party interpretation services. Health-related motivations to use third-party interpretation services, including concerns about individual and family health, were found to be significantly associated with an increased likelihood of sharing results with healthcare professionals compared to ancestry-related motivations47.
Experiences of health care professionals with DTC-GT consumers sharing their test results
Our review identified thirteen studies that explored the experiences of healthcare professionals regarding patients who disclosed their DTC-GT results29,57–68 (see Table 3B) (underlying data). The proportion of health care professionals that had been asked questions about DTC-GT results varied, ranging from 19% to 76%. In a study by Goddard et al. (2007) 7% of primary care physicians and pediatricians aware of DTC-GT reported having at least one patient who discussed their DTC-GT results with them29. Similar low percentages (3–17%) were observed in other studies conducted between 2010 and 201257–61. In contrast, another study performed by Howard and Borry in 2013 found that 44% of European clinical geneticists (n=54/121) had seen at least one DTC-GT consumer for the sole purpose of reviewing DTC-GT results62. Most of these participants had been contacted by one to five patients with DTC-GT results62. A more recent American study revealed that 40% of genetic counselors had seen at least one DTC-GT consumer specifically for reviewing results67. Likewise, a study assessing physicians’ (primary and specialty care) experiences reported that 35% of participants had patients sharing their DTC-GT results within the past year63. Another American study, focusing on the experiences of genetic counselors with clinical cancer genetics as primary specialty, reported that 94% of study participants had encountered health-related DTC-GT results, and 69% had reviewed health-related third-party interpretation data66. More specifically, these study participants provided counseling for a median of 3 DTC-GT results in the last year66. In addition, McGrath et al. (2019) reported that 58% of specialists (genetic counselors and clinical geneticists) had experience with patients bringing their DTC-GT results compared to 17% within the group of primary care healthcare professionals surveyed within their study64 (see Table 3B) (underlying data). Finally, Millward et al. (2020) reported that 114 DTC-GT related referrals were received by 11 different Australian genetic services since 201065.
Sharing behavior of DTC-GT consumers with family members
Our search also identified twelve studies that assessed to what extent DTC-GT consumers had shared their genetic test results with their family members, with the number of participants ranging from 20 to 2947832,34,36,37,39,43,47,49,50,54,56,72 (see Table 4) (Underlying data). The percentage of participants sharing their DTC-GT test with family members ranged from 18%32 to 98% (median=83%, IQR=41-92%)53. More detailed analysis indicated that this was frequently the case with partners (median=30%, IQR=16-47%, range=6%-48%)32,36,43,48,50,54, parents (median=30%, IQR=20-31%, range=20%-31%)36,50,54, and siblings (18%–35%(mean=20%, IQR=18-35%, range=18%-35%)36,50,54. Sharing of test results with extended family members occurred less frequently (mean=3%, IQR=3-29%, range=3%-29%))36,50,54 (see Figure 3).
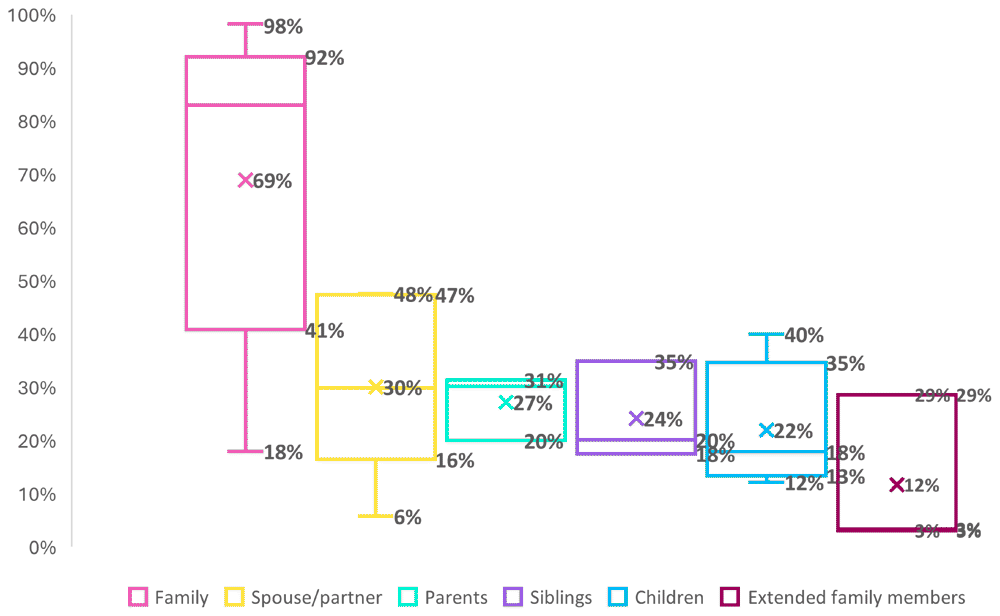
Figure 3. Sharing behavior of DTC-GT consumers with family members.
* For the boxplots shown, the line inside the box indicates the median value, whereas the ‘x’ marks the mean.
* Categories are not mutually exclusive but were retained as defined in the original studies for consistency.
B. Health care utilization
Overall, we identified 13 studies assessing healthcare utilization following DTC-GT, with a particular focus on the validation of DTC-GT results and subsequent clinical actions. An early study by Powel et al. (2012) found that four out of five primary care physicians who encountered patients bringing in DTC-GT results did not alter their patient’s medical management61. However, other studies did report on several instances of DTC-GT result validation and clinical actions performed based on the DTC-GT findings. Krieger et al. (2016) reported that 9% (n=55/617) of participants stated to have received additional genetic tests, medical exams, screenings, procedures, and/or scans as a result of the genetic information they had received through DTC-GT42. A similar result was reported by Lee et al. (2020) in a web-based survey among adult adoptees following DTC-GT. In this study 18% (n=5) of respondents received additional testing or procedures based on DTC-GT results53. A qualitative interview study by Francke et al. (2013) examined the experiences of 11 women who tested positive for BRCA through DTC-GT. Among them, one had undergone a prophylactic mastectomy, while three others had planned the procedure. Additionally, three had undergone oophorectomies, and four had planned to do so after completing childbearing. Five participants sought breast exams and imaging following their results, while seven participants who neither had nor planned to undergo mastectomies reported continuing regular breast cancer monitoring. Furthermore, 30 secondary BRCA tests were conducted on family members as a result of the initial DTC-GT result, either through a health care professional or 23andMe, yielding 13 positive and 17 negative results. In one mutation-positive secondary case, early-stage breast cancer was detected. Several family members with BRCA-positive results had already undergone prophylactic mastectomy and oophorectomy, while others indicated plans to pursue these risk-reducing procedures in the future36.
Jonas et al. (2019) reported that 40% of healthcare professionals (primary and specialty care physicians) who received DTC-GT results from patients made referrals to other healthcare professionals in the preceding year. Among these referrals, 78% were made to clinical geneticists and genetic counselors, while 22% were made to other health care professionals (e.g. clinical pharmacists)63. Trained genetic professionals also reported to have referred patients to other health care professionals in the study by Giovanni et al. (2010). In this study, 15 specialists in clinical genetics (n=15/22, 68%) had referred patients to at least one other health care professional57. In the Australian study conducted by Millward et al. (2020), which examined clinical genetics service referrals related to DTC-GT over ten years (2010–2019), there was considerable variation in the number of DTC-GT related referrals across the different publicly funded services surveyed65. While most services lacked specific procedures/guidelines for managing DTC-GT related referrals, six services reported that validating DTC-GT results was the most frequently performed clinical action following an appointment65. Overall, these services estimated that they had attempted to validate DTC-GT results for 34 patients, of which only 3 (9%) were confirmed as correct65. In the PGen study, 11% (n=105/961) of DTC-GT consumers stated to have undergone follow-up tests, examinations, and procedures based on their DTC-GT results six months after obtaining their test results45. A similar finding was also reported by Kaufman et al. (2012) where on average 10% of DTC-GT consumers reported following up their results with additional laboratory tests. This percentage was higher among those participants who had shared their DTC-GT test results with a health care professional (26%) compared to those who did not (2%)33. Interestingly, 27% of participants in the SGHI research study reported that their physicians had ordered additional tests based on the DTC-GT results they received34. Another American study by Elson et al. (2020) explored the outcomes of receiving DTC-GT results for the two most common genetic risk factors for venous thromboembolism (Factor V Leiden and prothrombin 20210G>A). In this study, 21% of variant-positive individuals were advised by health care professionals to undergo repeat genetic testing in a clinical lab, 13% were advised to have additional testing for other clotting disorders, and 15% were recommended to have relatives tested. About 28% (n=82/294) of cases reported that their relatives also underwent genetic testing based on their DTC-GT results. Within this group, 34% (n=28/82) reported that their family members received genetic testing through a healthcare professional and 17% (n=14/82) through a combination of DTC-GT and a health care professional50. In another study by Koop et al. (2021), six participants indicated to have pursued evaluation with a specialist in hereditary hemochromatosis (HH) due to their positive DTC-GT result. Additionally, three participants saw a HH specialist because a family member tested positive on commercial DNA testing for HH. Three participants also stated that a primary care physician ordered additional genetic testing due to a positive DTC-GT result, with one participant receiving conflicting results from formal gene testing52. Finally, in the study by Ashenhurst et al. (2022), 26.4% of participants with a physician-diagnosed Alpha-1 antitrypsin deficiency (AATD) received their diagnosis only after receiving their 23andMe test results and 50% of individuals with a PI*ZZ genotype (identified through DTC-GT) had received a diagnosis of AATD by a physician54.








