Introduction
The use of digital technologies have transformed the ways in which information is access and shared, driving the development of the contemporary digital landscape. In this context, adolescents' use of social media platforms has become a common avenue for accessing and sharing personal health-related information (Hausmann et al., 2017; Moreno et al., 2018). Adolescents worldwide increasingly engage with online platforms as sources to search and discuss information related to health, marking a significant shift in their information-seeking behaviours as discussed by Gray et al. (2005) and Skinner et al. (2003). Adolescence marks a pivotal stage for establishing lifelong health habits (Patton et al., 2016), and as such, understanding their health information-seeking behaviours in various contexts is important. Studies show that adolescents engage and respond well to tailored digital education programs targeting health-related behaviour such as physical activity in Australia (Caillaud et al., 2022) and the Pacific Islands (Galy et al., 2019).
The Pacific Islands Countries and Territories (PICTs) consist of 22 islands in the world's largest region, the South Pacific (Craig et al., 2022). Over several decades, there has been a rapid socio-economic transition in the South Pacific region, characterised by modernisation, urbanisation, increased imports, and the digitisation of urban, peri-urban, rural, and tribal areas (Bertrand-Protat et al., 2024; Galy et al., 2020; Wattelez et al., 2024a). The process of digital transition within these PICTs has taken time to unfold (Cave, 2012). Presently, there is a need to understand the relationship between adolescents and their use of media and digital environments. Literature addressing this topic is limited, with little evidence in the Pacific Islands. In countries like New Caledonia, a high number of digital devices are available in households with wide disparities across urban and rural areas related to the ongoing digital development of the country (Nedjar-Guerre et al., 2023). However, little is known about the use of digital technologies for health information by adolescents in Vanuatu, particularly comparing urban and rural areas.
With over 80 islands, Vanuatu is home to an estimated population of 328,928 people (https://worldpopulationreview.com/countries/vanuatu). Linguistically diverse, English, French and Bislama are the official languages spoken but also have 138 indigenous Oceanic languages (Crowley, 2000). The interaction between traditional practices and contemporary influences shapes the health experiences of the adolescent population in Vanuatu. Like many adolescents around the world, adolescents in Vanuatu engage with the Internet, social networking sites, and other mobile app technology, making digital technology a promising avenue for health. However, unlike adults, adolescents may still be in the process of accumulating the skills necessary to gather and evaluate reliable health information online (Taba et al., 2022). As such, the importance of their digital health literacy emerges as a pivotal factor for cultivating positive adolescent health and well-being outcomes. Digital health literacy represents the capacity to proficiently navigate health-related information and resources within digital environments (Oddone & Merga, 2025; Schulenkorf et al., 2021) and warrants attention to address contemporary health challenges among this Pacific demographic. However, before this, it is crucial to gain insight into the current state of their online activities and behaviours related to health. Gaining insight into the patterns of use and purposes behind their engagement with online platforms for health-related information enables the development of effective educational initiatives and interventions that are tailored to their needs and preferences. This approach ensures that efforts to enhance digital health literacy are relevant and impactful for adolescents.
Access to, and the use of, digital technologies vary across urban, rural, and tribal areas. With higher population density and greater investment, urban areas generally have better access to healthcare services, digital infrastructure, and technology. Adolescents in these areas can benefit from a wider range of digital health tools, including mobile health apps and online health information resources. The challenge lies in ensuring the quality and reliability of the information accessed (Swire-Thompson & Lazer, 2020), as well as addressing issues related to data privacy and security (Razi et al., 2020). Additionally, adolescents living in urban areas may face different health issues compared with their rural and tribal counterparts, necessitating tailored digital health (literacy) interventions (Jacobs, 2020; Miller et al., 2018).
For adolescents living in rural areas, digital health technologies can bridge the gap caused by geographical isolation (Wang et al., 2011). Telehealth services, for instance, can enable adolescents to access medical consultations without the need for long and often difficult travel to urban centers. However, the digital divide remains a significant barrier, with limited availability or access to resources and infrastructure for reliable internet connectivity in combination with limited digital literacy posing challenges to the effective use of technologies (Ji et al., 2024; Watson & Fox, 2021; Ye & Yang, 2020). Efforts to improve infrastructure and provide digital education are crucial to maximising the benefits of digital health solutions in these regions.
Furtherstill, residents in tribal areas present a unique context where traditional practices and beliefs play a significant role in healthcare. Integrating digital health technologies in these areas requires a culturally sensitive approach that respects and incorporates traditional health practices (Galy et al., 2022). Community engagement and collaboration with tribal leaders are essential to foster trust and acceptance of digital health solutions. Digital tools may be used to document and preserve traditional health knowledge, creating a valuable resource for both current and future generations.
This study therefore aims to explore the health information-seeking behaviours of adolescents in Vanuatu and identify their preferred online platforms for fulfilling these needs. Recognising the unique cultural and contextual factors in Vanuatu, this study aims to shed light on how adolescents living in urban areas compared with those living in rural areas navigate online resources to make informed health decisions. To address this aim, data from the current study will be analysed to answer which websites, social media platforms or apps, were
i) their favourite to use for health,
ii) used to search for health information, and
iii) used to discuss health topics.
By understanding their approach to seeking health information, we aim to bridge gaps in understanding and potentially tailor interventions that resonate with the specific needs of adolescents in Vanuatu, contributing to the advancement of their overall health outcomes.
Methods
Setting
This study was a part of the European Family Farming, Lifestyle and Health in the Pacific (FALAH) project (n° 873185) (Fotsing & Galy, 2019). As such, Ethics approval for FALAH projects including fields of research in Fiji, New Caledonia, Solomon Islands, and Vanuatu was obtained from the Consultative Ethics Committee of New Caledonia (CCE 2018-06 001 and 2023-10 012). This study was conducted in accordance with the requirements of the Declaration of Helsinki (World Medical Association [WMA], 2024).
Vanuatu archipelago is located in the South Pacific Ocean and consists of more than 80 islands. The two schools involved were selected based on the following criteria: (1) location, i.e. rural/urban; (2) island location, i.e. Esperitu Santo/Efate (amongst the most populated islands); (3) class grades, i.e. from levels/years 9 to 11; and (4) sufficient student numbers in the targeted class grades (n ≥ 150). The study was authorised by the Vanuatu Ministry of Education and the selected schools were contacted to present the research design to the staff in charge of the establishment. Before data collection, potential student participants and their parents were given written information about student involvement and details of the research study. This provided them an opportunity to opt out of participation in the study.
Procedure and participant sample
School recruitment. To understand the cultural context, members of the University of Sydney research team travelled to Vanuatu in October, 2022. During this trip, they visited two schools which were identified through existing connections with the FALAH network of international scientific teams (https://falah.unc.nc/en). During the school visits, research team members met with the principals and deputy principals and explained the details of the research study and the delivery of the project workshops. The meeting included discussions about the school curriculum and student environment to understand the educational context and a tour of the school grounds. Following the initial meeting, the principals reached out to the research team about their interest in involving their students. From this visit, both schools signed up to participate in the study.
Data collection. In June 2023, members from the University of Sydney and the University of New Caledonia research teams travelled to Vanuatu to run the project for data collection. The classes and students at each school were selected based on teacher interest and consent to participate in the study.
A participant information template was sent home with the students, providing parents with information about the study, and an opportunity to opt-out of the study if they did not want their child to participate. If no signed note was returned, it was understood as consenting to involvement in the study. For parents who were living in remote, isolated islands and were unable to sign and return the forms due to illiteracy, we obtained verbal consent from community authorities (directors, teachers, and Kustom leaders). In research, consent is sought from both parents and adolescents for studies involving vulnerable populations, including young people. However, in Vanuatu when parents are not available, such as in the case of students residing in boarding schools or living in remote islands, in line with local customs it is common practice that a representative of authority (for example a teacher, school director, or Kustom leader) can approve the ethical aspects of the study. The principals of the participating schools provided consent to involve their students in our study. In instances where written consent was not feasible, oral or verbal consent was accepted. The students whose parents did not opt them out of the study, had consent from community authorities, but did not want to participate, verbally expressed this to their teacher or a research team member and were free to leave the classroom without participating in the study. All adolescents provided individual written consent through the submission of the online survey.
Students completed a questionnaire either offline via a REDCap mobile app on digital tablets or online via the same REDCap questionnaire on a computer in a classroom. The questionnaire collected both quantitative and qualitative data. Depending on the student’s preferred language, the questionnaire could be completed in either French or English. It is recognised that these languages may not be the student’s first language, which is likely to be Bislama, however, it was a requirement that they could read and write in either French or English, as taught in their school curriculum. During the completion of the questionnaire, teaching staff and researchers remained in the classroom in the event students required support to better understand any of the questions. To minimise bias in the administration of the questionnaire, the teachers were instructed that they were allowed to provide definitions of any words within the questionnaire that the participant may not have understood, but were asked not to provide any examples that may suggest answers to the questions.
Data analysis
This study is a part of a larger research project aiming to better understand the lifestyle and behaviours of adolescents living in the PICTs and mainly focused on physical activity, diet and the use of digital technologies (Galy et al., 2024a; Galy et al., 2024b). Selected questions from the digital technology component of the questionnaire about the use of digital technology were adapted from an Australian survey (Armstrong et al., 2021) and from a previous study conducted in New Caledonia that explored the impact of digital screen time on unhealthy food consumption (Nedjar-Guerre et al., 2023). Results from the New Technologies and Medias and Digital Tools and Health sections of the questionnaire were analysed and this study presents the descriptive statistics and qualitative findings of digital technology use for health by adolescents living in Vanuatu.
Quantitative data. The use of digital tools was assessed through the following closed questions: 1) When you are on the computer and/or tablet, what type of actions do you most often performs? 2) When you are on the mobile phone, what type of actions do you most often perform? and 3) Do you use apps, social media or websites for your health? Responses to these questions, as well as the open questions that were categorised, are presented with percentages and shown with barplots.
Qualitative data. Within the survey, the following open questions were used to better understand participants’ use of digital tools regarding health information: (1) “Which social media platform/site is your favourite to use for health? And what do you like about it?”, (2) “For searching health information, which app, social media or website do you use?” and (3) “For discussing health topics, which app, social media or website do you use?” Participants were able to provide more than one response if they used more than one platform.
Where required, responses were first translated from French to English and then a simple content analysis was performed. Responses were assigned an open code that named the platform in that response. Similar codes were grouped together under axial codes. These were then grouped together under a category with a descriptive heading. For example, the axial codes “Facebook”, “TikTok” and “YouTube” were grouped together under the category “Social Media”, and axial codes “Google” was grouped with “Chrome” under a “Search engine” category. KA and GW reviewed all coding and discussed the final codes. There were no disagreements requiring further discussion.
This study employed a descriptive cross-sectional design to explore adolescents’ use of online platforms for health in Vanuatu. Given the limited number of participants who reported engaging with digital health tools, inferential statistical analysis was not pursued, as subgroup comparisons would not yield reliable or generalisable results. The aim was to provide foundational insights into digital health engagement in a context with minimal prior research.
Results
Participants
A total of 245 participants were recruited from two schools in Vanuatu. Of these, 197 participants completed the questionnaire. Participants were aged between 14 and 20 years, with 97% aged between 14 and 18 years. Majority of participants from both locations were female (62% in the urban school and 66% in the rural school; Table 1).
Table 1. Number of participants according to school location and sex.
| Number of
participants | Average age (sd) |
|---|
| Urban | 114 | 16.3 (1.27) |
| Female | 63 | 16.1 (1.23) |
| Male | 51 | 16.4 (1.32) |
| Rural | 83 | 15.4 (0.82) |
| Female | 53 | 15.4 (0.78) |
| Male | 30 | 15.5 (0.91) |
Device use
A total of 79.8% (n= 91) of participants from the urban location and 72.3% (n= 60) from the rural area reported to have owned a mobile phone. From this, 25.3% (n= 23) of participants from the urban location and 6.6% (n= 4) from the rural location shared the phone with other people.
Of the activities conducted on a computer or tablet, 43% of the participants identified “listening to the music” as the most performed, followed by completing “homework” (39%), “viewing videos” (30%), and “playing games” (29%). The least performed activities conducted by participants on a computer or tablet were “watching social network feed” (6%), “discussion” (8%), and “other” (8%), which were not specified (Figure 1).
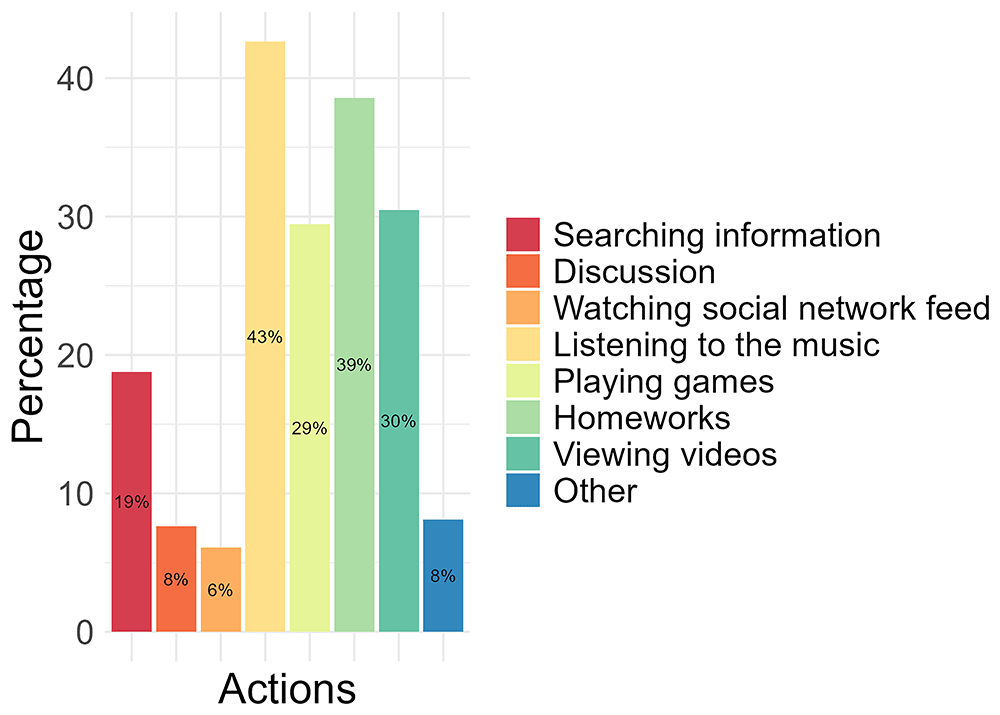
Figure 1. The most performed activities conducted on the computer and/or tablet by participants.
Of the activities conducted on a mobile phone, 34% of the participants identified “listening to the music” as the most performed, followed by completing “playing games” (22%), “viewing videos” (20%), and “homeworks” (19%). The least performed activities conducted by participants on a mobile phone were “watching social network feed” (7%), “discussion” (6%) and “other” (4%), which were not specified (Figure 2).
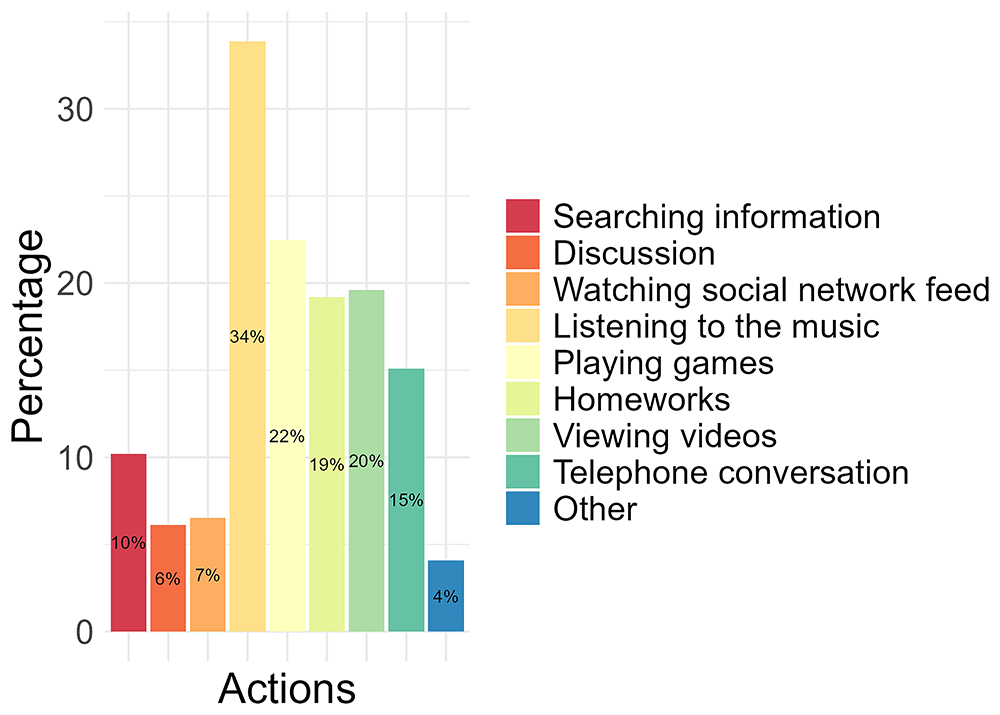
Figure 2. The most performed activities conducted on the mobile phone by participants.
Only 24% (n = 47) of the total number of participants reported to have used apps, social media or websites for their health. When analysed based on location, more participants from the urban location reported to have used apps, social media or websites for their health (29%, n= 33) (Figure 3).
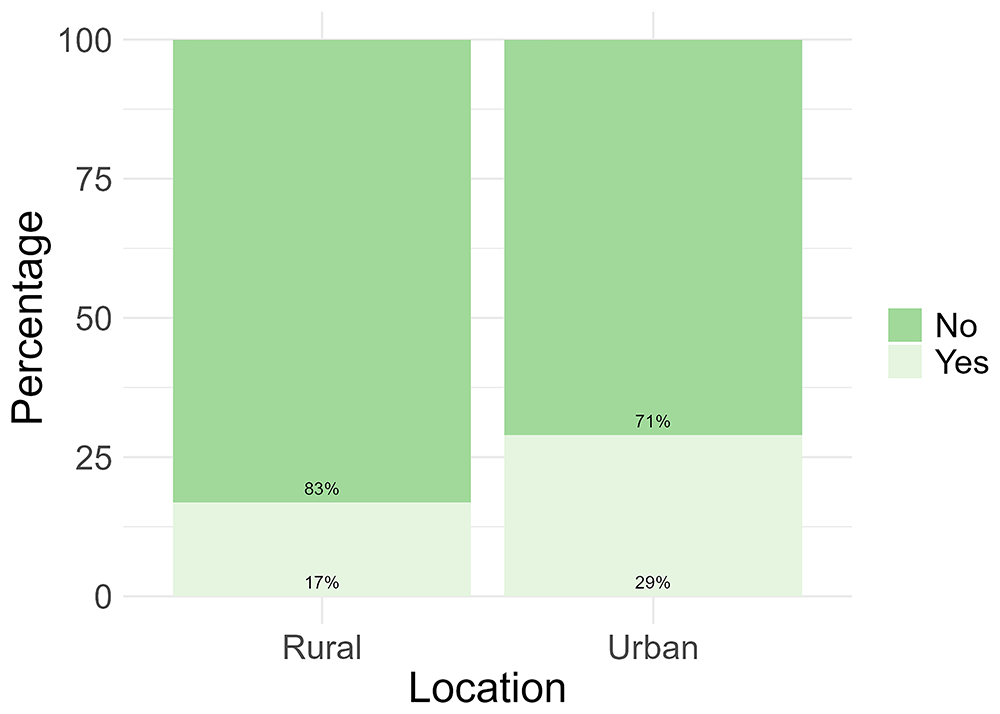
Figure 3. Participant use of apps, social media, and websites for health information by location.
Qualitative analysis
Of the 197 number of total participants who completed the questionnaire, 24% of participants reported that they used apps, social media, or websites specifically for their health. Due to the small number of respondents in this subgroup, results are presented descriptively without stratification by demographic variables. This approach was chosen to avoid overinterpretation and to maintain the integrity of the exploratory nature of the study.
To find out which platforms were: i) their favourite to use for health, ii) used to search for health information, and iii) used to discuss health topics, participants were asked open-ended questions and a simple content analysis was performed (see Supplementary Tables 1–3 in the Appendix). The following results present the qualitative findings from the urban and rural areas.
Favourite online platforms to use for health. When asked the question “Which social media platform/site is your favourite to use for health? And what do you like about it?”, 38 participants (n= 29; 25% from urban and n= 9, 11% from rural locations) reported the use of online platforms including Facebook (n= 20), TikTok (n= 16), YouTube (n= 5), Instagram (n= 2), and Twitter (n= 1) (Figure 4a) which was grouped together under the “social media” category as the participants' favourite (Figure 4b). A total of 3% (n= 3) of urban location responses and 1% (n= 1) of rural location responses also included “Google” (n= 3) and “Chrome” (n= 1), and was grouped together under the “Search engine” category. Responses categorised under “Unclear” (1%, n= 1, from urban and 4%, n= 3 from rural) included responses which could not be translated into English or did not explicitly name a platform or website to answer the question (Figure 4). From these responses, only 7 included reasons what they liked about these platforms. Reasons were summarised and categorised into “Gain knowledge” (71%, n= 5), “Watch videos” (43%, n= 3), and “Other” which included to “chat with friends” and “look at posts” (29%, n= 2). Two responses (1 from urban and 1 from rural) were empty with no text response despite indicating they used social media platforms or websites for health.
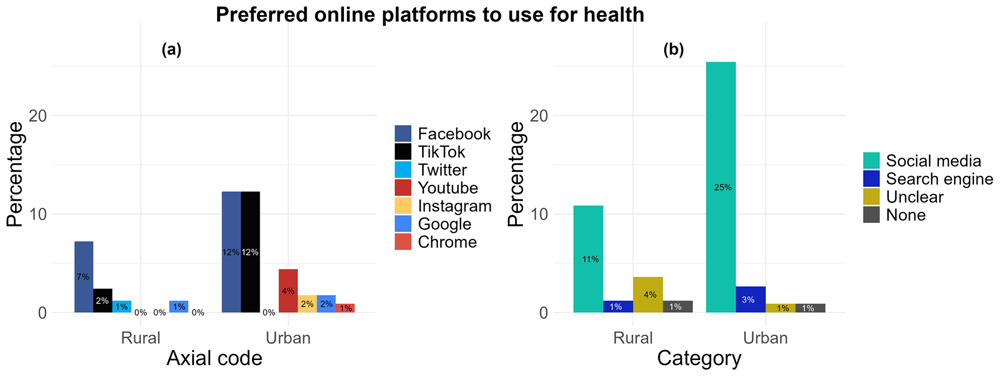
Figure 4.
Comparing rural and urban participant preferences for using online platforms for health: (a) aggregation by axial code, (b) aggregation by category.
Online platforms used to search for health information. Following analysis of the question “For searching health information, which app, social media or website do you use?” responses grouped together under the “social media” category was found to be the most used in the rural area (12%, n= 10) compared with the urban area (8%, n= 9) (Figure 5b). The platforms grouped into the social media category included Facebook (n= 9), TikTok (n= 3), YouTube (n= 7), and a broad ‘social media’ response (n= 3) (Figure 5a), as reported by 19 participants. The most used in the urban area was found to be “search engines” (12%, n= 14) compared with the rural location (5%, n= 4). Responses for these included “Google” (n= 16), “Chrome” (n= 1) and “I’m usually looking for, regardless of the website” [translated from: “Je cherche en générale, peut importe le site”] (n= 1). Only one participant from the urban location (1%) responded with “websites”. There were 2 responses from the urban location that could not be translated into English or did not explicitly name a platform or website, and were categorised under “Unclear” (2%). Participants from both the urban (6%, n= 7) and rural (1%, n= 1) locations indicated responses but either did not type a response or responded with “I don’t use” despite stating they used social media platforms or websites for health, but may not use it specifically to search health information (Figure 5).
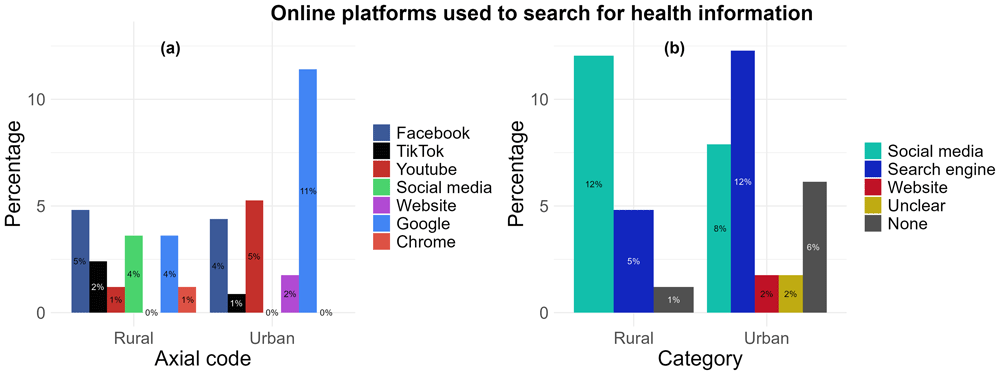
Figure 5.
The preferred use of types of online platforms by rural and urban participants’ to search for health information: (a) aggregation by axial code, (b) aggregation by category.
Online platforms used to discuss health topics. When asked the question “For discussing health topics with other people online, which app, social media or website do you use?”, a total of 19 participants from both urban (10%, n= 11) and rural (9%, n= 8) locations reported the platforms Facebook (n= 13), Instagram (n= 1), Twitter (n= 1), YouTube (n= 2), Snapchat (n= 1), and a broad ‘social media’ response (n= 2) (Figure 6a) which was grouped together under the “social media” category (Figure 6b) as their most used. Two responses from the urban location (2%) and one response (1%) from the rural location were categorised under “Search engine” and these included “Google” (n= 3) responses. Only three participants in the urban location (3%) identified “Apps” and these included chat apps including “Messenger” (n= 2) and a “Food network” (n= 1) responses. “Website” was also identified by three participants from the rural location (4%). There was only one response (1%) which was categorised under “Unclear” and included a response that could not be translated into English from the urban location. Participants from both the urban (15%, n= 17) and rural (2%, n= 2) locations provided responses which either did not type a response or responded with “I don’t use” despite stating they used social media platforms or websites for health, this may suggest they do not use it to discuss health topics (Figure 6).
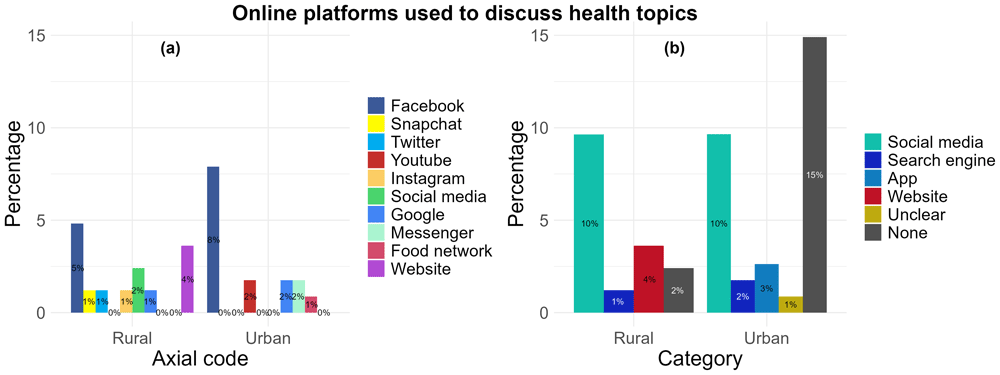
Figure 6.
Types of online platforms preferred by rural and urban participants to discuss health topics: (a) aggregation by axial code, (b) aggregation by category.
Discussion
Our study collected 197 completed questionnaires from adolescents in Vanuatu regarding their engagement with digital technology for health-related purposes. However, only 24% of participants reported using apps, social media, or websites for their health. Despite comprising a minority within the surveyed population, the significance of this subset cannot be understated. And whilst the study is descriptive in nature, it offers valuable data on digital health engagement among adolescents in Vanuatu, a population largely absent from existing literature. While reports often suggest a digital divide between urban and rural areas, the results from our study challenge this notion. Our current findings demonstrate that of the participants who reported having used digital technology for their health indicated similar responses across both urban and rural areas, suggesting that with access, there may not be a digital divide.
The analysis of findings from these adolescents reporting the use of digital technologies for their health holds importance as it provides insights into the health information-seeking behaviours of adolescents in Vanuatu. Understanding the preferences identified by this group serves as a pivotal point for targeted strategies to assist them with making appropriate health decisions. Tailoring educational initiatives, and resources to align with the needs and preferences of this population is required for effective engagement of digital and online health tools and positive health outcomes.
Influencing factors of social media use for health-related purposes by adolescents in Vanuatu
As children move from primary to secondary levels in school, tablets and mobile phones are the preferred device (Rich et al., 2020). The type of device used plays a crucial role in shaping how adolescents in Vanuatu engage with health-related digital content. Smartphones are likely the most commonly used devices due to their portability and multifunctionality, allowing adolescents to easily watch videos, interact with online communities and access social media and other health apps. In this study, the participants used their mobile phones mostly for music-related activities and less likely to search for information or use social media. Computers and tablets, while less portable, offer a larger screen that enhances the length and viewing experience of content consumption. Completing homework was the second most reported activity to be conducted on these devices in the current study, following music-related activities. These entertainment and education-oriented activities appear to take priority over proactive health-information seeking and may help explain the low levels of engagement with using digital technologies for health-related information and engagement in our study. This is similar to findings from recent research (Black Dog Institute, 2024; Rich et al., 2020). Listening to music (78%) and watching videos (72%) were in the top three activities (following socialising on social media, 85%) conducted on their smartphone or tablet by young people aged 11–18 years in South West England (Rich et al., 2020). The device type can also affect the format of content that adolescents prefer. Short videos and quick updates particularly on social media platforms are more suited to smartphones, while websites and documents might be better viewed on tablets or computers. Whilst previous research found 71.48% of 270 health-related webpages were mobile-friendly, only 15.93% of them were designed in a way to optimise readability (Cheng & Dunn, 2017). The dissemination of health information through mobile phones, however, have been shown to be a health-promotion strategy that is useful and convenient (Cilliers et al., 2018), with young people reported mobile phone use for seeking out information, advice and learning about health and illness, mental health and wellbeing, and physical fitness (Rich et al., 2020).
Previous studies have shown that online search engines and websites were the most common tool to use to actively search for health information (Freeman et al., 2018; Gazibara et al., 2024). In this current study, when asked about what online platforms they used to search for health information, the use of search engines was more popular to search for health information in the urban location compared with the rural location, where rural participants preferred to search health information through social media platforms. Social media platforms, including Facebook, TikTok, and YouTube, were also identified as the favourite to use for health-related activities and discussing health topics as identified by adolescents from both urban and rural areas. This aligns with current literature that adolescents from other regions use social media platforms to access health-related information, including topics such
as healthy lifestyle behaviour (nutrition, physical activity, weight management, sleep), mental health, sexual health, substance use, and specific medical conditions (Armstrong et al., 2021; Rich et al., 2020). Popular platforms including Facebook, Twitter (now known as X), and YouTube act as accessible reservoirs of diverse knowledge, and serves as a space for peer interaction and social support, empowering adolescents with important health information (Moreno et al., 2018; Rich et al., 2020). Fostering a sense of community engagement, social media enables adolescents to share personal health experiences, practices and solutions within a digitally interconnected space. These findings have leveraged the potential social media has as a platform to delivering health interventions, with positive findings (Alvarez-Jimenez et al., 2020; Amon et al., 2022).
These findings were revealed by only a quarter of the total participants, however, this may be influenced by multifaceted factors that are characteristic of the Pacific Islands. Whilst there were no specific differences in use between rural and urban locations, the limited accessibility of internet infrastructure, coupled with socioeconomic disparities may significantly impact the opportunity to use digital technologies for these purposes. In addition, the amalgamation of traditional cultural norms with the current digital landscape shapes the acceptance and credibility of health information that is disseminated through these online platforms. The interactive nature of these platforms encourages open dialogues, enhancing health literacy and promoting discussions around taboo health topics in a culturally sensitive manner (Chen, 2023). Understanding these multifaceted and complex connections is crucial for a comprehensive understanding of adolescent use of social media for health-related purposes within the Vanuatu context.
Cultural sensitivity
Culture may affect health by shaping and influencing habits and behaviours related to precursors of health, development of disease, and by controlling their physical environment (Fleisher et al., 2013). Interpretations of health and illness may vary with different cultural groups and ultimately inform why some cultural groups may choose to adopt or not adopt preventative health behaviours. Thus, health education materials need to be culturally appropriate. An important component of culture is language, and the impact of language on minority subgroups differs based on social and demographic characteristics. A lack of understanding of written English or French is a barrier that can cause misunderstandings that lead to inappropriate health decisions (Sauni & Neal, 2012).
The rapid dissemination of potentially culturally insensitive information is of concern. Vanuatu is culturally diverse which amplifies the susceptibility to misinterpretation of health-related content available online, and the lack of digital health resources in local languages can limit the reach and effectiveness of health initiatives.
Risks
Misinformation. Whilst social media serves as a means to access health information by adolescents in Vanuatu, it is unregulated which presents potential risks of misinformation (Suarez-Lledo & Alvarez-Galvez, 2021; Swire-Thompson & Lazer, 2020). Taba et al. (2022) explored the relationship between adolescents’ self-efficacy and digital health literacy, emphasising the critical role these factors play in navigating online health information. Thus, while adolescents increasingly turn to social media for health-related information, their ability to discern credible sources from misinformation is often limited by their digital health literacy skills, emphasising the risk of misinformation, particularly in contexts like Vanuatu, where digital literacy education may be less prevalent. While participants in our study reported the use of TikTok as one of their favourites to use for health, Merga’s (2025) systematic review cautions that the platform’s entertainment-driven content and inconsistent credibility may pose risks to adolescent digital health literacy, particularly when health advice is delivered by influencers rather than qualified professionals. Adolescents with higher self-efficacy and better digital health literacy are more adept at evaluating the trustworthiness and relevance of online health content, thereby reducing their susceptibility to misinformation. Therefore, there is a need for targeted educational interventions and policies to enhance digital health literacy among adolescents, ensuring they can safely and effectively use social media for health information.
Exposure. There is evidence of passive health information exchange via social media (Raeside et al., 2022). Findings from this current study show that adolescents in Vanuatu engage in several other activities on their devices. Thus, even if an adolescent is not actively searching for health-related information, their presence on online websites and social media leaves them open to a variety of unsolicited unhealthy promotional content. This exposure can significantly influence adolescents’ health behaviours and perceptions. Potvin Kent et al. (2024) found that youth exposed to digital marketing of unhealthy foods, including fast food and sugary drinks, were more likely to consume these foods and more frequently. The constant exposure to promotional content can lead to increased consumption of unhealthy foods, contributing to poor dietary habits and related health issues. This highlights the importance of developing digital health literacy skills to help adolescents critically evaluate the online health information they encounter, whether intentionally sought or not. According to Oddone and Merga (2025) there is a role school library professionals and educators can take in the development of adolescents’ critical evaluation skills, which include questioning source credibility, recognising misinformation, and identifying fake expertise, to mitigate the risks. Without adequate digital literacy skills, adolescents are more susceptible to the persuasive tactics of digital marketing, which can exacerbate unhealthy behaviours and the risk of misinformation. Instead, equipping adolescents with these skills can empower them to safely navigate digital health spaces and responsibly make informed decisions about their wellbeing.
The role of policy and education
Policy and education play a crucial role in shaping adolescents’ use of social media for health-related purposes. There is a required focus on equipping adolescents with the digital literacy skills needed to critically evaluate health information encountered online, consequently reducing the risk of misinformation (Taba et al., 2022; Wendt et al., 2023). Educational interventions, both within school settings and through community-based programs, play a significant part. For example, integrating digital literacy into the school curriculum can help students develop the necessary competencies to navigate the digital landscape effectively, whilst also providing them with free connectivity access. Also providing school staff such as onsite school nurses with such skills as additional resources. Additionally, community workshops and campaigns led by non-government organisations can provide practical guidance on identifying credible sources and understanding the potential impacts of social media on health behaviours. By fostering a supportive environment that encourages informed and responsible social media use, these policy and educational efforts can significantly influence adolescents’ health outcomes. Further still, ongoing evaluation and adaptation of these programs are essential to address the evolving digital habits and health needs of adolescents in Vanuatu.
Limitations and future research directions
This study serves as an important direction to determine the online activities conducted by adolescents to access health information and communicate about health topics, between urban and rural areas in Vanuatu. Future research could explore cross-cultural comparisons of digital health behaviours among adolescents across Pacific Island nations, highlighting both shared challenges and culturally distinct approaches. A limitation of this current study is the low number of participants who completed the open-ended questions, which may affect the generalisability of the findings. Future research with a greater number of participant responses would provide a more comprehensive understanding by identifying more online platforms, apps, and specific websites and yield more detailed insights into the patterns and preferences of adolescents in this context, further identifying any differences between the urban and rural settings, and would also ensure that the sample is more representative of the broader population. With a greater number of participants, attention to gendered experiences using digital technologies for health, particularly around sensitive health topics, may also reveal nuanced vulnerabilities and coping strategies. To address these challenges, developing community-led interventions that center around cultural relevance, and adolescent agency may help build more inclusive and responsive digital health ecosystems, which involve an interconnected network of people, platforms, and policies that facilitate health communication and access through digital technologies.
The scarcity of region-specific studies underscores the importance of our contribution, offering preliminary insights into a population that remains underrepresented in digital health and youth engagement research. We advocate for future studies to expand the evidence base in this area, particularly those that explore culturally nuanced perspectives and age-specific experiences across Pacific Island communities.
Conclusion
This study contributes to the growing body of research on adolescent digital health practices by indicating that adolescents in Vanuatu engage with digital technologies, to access and share information on health-related topics. However, there exists a noticeable gap in research concerning their specific information needs and patterns of use, particularly within the Vanuatu context. Amongst the range of digital sources available to them, adolescents from both urban and rural locations in Vanuatu reported a preference for the use of social media, namely Facebook, TikTok and YouTube, as their primary means to access health information and discuss health issues. Since these platforms also display content that is not evidence-based and may be harmful to young people with inadequate health literacy, these initial findings are instrumental in informing future research shaping tailored initiatives and furthering our understanding of digital health trends among adolescents in Vanuatu. These findings also highlight the need to integrate digital health literacy resources into educational curricula, thereby contributing to the advancement of knowledge and skills within this population. Future research must explore cross-cultural comparisons of digital health behaviours among adolescents across Pacific Island nations, highlighting both shared challenges and opportunities for innovative health engagement strategies that are culturally grounded.
Ethics and consent
This study was a part of the European Family Farming, Lifestyle and Health in the Pacific (FALAH) project (n° 873185) (Fotsing & Galy, 2019). As such, Ethics approval for FALAH projects including fields of research in Fiji, New Caledonia, Solomon Islands, and Vanuatu was obtained from the Consultative Ethics Committee of New Caledonia (CCE 2018-06 001 and 2023-10 012). This study was conducted in accordance with the requirements of the Declaration of Helsinki (World Medical Association [WMA], 2024).
A participant information template was sent home with the students, providing parents information about the study, and an opportunity to opt-out of the study if they did not want their child to participate. If no signed note was returned, it was understood as consenting to involvement in the study. For parents who were living in remote, isolated islands and were unable to sign and return the forms due to illiteracy, we obtained verbal consent from community authorities (directors, teachers, and Kustom leaders). In research, consent is sought from both parents and adolescents for studies involving vulnerable populations, including young people. However, in Vanuatu when parents are not available, such as in the case of students residing in boarding schools or living in remote islands, in line with local customs it is common practice that a representative of authority (for example a teacher, school director, or Kustom leader) can approve the ethical aspects of the study. The principals of the participating schools provided consent to involve their students in our study. In instances where written consent was not feasible, oral or verbal consent was accepted. The students whose parents did not opt them out of the study, had consent from community authorities, but did not want to participate, verbally expressed this to their teacher or a research team member and were free to leave the classroom without participating in the study. All adolescents provided individual written consent through the submission of the online survey.
Data availability
The data that support the findings of this study are openly available in Zenodo (open – Creative Commons Attribution 4.0 International – CC-BY 4.0). Exploring the Digital Health Landscape: How adolescents living in urban and rural Vanuatu use online platforms to access health information (anonymized version). DOI: 10.5281/zenodo.17154763 (https://zenodo.org/records/17154763) (Wattelez et al., 2025).
Data are available under the terms of the Creative Commons Attribution 4.0 International
Restricted version of the data that support the findings of this study are available in Zenodo (restricted). Exploring the Digital Health Landscape: How adolescents living in urban and
rural Vanuatu use online platforms to access health information (non-anonymized version). DOI: 10.5281/zenodo.14323390 (https://zenodo.org/records/14323390) (Wattelez et al., 2024b)
For ethical reasons, the restricted data is not freely open because the data has not been anonymized. The risk of reidentification is not negligible. However, within reason, authenticated Zenodo users can request access to the data by contacting the authors through the Zenodo website, or by sending a direct email to dirlire@unc.nc. The authors will consider all serious requests. A basic condition to access to this dataset will be to certify that the requester complies with the European General Data Protection Regulation (GDPR) and the data will not be used to identify individuals.
Data are available under the terms of the Creative Commons Attribution 4.0 International
Faculty Opinions recommendedReferences
- Alvarez-Jimenez M, Rice S, D’Alfonso S, et al.:
A novel multimodal digital service (Moderated Online Social Therapy+) for help-seeking young people experiencing mental ill-health: pilot evaluation within a national youth e-mental health service.
J Med Internet Res.
2020; 22(8): e17155. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Amon K, Ridout B, Forsyth R, et al.:
Online group counseling for young people through a customized social networking platform: phase 2 of kids helpline circles.
Cyberpsychol Behav Soc Netw.
2022; 25(9): 580–588. PubMed Abstract
| Publisher Full Text
- Armstrong M, Halim NK, Raeside R, et al.:
How helpful and what is the quality of digital sources of healthy lifestyle information used by Australian adolescents? A mixed methods study.
Int J Environ Res Public Health.
2021; 18(23): 12844. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Bertrand-Protat S, Wattelez G, Frayon S, et al.:
Encouraging physical activity in Pacific children, an effective way to prevent childhood obesity? Pilot study in schools in Wallis and Futuna.
Public Health.
2024; 36(HS2): 71–81. PubMed Abstract
| Publisher Full Text
- Black Dog Institute:
Adolescent screen use and mental health: summary findings from the future proofing study. 2024. Reference Source
- Caillaud C, Ledger S, Diaz C, et al.:
iEngage: a digital health education program designed to enhance physical activity in young adolescents.
PLoS One.
2022; 17(10): e0274644. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Cave D:
Digital islands: how the Pacific’s ICT revolution is transforming the region.
Lowy Institute for International Policy.
2012; 21(1): 1–24. Reference Source
- Chen X:
Online health communities influence people’s health behaviors in the context of COVID-19.
PLoS One.
2023; 18(4): e0282368. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Cheng C, Dunn M:
How well are health information websites displayed on mobile phones? Implications for the readability of health information.
Health Promot J Austr.
2017; 28(1): 15–20. PubMed Abstract
| Publisher Full Text
- Cilliers L, Viljoen KL, Chinyamurindi WT:
A study on students' acceptance of mobile phone use to seek health information in South Africa.
Health Inf Manag.
2018; 47(2): 59–69. PubMed Abstract
| Publisher Full Text
- Craig AT, Beek K, Gilbert K, et al.:
Universal health coverage and the Pacific Islands: an overview of senior leaders’ discussions, challenges, priorities and solutions, 2015–2020.
Int J Environ Res Public Health.
2022; 19(7): 4108. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Crowley T:
The language situation in Vanuatu.
Current Issues in Language Planning.
2000; 1(1): 47–132. Publisher Full Text
- Fleisher L, Davis SN, Jibaja-Weiss M, et al.:
Best practices in culturally appropriate health education approaches. In: Kinsey P.J., and Louden, D.M. (Eds.) Health, ethnicity, and well-being: an African American perspective. Xlibris Corporation LLC: USA, 2013; 199–237. Reference Source
- Fotsing JM, Galy O:
Family Farming Lifestyle and Health in the pacific project. (hal-03150691), 2019. Reference Source
- Freeman JL, Caldwell PHY, Bennett PA, et al.:
How adolescents search for and appraise online health information: a systematic review.
J Pediatr.
2018; 195: 244–255.e1. PubMed Abstract
| Publisher Full Text
- Galy O, Caillaud C, Frayon S, et al.:
Questionnaire tools used with adolescents in FALAH project (1.0.0).
Zenodo.
2024a. http://www.doi.org/10.5281/zenodo.14031903
- Galy O, Caillaud C, Frayon S, et al.:
Outils du questionnaire utilisé avec les adolescents impliqués dans le projet FALAH (1.0.0).
Zenodo.
2024b. http://www.doi.org/10.5281/zenodo.14183635
- Galy O, Frayon S, Goldin M, et al.:
Generational issues in linking family farming production, traditional food in diet, physical activity and obesity in Pacific Islands countries and Territories: the case of the Melanesian population on Lifou Island [version 2; peer review: 2 approved].
Open Res Eur.
2022; 1: 135. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Galy O, Paufique E, Nedjar-Guerre A, et al.:
Living in rural and urban areas of New Caledonia: impact on food consumption, sleep duration and anthropometric parameters among Melanesian adolescents.
Nutrients.
2020; 12(7): 2047. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Galy O, Yacef K, Caillaud C:
Improving Pacific adolescents’ physical activity toward international recommendations: exploratory study of a digital education app coupled with activity trackers.
JMIR Mhealth Uhealth.
2019; 7(12): e14854. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Gazibara T, Cakic M, Cakic J, et al.:
Familiarity with the internet and health apps, and specific topic needs are amongst the factors that influence how online health information is used for health decisions amongst adolescents.
Health Info Libr J.
2024; 41(3): 283–297. PubMed Abstract
| Publisher Full Text
- Gray NJ, Klein JD, Noyce PR, et al.:
Health information-seeking behaviour in adolescence: the place of the internet.
Soc Sci Med.
2005; 60(7): 1467–1478. PubMed Abstract
| Publisher Full Text
- Hausmann JS, Touloumtzis C, White MT, et al.:
Adolescent and young adult use of social media for health and its implications.
J Adolesc Health.
2017; 60(6): 714–719. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Jacobs M:
Rural adolescent health: issues, behaviors and self-reported awareness.
J Community Med Health Solut.
2020; 1: 001–017. Publisher Full Text
- Ji H, Dong J, Pan W, et al.:
Associations between digital literacy, health literacy, and digital health behaviors among rural residents: evidence from Zhejiang, China.
Int J Equity Health.
2024; 23(1): 68. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Merga MK:
Tiktok and digital health literacy: a systematic review.
IFLA Journal.
2025; 51(2): 490–501. Publisher Full Text
- Miller B, Baptist J, Johannes E:
Health needs and challenges of rural adolescents.
Rural Remote Health.
2018; 18(3): 4325. PubMed Abstract
| Publisher Full Text
- Moreno MA, Standiford M, Cody P:
Social media and adolescent health.
Curr Pediatr Rep.
2018; 6: 132–138. Publisher Full Text
- Nedjar-Guerre A, Wattelez G, Serra-Mallol C, et al.:
Adolescent screen time and unhealthy food consumption in the context of the digital development in New Caledonia.
PLoS One.
2023; 18(5): e0285374. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Oddone K, Merga M:
Evaluation strategies of school students accessing health information in social media videos: a case study investigation.
J Libr Adm.
2025; 65(2): 214–234. Publisher Full Text
- Patton GC, Sawyer SM, Santelli JS, et al.:
Our future: a Lancet commission on adolescent health and wellbeing.
Lancet.
2016; 387(10036): 2423–2478. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Potvin Kent M, Bagnato M, Remedios L, et al.:
Child and adolescent exposure to unhealthy food marketing across digital platforms in Canada.
BMC Public Health.
2024; 24(1): 1740. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Raeside R, Jia SS, Redfern J, et al.:
Navigating the online world of lifestyle health information: qualitative study with adolescents.
JMIR Pediatr Parent.
2022; 5(1): e35165. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Razi A, Agha Z, Chatlani N, et al.:
Privacy challenges for adolescents as a vulnerable population. Networked Privacy Workshop of the 2020 CHI Conference on Human Factors in Computing Systems. April 26, 2020. Publisher Full Text
- Rich E, Lewis S, Lupton D, et al.:
Digital health generation? Young people's use of 'healthy lifestyle' technologies. 2020. Publisher Full Text
- Sauni P, Neal T:
Digital health literacy in commonwealth Pacific nations. Published by Commonwealth of Learning, 2012. Reference Source
- Schulenkorf T, Krah V, Dadaczynski K, et al.:
Addressing health literacy in schools in Germany: concept analysis of the mandatory digital and media literacy school curriculum.
Front Public Health.
2021; 9: 687389. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Skinner H, Biscope S, Poland B, et al.:
How adolescents use technology for health information: implications for health professionals from focus group studies.
J Med Internet Res.
2003; 5(4): e32. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Suarez-Lledo V, Alvarez-Galvez J:
Prevalence of health misinformation on social media: systematic review.
J Med Internet Res.
2021; 23(1): e17187. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Swire-Thompson B, Lazer D:
Public health and online misinformation: challenges and recommendations.
Annu Rev Public Health.
2020; 41: 433–51. PubMed Abstract
| Publisher Full Text
- Taba M, Allen TB, Caldwell PHY, et al.:
Adolescents’ self-efficacy and digital health literacy: a cross-sectional mixed methods study.
BMC Public Health.
2022; 22(1): 1223. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Wang JY, Bennett K, Probst J:
Subdividing the digital divide: differences in internet access and use among rural residents with medical limitations.
J Med Internet Res.
2011; 13(1): e25. PubMed Abstract
| Publisher Full Text
| Free Full Text
- Watson AHA, Fox R:
Digital divide: mobile internet speeds in the Pacific.
Pacific Journalism Review.
2021; 27(1/2): 215–231. Publisher Full Text
- Wattelez G, Amon KL, Forsyth R, et al.:
Self-reported and accelerometry measures of sleep components in adolescents living in Pacific Island countries and Territories: exploring the role of sociocultural background.
Child Care Health Dev.
2024a; 50(3): e13272. PubMed Abstract
| Publisher Full Text
- Wattelez G, Amon K, Nedjar-Guerre A, et al.:
Exploring the Digital Health Landscape: how adolescents living in urban and rural Vanuatu use social media to access health information (non-anonymized version)(1.0.0). [Data set].
Zenodo. 2024b. http://www.doi.org/10.5281/zenodo.14323390
- Wattelez G, Amon K, Nedjar-Guerre A, et al.:
Exploring the Digital Health Landscape: how adolescents living in urban and rural Vanuatu use social media to access health information (anonymized version) (1.0.0). [Data set]. Zenodo. 2025. http://www.doi.org/10.5281/zenodo.15074016
- Wendt R, Naderer B, Bachl M, et al.:
Social media literacy among adolescents and young adults: results from a cross-country validation study.
Soc Media Soc.
2023; 9(4). Publisher Full Text
- World Medical Association: WMA declaration of helskini – ethical principles for medical research involving human parcitipants.
2024. Reference Source
- Ye L, Yang H:
From digital divide to social inclusion: a tale of mobile platform empowerment in rural areas.
Sustainability.
2020; 12(6): 2424. Publisher Full Text









