Introduction
Access to secondary use of medical imaging data for AI-driven research are hindered by fragmentation, lack of interoperability, and complex regulations across Europe regarding privacy and security issues. Although many research initiatives have created imaging repositories, these are often project-specific, temporally limited, and constrained in their potential for reuse. This is especially challenging in oncology1–3, where AI tools for precise diagnosis, prognosis and treatment estimations require large, standardized and annotated datasets to reach full clinical applicability4,5.
The European Federation for Cancer Images (EUCAIM) project addresses these challenges by developing a large-scale, secure, and federated digital infrastructure for medical imaging and related clinical data. EUCAIM accelerates AI research in personalized medicine, offering tools that support clinical decision-making in complex settings6. EUCAIM builds on the AI for Health Imaging (AI4HI) network, which includes five major Horizon Europe projects (PRIMAGE, CHAIMELEON, EuCanImage, ProCancer-I, and INCISIVE). With over 90 partners and more than 180 stakeholders, EUCAIM is creating a GDPR-compliant, sustainable ecosystem for AI-based cancer research7,8.
While EUCAIM offers a unique opportunity to harmonize and share annotated oncological imaging data, its success depends on overcoming technical barriers (standardization, transformation, anonymization, curation), strict compliance with the General Data Protection Regulation (GDPR), the European Health Data Space Regulation (EHDSR), and the Artificial Intelligence Act (AI Act), and with a clear governance frameworks9. The EUCAIM platform aims to host over 60 million images from more than 100,000 patients, transforming medical data use in personalized actionable care10.
EUCAIM’s hybrid model allows Data Providers to transfer data to a reference node or set up their own federated node. This paper analyses the use case of real-world data transfer from a referral hospital, detailing workflows and practical solutions to secure legal compliant integration into EU-wide repositories.
Material and methods
Data integration in EUCAIM follows either a Data Sharing Agreement (DSA), where data stays within the institution via a federated node; or a Data Transfer Agreement (DTA), where data is physically moved to a reference node. For the retrospective imaging data included in this study, no informed consent was required, an exemption of informed consent was submitted to and approved by the Ethics Committee. All these nodes are core to EUCAIM’s infrastructure.
Data extraction and exposure pipeline
To ensure standardized, anonymized, and compliant data integration into the EUCAIM infrastructure, a structured extraction, transformation, and loading (ETL) pipeline was defined, incorporating best practices in data governance, security, and regulatory adherence. Imaging data were extracted from the hospital PACS through specific nodes in DICOM format according to each project’s inclusion criteria. Corresponding clinical data were retrieved from the Electronic Health Record (EHR) system to maintain proper alignment. Pseudonymization and compliance checks were carried out on a restricted-access virtual machine by dedicated personnel, ensuring a clear separation from researchers and full GDPR compliance. This process follows guidelines from the DICOM Standards Committee and the AI4HI initiative to guarantee interoperability with EUCAIM.
Key pseudonymization steps included replacing the PatientID with the project code (for both imaging and clinical data) and applying the Blake2b hashing function to replace the AccessionNumber and StudyID metadata. Folder structures were adjusted to remove any Personally Identifiable Information (PII), and all public/private DICOM metadata potentially containing personally identifiable information were removed, following EUCAIM’s anonymization profile. Secondary captures and screenshots, which may embed sensitive information, were excluded when identified by terms like “DERIVED,” “SECONDARY,” or “SCREEN SAVE” in the ImageType metadata.
Pseudonymized data was then transferred to a separate file system, the Pseudonymized Medical Imaging Repository (RIMP). The DICOM File Integrity Checker developed by our group was used to detect corrupted or missing files. Data were finally ingested into EUCAIM datasets through the QP-Insights API, ensuring stronger anonymization, and secure transfer or sharing. This two-layer anonymization approach mitigates re-identification risks, aligning with procedures recommended by the Spanish Data Protection Agency and best practices from the Singaporean authority (Figure 1). For data standardization, all DICOM files and metadata were validated for compliance with EUCAIM’s structure and interoperability standards.
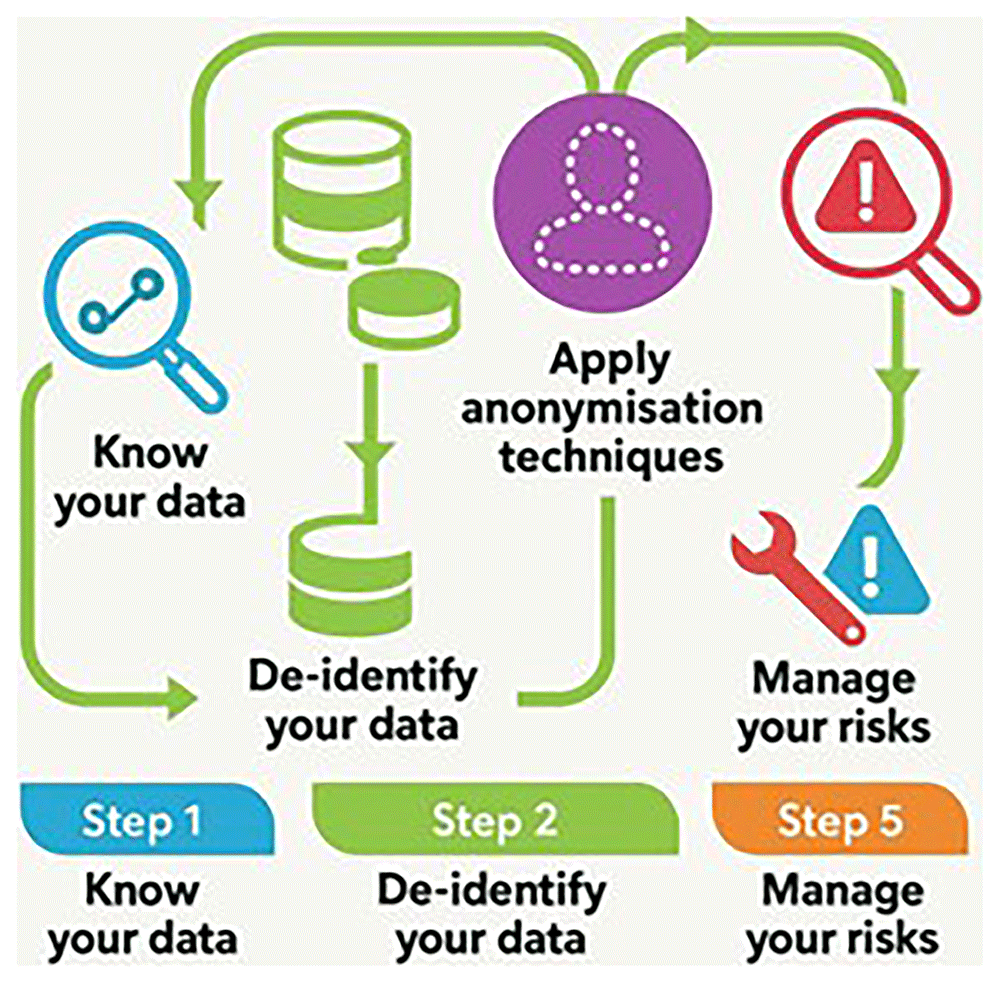
Figure 1. Steps for anonymization.
Source: Adapted from AEPD. Guide to basic anonymization. Prepared by the National Data Protection Authority of Singapore (PDPC - Personal Data Protection Commission Singapore.
The EUCAIM Federated Node provides an open-source, fully integrated Data Lake, Registry, and Secure Virtual Research Environment, backed by dedicated computing resources. Its API enables the ingestion while logging all transfers for traceability and auditability. Federated nodes are fully integrated within the EUCAIM platform and meet the EHDSR requirements for Secure Processing Environments (SPEs). SPEs ensure that data processing stays local, under the health data holder’s continuous control, significantly reducing transfer risks. Specialized mediation software enforces strict anonymization rules, restricts user actions, and logs all activities to prevent misuse and ensure full accountability.
By leveraging SPEs and federated nodes, EUCAIM provides a robust, compliant, and auditable framework for the secure secondary use of health data. This rigorous ETL pipeline ensures scalability, data quality, and legal compliance, positioning EUCAIM’s reference and federated nodes as the backbone for integrating data from research projects, clinical trials11, and future initiatives, in line with European regulations such as the Data Act and Data Governance Act. This strategy guarantees EUCAIM’s long-term sustainability and impact on AI research in medicine12.
Documentation framework for data integration to EUCAIM
Ensuring compliant data integration within EUCAIM requires strict adherence to clear documentation protocols. At its current stage, decisions on the final integration of a dataset and/or federated node are verified by an Access Committee (AC). During this phase, it is mandatory to provide documentary evidence that guarantees accountability in EUCAIM’s operation and demonstrates the application reliability.
For data transfers to EUCAIM, the following documents are considered to safeguard data integrity and regulatory compliance previous to the signature of the DTA:
Data Protection Officer (DPO) Report or Self-Declaration: formal declaration by the transferring institution affirming that the data processing activities comply with GDPR requirements, including data minimization, data protection by design, and risk mitigation measures.
Codes of conduct or certification schemes adherence: a non-mandatory certification of GDPR declaring the institution provides evidence of adherence to established codes of conduct or certifications relevant to GDPR compliance.
Data Protection Impact Assessment (DPIA). documented evidence of the completed DPIA must be submitted in cases where, in accordance with Article 25 of the GDPR and the relevant national authority's whitelist, it is required.
Ethical Approval Documentation from the relevant Ethics Committee: certifying that the data transfer aligns with ethical research practices and data protection regulations. The requirement for ethics approval, its specific content, or any granted exemption is determined by national law. In cases where ethics approval is not required, it is recommended to be explicitly documented in the statement provided by the DPO.
Legal Representation Declaration: signed by the institution’s legal representative, confirming that the data transfer adheres to legal obligations and that the representative is duly authorized to sign agreements on behalf of the institution. This documentary requirement is crucial, as requests might be handled by researchers or individuals who lack the legal capacity to make binding declarations of intent.
For Data Sharing Agreements (DSAs) via federated nodes, the same requirements apply, with an additional Security Report or certification (e.g., ISO 27001) document verifying that data sharing meets EUCAIM’s security standards for encryption, user authentication, and access control.
All documentation must be verifiable and may undergo audits. Federated nodes must show secure operations and technical interoperability with the EUCAIM platform. Likewise, datasets claimed to be anonymized will be checked: any re-identification risk means the data will be returned for further processing until fully compliant. This framework guarantees that all partners contribute data responsibly, supporting secure, transparent, and efficient data sharing within the EHDSR.
Use case of data transfer from completed research projects
The PRIMAGE project (GA: 826494) demonstrated how historical datasets could be successfully transferred and validated within the EUCAIM reference node. The main steps included:
Legal and Ethical Compliance: all approvals and documentation were secured.
Data Processing & Transfer: imaging data were extracted, anonymized, and reformatted into EUCAIM-compliant DICOM structures. Clinical data was similarly processed, aligned with the EUCAIM CDM and hyper-ontology based on mCODE specifications.
Use case of data transfer from oncology clinical trials
The previous approach was also applied to ongoing clinical trials, expanding EUCAIM’s reference node cases. Additional challenges emerged, particularly regarding data ownership and sponsor agreements. Key strategies included:
Data Ownership Clarification: a legal framework defined that imaging data belong to the patient’s EHR, not the trial sponsor, minimizing transfer conflicts and ensuring EU compliance.
Informed Consent: exemptions were requested as data were fully anonymized and restricted to research use.
Periodic Scheduling: semi-annual transfers allow continuous integration in line with regulatory approvals.
Use case of data sharing from ongoing research projects
The CHAIMELEON project (GA: 952172) illustrated a continuous dataset sharing process without disrupting ongoing research, serving as a model for federated nodes. For these projects, a more dynamic workflow was required due to evolving data collection and regulatory requirements:
Ethics Committee Approval: an addendum updated the original approval to permit secondary data use in EUCAIM.
Data Harmonization & Monitoring: a real-time tracking system ensured seamless, compliant integration.
CHAIMELEON reached a high maturity level by preparing a robust DSA, anonymizing data, implementing a secure node, and completing a DPIA, setting a strong precedent for future compliant transfers.
Ethical and legal considerations
Each use case prioritizes full compliance with data protection regulations, especially GDPR. All data transferring and sharing activities were approved by the relevant ethics committees, ensuring confidentiality, integrity, and security. This rigorous approach has enabled the secure transfer and sharing of large volumes of anonymized data, contributing to advanced AI research. Within EUCAIM, data use is strictly limited to users with approved research projects that meet institutional ethics standards and follow the Access Committee’s protocols.
The recent approval of the EHDSR marks a significant milestone for EUCAIM and similar initiatives, providing a harmonized framework for secure access, sharing, and secondary use of large-scale medical datasets. This framework sets clear rules for research and innovation, supported by strict requirements for security, privacy, and informed consent, fostering an interoperable and sustainable data ecosystem. EUCAIM’s activities have been progressively aligned with this evolving landscape, positioning as a pilot platform under HealthData@EU. Its formal integration into the EHDS ecosystem will strengthen data accessibility and protection, reinforcing the project’s long-term sustainability and scientific value, as data volume and diversity grow.
Results
The implementation of a dedicated, harmonized pipeline for data transfer and sharing enabled the successful ingestion of cancer imaging data into the EUCAIM infrastructure. This process established a replicable and scalable workflow suitable for future large-scale federated data integration.
In total, 12,484 medical imaging studies at our hospital and research institute were identified, reviewed, and prepared for integration into EUCAIM, covering both research datasets and real-world clinical trial data. Of these, 10,892 studies (87.24%) from 6,105 patients have been fully processed and validated for upload through either a reference or federated node approach. Our institution has contributed to several initiatives, including the completed PRIMAGE project with 878 studies, the ongoing CHAIMELEON project with 5,346 studies, and a series of Oncology Clinical Trials comprising 4,668 studies. The datasets include multiple modalities (CT, MR, mammography, PET-CT) and represent a broad spectrum of cancer cases and patient populations (Table 1).
Table 1. Overview of prepared Data Sources for Integration into the EUCAIM Reference Node and Federated Node.
| Acronym | Project status | Number of identified
imaging studies | Number of prepared
imaging studies | Node |
|---|
| PRIMAGE | Completed | 878 | 878 | Reference |
| CHAIMELEON | Ongoing | 5,346 | 5,346 | Federated |
| Clinical Trials | Completed and
ongoing | 6,260 | 4,668 | Reference |
The ETL pipeline achieved a processing efficiency of 98.6%, with minimal data loss. Automated DICOM anonymization, combined with manual checks, ensured GDPR compliance while maintaining clinical relevance. PRIMAGE delivered one of EUCAIM’s largest structured paediatric oncology datasets, setting a benchmark for rare disease integration. CHAIMELEON validated a stepwise model for harmonized data sharing, and the inclusion of ongoing clinical trial data demonstrated the feasibility of incorporating prospective datasets into the federated infrastructure.
Several challenges emerged that required refinements to optimize efficiency, scalability, and compliance. A key technical challenge was achieving interoperability across diverse imaging formats and legacy PACS metadata, which often required extensive transformation and custom mapping. Variability in clinical data mappings also highlighted the need for more automated and standardized processes.
Administrative and legal aspects added complexity. Ethics approvals often needed significant revisions depending on the project type, and requests for informed consent exemptions required careful justification and additional documentation. These barriers underscored the lesson learned: the EHDS will require organisations to renew their ethical and legal governance models to ensure predictable, efficient data sharing, including data holders, research infrastructures, and users.
Scalability was initially hindered by reliance on manual anonymization checks, slowing processing and introducing inconsistencies. Introducing automated validation tools and batch workflows significantly improved efficiency, though manual review remains necessary for nuanced cases like secondary capture images.
These insights guided refinements to our protocols. Automated metadata validation minimized errors, while standardized ethics templates helped accelerate approval timelines. Experience gained across projects emphasized the importance of early alignment with EUCAIM requirements, ensuring technical, compliance, and governance aspects are clear from the outset.
Despite initial hurdles, this process strengthened our capacity to securely transfer oncological imaging data with the highest standards of security, privacy, and interoperability, providing a solid foundation for future data-sharing efforts within EUCAIM and similar large-scale initiatives.
Discussion
EUCAIM is established as a landmark initiative in oncological imaging, offering Europe’s first large-scale hybrid infrastructure for the secondary use of imaging, clinical, and molecular data. By integrating datasets from completed research, ongoing projects, and clinical trials, EUCAIM ensures alignment with the EHDSR and GDPR, thereby supporting the full potential of artificial intelligence in advancing predictive and personalized cancer care. Nevertheless, significant challenges remain, particularly data fragmentation, legacy system integration, and cross-border regulatory complexity.
A key barrier to building a unified repository has been the variability in data formats, metadata, and institutional governance practices. EUCAIM addresses this challenge through structured documentation frameworks and standardized ETL pipelines, which enhance data governance and promote interoperability across systems. Even so, harmonizing legacy PACS data and oncological metadata will continue to demand refinements and shared best practices.
From the outset, ethical and legal considerations have been central. Multi-step anonymization, robust audit logs, and clear governance models ensure compliance and traceability. However, achieving consistent ethics approvals and seamless cross-border data sharing still requires effort. The EHDS framework will be instrumental in easing these processes, but only if health data holders, research infrastructures, and users renew and align their governance models.
The lessons learned from large-scale data integration reinforce the value of early legal and technical alignment. PRIMAGE, CHAIMELEON and ongoing clinical trials each illustrate how proactive regulatory planning and clear data management frameworks enable scalable, compliant data sharing.
Long-term sustainability will rest on strict adherence to FAIR principles, supported by reference and federated nodes, FAIR Data APIs, and persistent identifiers that guarantee data findability and reusability. Automating compliance checks and deploying secure cloud-based environments will be essential to handle ever-growing data volumes, while standardized metadata schemas will further support seamless reuse.
Through the continuously refinement of its governance strategies and proactive alignment with the evolving regulatory landscape under the EHDS, EUCAIM is positioned to become a cornerstone for AI-driven oncology research. Its robust infrastructure not only accelerates the clinical translation of AI tools but also strengthens a culture of trustworthy, collaborative data sharing across Europe, reinforcing EUCAIM’s pivotal role in shaping the future of cancer imaging and precision medicine. Central to this effort is the essential contribution of data providers, whose engagement ensures the availability, diversity, and quality of datasets reinforcing EUCAIM in shaping the future of precision medicine.
Ethical approval statement
This manuscript has been approved by the Research Ethics Committee on Medicinal Products of La Fe University and Polytechnic Hospital under registration number 2022-437-1. For the retrospective imaging data included in this study, no informed consent was required, an exemption of informed consent was submitted to and approved by the Ethics Committee.
Data availability
No data are associated to this manuscript.
Acknowledgments section
Patricia Serrano Candelas, Silvia Flor Arnal, Lucas Espuig Peiró, Antonio Orduña Galán, Cayetano Hernandez Marín and Javier Medina Álvarez.
Faculty Opinions recommendedReferences
- 1.
Genovese S, Bengoa R, Bowis J, et al.:
The European Health Data Space: a step towards digital and integrated care systems.
J Integr Care.
2022; 30(4): 363–372. Publisher Full Text
- 2.
Lehne M, Sass J, Essenwanger A, et al.:
Why digital medicine depends on Interoperability.
NPJ Digit Med.
2019; 2(1): 79. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 3.
Pierce HH, Dev A, Statham E, et al.:
Credit data generators for data reuse.
Nature.
2019; 570(7759): 30–32. PubMed Abstract
| Publisher Full Text
- 4.
Norgeot B, Glicksberg BS, Butte AJ:
A call for deep-learning healthcare.
Nat Med.
2019; 25(1): 14–15. PubMed Abstract
| Publisher Full Text
- 5.
Koh DM, Papanikolaou N, Bick U, et al.:
Artificial intelligence and machine learning in cancer imaging.
Commun Med (Lond).
2022; 2(1): 133. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 6.
Radclyffe C, Ribeiro M, Wortham RH:
The assessment list for trustworthy Artificial Intelligence: a review and recommendations.
Front Artif Intell.
2023; 6: 1020592. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 7.
Gagliardi D, et al.:
AI4HI: AI and health imaging research priorities.
European Journal of Radiology Open.
2023.
- 8.
Kondylakis H, Ciarrocchi E, Cerda-Alberich L, et al.:
Position of the AI for Health Imaging (AI4HI) network on metadata models for imaging biobanks.
Eur Radiol Exp.
2022; 6(1): 29. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 9.
Voigt P, Von der Bussche A:
The eu General Data Protection Regulation (GDPR). A Practical Guide, 1st Ed., Cham: Springer International Publishing, 2017; 10(3152676): 10–5555.
- 10.
Wilkinson MD, Dumontier M, Aalbersberg IJ, et al.:
The FAIR guiding principles for scientific data management and stewardship.
Sci Data.
2016; 3(1): 160018. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 11.
Gyrard A, Abedian S, Gribbon P, et al.:
Lessons learned from European health data projects with cancer use cases: implementation of health standards and internet of things semantic interoperability.
J Med Internet Res.
2025; 27: e66273. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 12.
Martí-Bonmatí L, Blanquer I, Tsiknakis M, et al.:
Empowering cancer research in Europe: the EUCAIM cancer imaging infrastructure.
Insights Imaging.
2025; 16(1): 47. PubMed Abstract
| Publisher Full Text
| Free Full Text







