1. Introduction
Hospital schools provide educational services to children and adolescents whose treatment interrupts regular schooling, helping to preserve learning, peer connection and a sense of normality during hospitalization (Issaka and Hopkins, 2015; Jiliberto and Zarate Alva, 2024). Whilst form and resourcing of these services vary across health and education systems, physical education (PE) is frequently omitted because of limited space, equipment, specialist staff and time, together with concerns about medical safety and coordination with clinical care (Catenazzo, 2019; Catenazzo, 2024; Cistulli et al., 2025).
PE is a curriculum area with explicit learning aims related to movement competence, knowledge and understanding, meaningful participation, and personal and social development (McLennan and Thompson, 2015; Opstoel et al., 2020; GloPL Consortium, 2026). It is therefore conceptually distinct from physical activity as a broad behaviour of bodily movement resulting in energy expenditure (World Health Organization, 2022; Ciaccioni et al., 2026a), from therapeutic exercise or rehabilitation prescribed primarily to address symptoms, impairments, functioning, or other health-related needs (Taylor et al., 2007; Gutenbrunner et al., 2011) and from recreational or play-based movement that may occur without explicit curricular learning objectives (Pellegrini and Smith, 1998; Martins et al., 2021). Although these activities may overlap in hospital settings, they differ in their primary purposes, intended learning or clinical outcomes, and the professional responsibilities associated with their planning and delivery. Consequently, evidence from clinical exercise programs can inform, but cannot automatically be interpreted as evidence for PE provision within hospital schools.
Research on hospital-based movement is dispersed across education, paediatric rehabilitation, psychology, nursing and sport sciences. Existing reviews have generally examined physical activity or therapeutic exercise in specific clinical groups rather than PE as an educational provision (Dixon, 2020; Ludgério et al., 2023; Theobald et al., 2025). In parallel, international commitments support inclusive education and participation for hospitalised children, but the extent to which laws, curriculum frameworks and implementation guidance address PE in hospital schools has not been systematically mapped (McLennan and Thompson, 2015; UNESCO, 2015; European Parliament, 2016; European Commission, 2025). Consequently, the evidence base and the policy environment remain difficult to interpret together.
In response to these gaps, a multi-component review has been designed to consolidate evidence and policy information on PE in hospital schools. The objectives are to: (i) identify and describe the characteristics, and delivery models of PE interventions in hospital-school settings; (ii) summarise evidence concerning their safety, feasibility and physical, psychosocial, and educational outcomes; (iii) synthesize systematic-review evidence on broader hospital-based physical activity interventions that may offer transferable insights; (iv) map international, national and regional policy and regulatory provisions relevant to PE in hospital schools, including professional preparation and intersectoral responsibilities; (v) integrate empirical and policy findings to identify areas of convergence, divergence and uncertainty.
Thus, developed within the framework of the MSCA Global Postdoctoral Fellowship project “Hospital schools’ guidelines On Physical Education” (HOPE; https://cordis.europa.eu/project/id/101206417), this protocol is intended to provide an evidence-informed foundation for later guideline development.
2 Methods and analysis
2.1 Review structure
The present protocol was prospectively registered in the International Prospective Register of Systematic Reviews (PROSPERO) on 04 December 2025 (registration number: CRD420251156215). The preparation and reporting of this protocol manuscript were conducted in accordance with the Preferred Reporting Items for Systematic Review and Meta-Analysis Protocols (PRISMA-P; see Extended Data: (Ciaccioni et al., 2026b)) guidelines (Shamseer et al., 2015). The plan comprises two evidence-synthesis tiers and a parallel policy framework analysis. The components will be conducted separately using purpose-specific eligibility criteria, searches, appraisal methods and syntheses, and will be integrated only at the interpretation stage (Tenenbaum and Driscoll, 2005; Bowen, 2009; Browne et al., 2019).
• Tier 1: Umbrella review of systematic reviews. This component will include systematic reviews with or without meta-analyses, that use explicit eligibility criteria and reproducible search methods to examine physical activity, exercise, and movement-based interventions delivered to hospitalised children and adolescents. Its purpose is to summarise higher-level evidence on benefits, harms, and implementation considerations that may be relevant, but not necessarily directly transferable, to hospital-school PE.
• Tier 2: Systematic review of primary studies. This component will include quantitative, qualitative, and mixed-methods primary studies of PE in formal hospital school or hospital-associated educational programs. Because the field is expected to be small, eligible designs will include randomised and non-randomised studies, observational studies, qualitative studies, mixed-methods studies, and case reports or series that provide sufficient information on a structured PE intervention or its implementation. Descriptive and case-based evidence will be used for mapping and narrative interpretation rather than pooling estimates of effectiveness.
• Policy framework analysis. A structured document analysis will identify binding and non-binding instruments relevant to PE or movement provision in hospital education. Eligible sources will include legislation, regulations, ministerial decrees or circulars, curriculum frameworks, national or regional strategies, official standards, implementation guidance and international normative or recommendation documents. Expert consultation will be used only to identify potentially missing documents; expert opinions will not be analysed as data.
Figure 1 presents the concurrent design. Tier 1 provides the broader hospital-based physical activity context, Tier 2 focuses specifically on PE as educational provision in hospital-school settings, and the policy analysis examines the governance context. Findings will be compared through a predefined integration framework addressing convergence, divergence, transferability and gaps, without combining unlike forms of evidence into a single effect estimate.
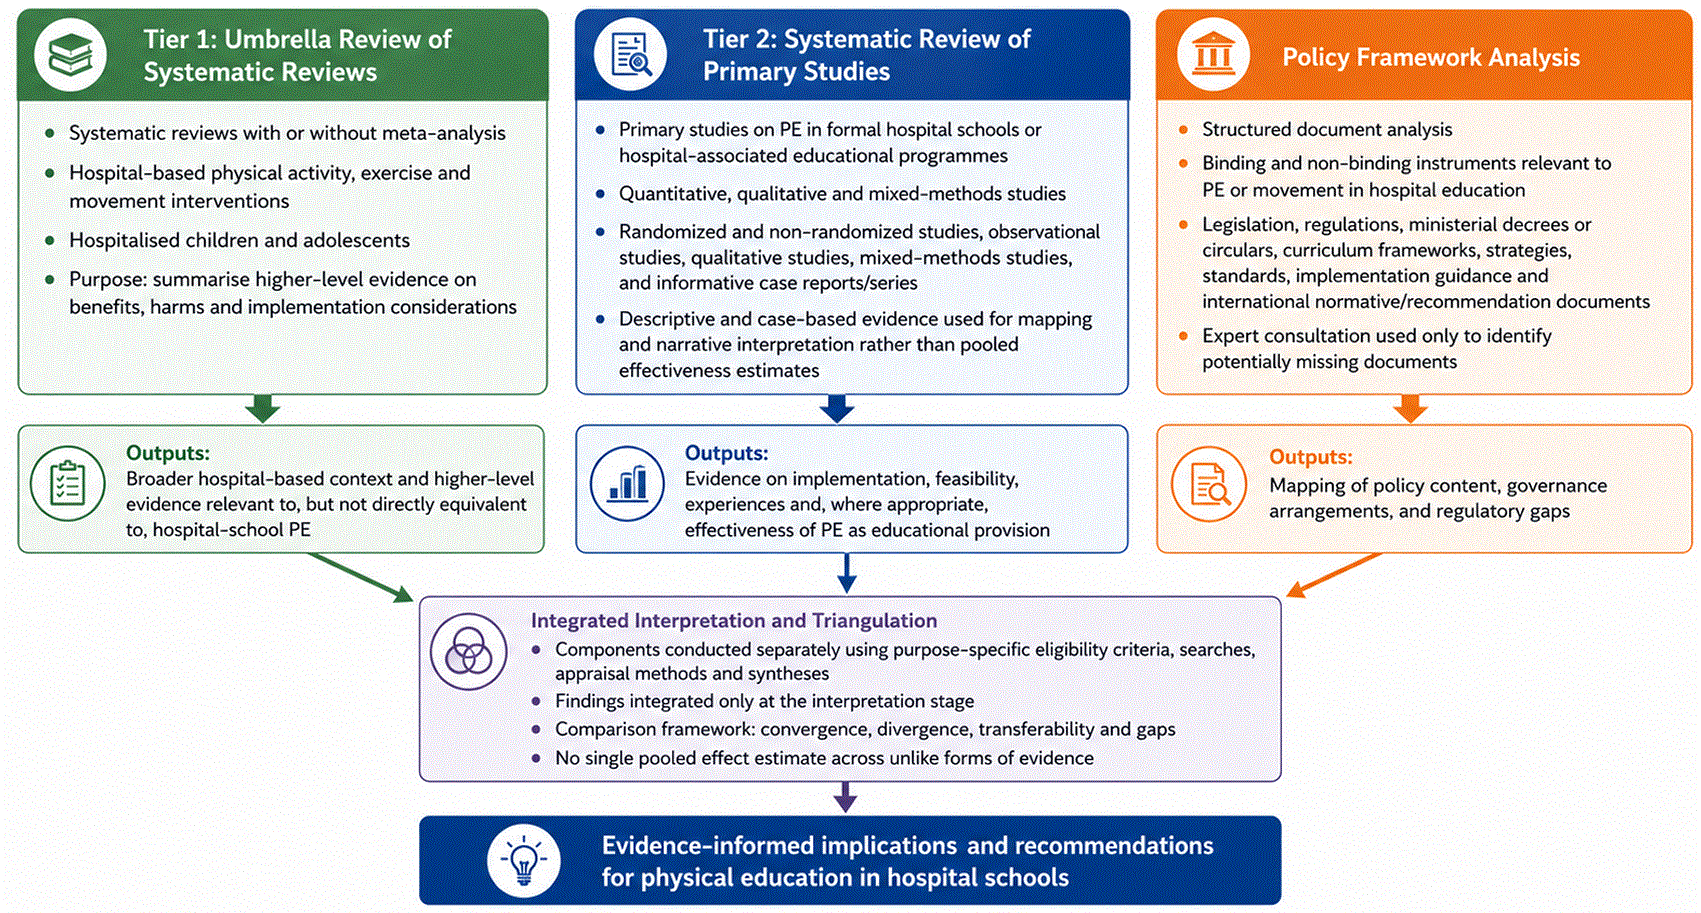
Figure 1. Overview of the concurrent multi-tier design and evidence integration.
Note: PE: Physical education; PROSPERO: International Prospective Register of Systematic Reviews; PRISMA-P: Preferred Reporting Items for Systematic Review and Meta-Analysis Protocols.
2.2 Eligibility criteria
Eligibility criteria were developed using the Population, Intervention, Comparator, Outcomes and Study design (PICOS) framework, with an additional Context criterion (Brown et al., 2006). The terminology and Tier 2 screening decision rule are presented in Table 1. The definitions are intended to prevent educational PE from being conflated with clinical treatment or unstructured recreation while allowing transparent assessment of interventions that combine educational and therapeutic elements.
Table 1. Operational terminology and Tier 2 screening decision rule.
|
Term | Operational meaning in this protocol | Tier 2 eligibility |
|---|
| Physical education | Planned movement-based learning with explicit educational aims related to curriculum, movement competence, knowledge, participation, self-regulation, or personal and social development. | Eligible when the educational purpose is explicit and the activity is either formally integrated into the hospital-school program or involves educational staff in planning, delivery or assessment. |
| Physical activity | Any bodily movement that increases energy expenditure, irrespective of purpose or setting. | Eligible only when it also meets the PE educational decision rule. Otherwise, it may be relevant to Tier 1. |
| Exercise or therapeutic exercise | Planned and structured activity undertaken primarily to improve fitness, symptoms, function or health. | Eligible only when it has an explicit educational purpose and a documented hospital-school connection. Clinically prescribed exercise alone is excluded. |
| Rehabilitation or physiotherapy | Clinical assessment and treatment intended to restore or maintain function. | Excluded when delivered solely as healthcare. Included only when formally integrated with educational aims and the hospital-school program. |
| Active play or recreation | Enjoyable spontaneous or structured movement primarily intended for play, leisure or social interaction. | Eligible only when educational objectives and hospital-school integration are documented. |
| Borderline cases | Activities combining educational, therapeutic and recreational purposes. | Criterion A, explicit educational purpose, is mandatory. In addition, criterion B, formal hospital-school integration, or criterion C, documented educational-staff involvement, must be present. Unclear cases will undergo duplicate full-text assessment and author contact where feasible. |
Population and context: Tier 2 will include children and adolescents of compulsory or upper-secondary school age, approximately 5 to 18 years, who receive education during inpatient care or through a hospital-associated educational program. All diagnoses, treatment pathways and countries will be eligible. Home or outpatient education will be excluded unless it forms part of a documented hospital-school transition or reintegration program. Tier 1 will include systematic reviews of hospitalised children and adolescents, whether or not the intervention is connected to schooling.
Interventions: A Tier 2 intervention must have an explicit educational purpose, such as curriculum-related learning, development of movement competence, knowledge, participation, self-regulation or personal and social learning through movement. In addition, it must either be formally scheduled or documented within the hospital-school program, or involve a teacher, PE professional or other educational staff member in planning, delivery or assessment. Frequency, intensity, duration, group size and mode of delivery will not determine eligibility.
Therapeutic exercise, physiotherapy, rehabilitation and active play will be included in Tier 2 only when they meet the educational decision rule in Table 1. Programs delivered solely as medical treatment, symptom management or recreation without an explicit educational objective will be excluded from Tier 2 but may be represented in Tier 1 through an eligible systematic review. Borderline cases will be independently assessed by two reviewers using the decision rule; study authors will be contacted when the educational purpose or organisational linkage cannot be determined from the report.
Comparator: A comparator will not be required because qualitative studies, single-group evaluations and descriptive designs are expected. When available, comparators such as usual care, non-PE educational activities, alternative movement programs or pre-intervention measurements will be extracted and considered in design-specific syntheses.
Outcomes: Priority outcomes will be organised into two complementary synthesis strands. The implementation/process strand will prioritise (i) safety and feasibility/implementation, including adverse events, and (ii) educational participation or engagement; these findings will be synthesised using quantitative descriptive, qualitative and mixed-method evidence, as appropriate. The effectiveness/outcome strand will prioritise (iii) physical functioning or motor competence and (iv) psychosocial well-being or health-related quality of life; these domains will be prioritised for comparative quantitative synthesis and GRADE assessment when the prespecified criteria for quantitative synthesis are met. Comparative evidence concerning safety or educational participation may also undergo quantitative synthesis and GRADE assessment when a sufficiently coherent body of evidence is available. Other clinical, cognitive, academic and implementation outcomes will be mapped and synthesised narratively.
Study Designs: Tier 1 will include systematic reviews and meta-analyses with an explicit search strategy, eligibility criteria and reproducible selection process. Narrative, scoping or integrative reviews will be excluded unless they meet these minimum systematic-review criteria. Tier 2 will include randomised trials, quasi-experimental and other non-randomised intervention studies, cohort, case-control and cross-sectional studies, qualitative studies, mixed-methods studies, and informative case reports or series. Protocols, editorials, commentaries and conference abstracts without sufficient outcome or implementation data will be excluded.
No restrictions will be applied by country, language, publication year, medical condition or length of stay. Contextual information, including the type and governance of the hospital school, educational staffing, clinical collaboration, resources and transition arrangements, will be extracted because these features may influence feasibility and transferability (Pesce et al., 2021; Ciaccioni et al., 2025).
2.3 Data sources and search strategy
Separate search strategies will be developed for the umbrella review, the primary-study systematic review and the policy framework analysis because the components address different questions and evidence sources. Table 2 summarises the operational structure; complete line-by-line strategies for each database and operational procedures for policy framework analysis are reported as extended data (Ciaccioni et al., 2026a).
Table 2. Component-specific search framework.
|
Component | Operational search structure |
|---|
| Tier 1: umbrella review | Sources: MEDLINE, Embase, CINAHL, PsycINFO, Scopus, Web of Science, SPORTDiscus and the Cochrane Database of Systematic Reviews. Concepts: child or adolescent AND hospital or inpatient AND physical activity, exercise, sport, movement or rehabilitation AND systematic-review terms. Hospital-school terminology will not be mandatory. |
| Tier 2: primary-study review | Sources: MEDLINE, Embase, CINAHL, PsycINFO, Scopus, Web of Science, SPORTDiscus, ERIC, Education Source and CENTRAL. Concepts: hospital school or in-hospital education AND physical education, physical activity, exercise, movement, sport or active play AND child or adolescent. No study-design filter will be applied. |
| Policy framework analysis | Sources: official international, European, national and regional organisation websites; ministries of education and health; legal databases; curriculum authorities; Youth Wiki; and recognised hospital-school networks. Concepts will combine hospital schooling or education during illness with PE, physical activity, movement, sport, curriculum, law, regulation, strategy, guideline and implementation terms in English and relevant local languages. |
• Tier 1 strategy. Searches will not include hospital-school terms as a mandatory concept because the purpose is to capture the broader hospital-based evidence. Reviews will be screened against the methodological and population criteria stated above, and the reference lists and citing literature of included reviews will be examined.
• Tier 2 strategy. Search sensitivity will be prioritised because hospital-school PE may be described using educational, clinical or recreational terminology. Broad movement terms will therefore be retained at the search stage, while the educational decision rule in Table 1 will be applied during full-text screening.
• Policy strategy and documentation. A common country-search template will specify the official domains searched, English and local-language terms, document categories, dates searched, result counts and reasons for exclusion. Search strings will combine hospital schooling or education during illness with PE, physical activity, movement, sport, curriculum and implementation terms. Where website search functions are inadequate, targeted web searches restricted to official domains will be used. Superseded documents will be retained only when needed to explain policy development and will be clearly labelled as historical.
Supplementary identification methods will include backward and forward citation searching, searches of relevant repositories and doctoral theses, and consultation with hospital educators, researchers and policy stakeholders. All expert contacts will receive the same written request. The search log will record the expert’s role, country, date of contact and nominated documents. A nominated document will be included only after independent eligibility verification and source authentication.
No date or language restrictions will be applied. Titles and abstracts in languages not spoken by the review team will be assessed using professional translation, institutional language support or verified machine translation as appropriate. Key eligibility, extraction and appraisal decisions will be checked by a reviewer able to assess the original language whenever feasible.
Database records will be exported to MS Excel (Microsoft 365), deduplicated and assigned to the relevant component. Searches will be rerun before final synthesis. The final reports will provide the complete strategies, dates, platforms, filters, deduplication procedures and any deviations from this protocol.
2.4 Use of artificial intelligence and automation tools
Any automation or artificial intelligence functionality will be used, if at all, only for supportive tasks such as deduplication, record organisation, translation support or citation prioritisation (Thomas et al., 2026). Automated outputs will not determine eligibility, extraction, appraisal, coding, theme development, certainty ratings or interpretation. Reviewers will verify all outputs and retain direct responsibility for every methodological decision. The tool name, developer, version, purpose, date of use, input type, verification procedure and any detected errors will be documented in the final report.
2.5 Screening and study selection
The reviewer workflow is summarised in Table 3 and will apply separately to Tier 1, Tier 2 and the policy component. Before formal screening, reviewers will pilot the eligibility criteria on a shared sample and refine the guidance without altering the registered review questions. Titles and abstracts, followed by full texts, will be assessed independently by two reviewers. Disagreements will be resolved through discussion and, when necessary, adjudication by a third reviewer. Full-text exclusions and reasons will be recorded, and selection will be reported using component-specific PRISMA flow diagrams. Authors will be contacted when essential eligibility information is unclear.
Table 3. Reviewer workflow across the three review components.
|
Stage | Reviewer process | Resolution and documentation |
|---|
| Search validation | A second reviewer or information-search lead will check each strategy against the relevant eligibility criteria before execution. | Search versions, dates, platforms and amendments will be retained in the search log. |
| Title, abstract and full-text screening | Two reviewers will assess records independently after a shared calibration exercise. | Disagreements will be resolved by consensus or third-reviewer adjudication; full-text exclusion reasons will be recorded. |
| Data extraction | One reviewer will extract data and a second reviewer will verify all fields against the source. | Discrepancies and author contacts will be documented. |
| Risk of bias and critical appraisal | Two reviewers will appraise each included unit independently using the tool appropriate to its design or document type. | Consensus or third-reviewer adjudication; domain-level judgments will be retained. |
| Qualitative synthesis | Two reviewers will independently code a diverse calibration sample; one will code the remaining findings and the second will verify coding and themes. | A codebook, reflexive notes, divergent cases and theme revisions will form an audit trail. |
| Certainty assessment | Two reviewers will independently prepare GRADE or GRADE-CERQual judgments for predefined priority findings. | Consensus or third-reviewer adjudication; reasons for judgments will be reported. |
| Policy-document analysis | Two reviewers will independently confirm eligibility; one will extract and a second will verify. | Expert nominations will be logged and subjected to the same eligibility and authenticity checks as documents found through standard searches. |
2.6 Data extraction
Component-specific extraction forms will be developed, piloted and accompanied by a coding manual (Khudair et al., 2022; Lee et al., 2025a; Lee et al., 2025b). For Tier 2, extracted items will include publication and design, country and hospital-school context, participant characteristics and diagnoses, educational purpose, intervention content and dose, delivery personnel and professional preparation, curriculum linkage, comparator, outcomes and instruments, time points, numerical or qualitative findings, adverse events, implementation processes, barriers and facilitators, funding and conflicts of interest.
For Tier 1, extraction will cover review objectives, databases and search dates, eligibility criteria, included study designs and populations, intervention categories, outcomes, synthesis methods, effect estimates, adverse events, implementation findings, certainty assessments and authors’ conclusions. Primary-study overlap across included reviews will be mapped and quantified using the Corrected Covered Area (Higgins et al., 2023). No new meta-analysis will combine pooled estimates from overlapping reviews.
For policy documents, extraction will record the document title, issuing authority, jurisdiction, legal or administrative status, date, current or superseded status, target population, references to PE or related movement provision, curricular expectations, professional roles, safety and adaptation requirements, funding or resource provisions, implementation and monitoring mechanisms, and links between education and health authorities. Direct quotations will be limited to short excerpts required to support interpretation.
One reviewer will extract each record and a second reviewer will verify all fields against the source. Discrepancies will be resolved according to Table 3. When multiple reports describe the same study or policy instrument, they will be linked and treated as one unit of evidence. Authors or issuing bodies may be contacted for missing information, but unverified information will not replace the published or official record.
2.7 Risk of bias and quality assessment
Critical appraisal will be selected according to evidence type and will be completed independently by two reviewers as specified in Table 3. Appraisal results will inform synthesis, certainty assessment and interpretation but will not be used as an automatic exclusion threshold.
Randomised trials will be assessed with Cochrane Risk of Bias 2 (RoB 2), and non-randomised intervention studies with Risk Of Bias In Non-randomized Studies of Interventions (ROBINS-I) (Sterne et al., 2016; Sterne et al., 2019). Observational and case-based quantitative evidence will be assessed using the Joanna Briggs Institute (JBI) critical appraisal instrument appropriate to the reported design (https://jbi.global/critical-appraisal-tools). Mixed-methods studies will be appraised through the Mixed Methods Appraisal Tool-MMAT (Hong et al., 2018).
Qualitative studies will be appraised with the Critical Appraisal Skills Programme checklist, with attention to the appropriateness of the design, recruitment, data collection, reflexivity, analysis, ethical considerations and coherence between data and interpretation (Long et al., 2020).
Systematic reviews included in Tier 1 will be appraised using AMSTAR 2 (Shea et al., 2017). The review team will also examine the recency and scope of each review, the risk of bias of its included studies, and overlap between reviews. Conclusions from critically low-quality reviews will not be treated as equivalent to conclusions from reviews with stronger methods.
Policy and regulatory documents will be appraised according to document type. AGREE II will be used only for documents that meet the characteristics of a practice or implementation guideline (Brouwers et al., 2010). Policy texts will be assessed using the JBI approach for textual policy evidence, including credibility, authority, purpose, evidence base and transparency of development (McArthur et al., 2025). Grey-literature source characteristics will additionally be documented using the Authority, Accuracy, Coverage, Objectivity, Date, Significance (AACODS) Checklist (Seniutis et al., 2026; Tyndall, 2010). For laws and regulations, their issuing authority, legal force, currency, scope, accessibility and implementation provisions will be recorded.
Appraisal judgments will be presented by domain; sensitivity analyses or structured comparisons will examine whether conclusions differ when evidence at high or critical risk of bias is omitted, provided sufficient studies are available.
2.8 Data synthesis and analysis
Narrative synthesis will be the primary approach for both review tiers because heterogeneity is expected in settings, populations, educational purposes, interventions, designs and outcomes. Tier 1 findings will be summarised by review scope and quality, with explicit attention to primary-study overlap and transferability to hospital-school PE. For Tier 2, synthesis will distinguish implementation/process evidence from effectiveness/outcome evidence. Safety, feasibility, implementation and educational participation or engagement will primarily be integrated through narrative, qualitative and, where appropriate, mixed-method synthesis. Physical functioning or motor competence and psychosocial well-being or health-related quality of life will be prioritised for comparative quantitative synthesis. This distinction is analytical rather than absolute, as sufficiently comparable comparative data on safety or educational participation may also support quantitative synthesis. Policy documents will first be synthesised by jurisdiction, document type, legal status and substantive provision, followed by cross-jurisdictional comparison.
Meta-analysis will be considered only when at least three independent studies are sufficiently comparable in population, intervention purpose and content, design, comparator, outcome construct and assessment time point, and when effect estimates can be derived without double-counting participants. Randomised and non-randomised studies will not be pooled together. Random-effects models will be used, with risk ratios or odds ratios for dichotomous outcomes and mean differences or standardised mean differences for continuous outcomes, each with 95% confidence intervals. Statistical heterogeneity will be examined using I-squared and tau-squared, but pooling decisions will be based primarily on clinical, educational and methodological comparability. Subgroup and sensitivity analyses will be undertaken only when adequately supported and will prioritise age group, clinical condition, intervention type, delivery professional and risk of bias. Publication-bias analyses will be considered only when the number of studies is sufficient for meaningful interpretation (Higgins et al., 2023; Borenstein et al., 2021).
Qualitative findings will be synthesised using the three-stage thematic-synthesis process of line-by-line coding, development of descriptive themes and generation of analytical themes (Thomas and Harden, 2008; Green and Thorogood, 2018). Two reviewers will independently code an initial sample representing different settings and participant perspectives, compare interpretations and agree a provisional codebook. One reviewer will then code the remaining findings and the second will verify coding and theme development. Reflexive notes, coding decisions, divergent cases and changes to the codebook will be retained in an audit trail. Participant quotations and study-author interpretations will be distinguished. Policy and empirical syntheses will subsequently be integrated in a matrix examining convergence, divergence, implementation conditions, transferability and unresolved gaps.
2.9 Certainty of evidence assessment
GRADE will be applied to sufficiently coherent bodies of comparative quantitative evidence, with physical functioning or motor competence and psychosocial well-being or health-related quality of life designated as the primary domains for quantitative certainty assessment. Safety/adverse events and educational participation or engagement will also be assessed using GRADE when they are reported as sufficiently comparable comparative outcomes; otherwise, they will contribute primarily to the implementation/process synthesis. Separate certainty judgments will be made by study design and outcome, considering risk of bias, inconsistency, indirectness, imprecision and publication bias, with upgrading factors applied where appropriate. GRADE-CERQual (Confidence in the Evidence from Reviews of Qualitative research) will be applied to a limited set of priority qualitative findings concerning safety, acceptability, barriers, facilitators, educational participation and engagement, and stakeholder experience, considering methodological limitations, coherence, adequacy and relevance (Lewin et al., 2018; Brozek et al., 2021; Kolovelonis et al., 2024). Certainty will not be assigned to isolated case reports, purely descriptive mappings or legal obligations. Summary-of-findings tables will report the rationale for each judgment and distinguish evidence from Tier 1, Tier 2 and the policy analysis.
3. Discussion
This protocol addresses an under-synthesised area at the intersection of education, health and physical activity. Its central methodological challenge is that PE, clinical exercise, rehabilitation and active play may coexist in hospital settings while serving different purposes (Issaka and Hopkins, 2015; West et al., 2019; Cistulli et al., 2025) with operational definitions and decision rules intended to preserve the educational focus of Tier 2 while allowing Tier 1 to provide a broader clinical and implementation context.
The multi-component design may clarify how PE has been conceptualised and delivered, which outcomes have been assessed, and which implementation conditions have been reported. However, the review will not assume that hospital-based physical activity programs are educationally equivalent to PE or that evidence from one diagnosis, profession or healthcare system is transferable to another (Reid, 2010; Braam et al., 2016; Santos et al., 2020; Crowder et al., 2022). Transferability will be examined explicitly with reference to educational purpose, clinical constraints, staffing and governance.
The policy analysis may help explain whether variation in provision is associated with the presence or absence of curriculum requirements, professional responsibilities, safety guidance, intersectoral coordination or implementation resources. Its interpretation will distinguish legal obligations from recommendations and practice guidelines. The analysis is intended to identify policy patterns and gaps rather than rank countries or infer implementation solely from the existence of a document (European Union, 2008; European Commission, 2023; Amornsriwatanakul et al., 2025).
Several limitations are anticipated. The empirical evidence may be sparse, heterogeneous and at risk of bias, which may preclude quantitative pooling and result in low-certainty conclusions. Terminology may be inconsistent, relevant educational activities may be reported in clinical literature, and policy documents may be difficult to locate, translate or compare across legal systems. Standardised searches, transparent decision rules, duplicate screening, document-type-specific appraisal and an audit trail are intended to reduce, but cannot eliminate, these limitations. Expert consultation may improve document identification, although it may introduce unequal coverage across jurisdictions; expert nominations will therefore remain supplementary to the standardised search and will undergo the same eligibility checks (Browne et al., 2019; Brozek et al., 2021; Higgins et al., 2023).
The completed reviews are intended to provide a transparent account of the available evidence and policy landscape. Depending on the findings and their certainty, they may inform subsequent stakeholder consultation, research priorities and the development of context-sensitive guidance for PE in hospital schools. They will not, by themselves, establish universal implementation standards (Kohl III et al., 2013; Longmuir et al., 2013; American Public Health Association, 2021; World Health Organization, 2010).
Ethics and dissemination
This multi-tiered review (encompassing a systematic review, umbrella review, and policy framework analysis) will rely exclusively on secondary data from published studies and publicly available policy documents. No primary data collection involving human participants will be conducted, and thus no formal ethics approval is required.
The results will be disseminated in peer-reviewed publications, conference presentations, open repositories and targeted materials for hospital-school educators, healthcare professionals and policy stakeholders. Dissemination products will distinguish review findings from subsequent recommendations and will report uncertainty, contextual limitations and evidence gaps.










