List of abbreviations
FGD: focus group discussion
HIC: high-income country
HSR: Health system responsiveness
MIC: middle-income country
mhGAP: Mental Health Gap Action Programme
MHPSS: mental health and psychosocial support
NGO: non-governmental organisation
PHC: primary healthcare
PTSD: post-traumatic stress disorder
RCT: randomised controlled trial
STRENGTHS: Syrian REfuGees MeNTal HealTH Care Systems
UNHCR: United Nations High Commissioner for Refugees
WHO: World Health Organization
Introduction
The United Nations High Commissioner for Refugees (UNHCR) estimated that 108.4 million people worldwide were forcibly displaced end of 2022, including 35.5 million refugees and 5.4 million asylum seekers1. Forcibly displaced populations bear a high burden of anxiety, depression, and post-traumatic stress disorder (PTSD)2–5. Refugees’ experiences of war and violence render them at risk of developing mental disorders, exacerbated by post-displacement stressors like poverty, inadequate accommodation, discrimination, social isolation, insecurity, and uncertainty about, for example, legal status, and potential for family reunification6–8.
Despite having high needs for mental health care, refugee populations have low utilisation of mental health and psychosocial support (MHPSS)9,10. MHPSS is defined as any type of external support that aims to protect or promote psychosocial well-being and/or prevent or treat mental disorders11. It covers a broad range of services from diverse providers, including mental health specialists (e.g. psychiatrists, and psychotherapists) and non-specialists (e.g. community workers, social workers, and lay health workers). Previous research has found low uptake of MHPSS by refugees, who experience difficulties in accessing services because of stigma, unfamiliar language, low levels of trust, limited financial resources, and inadequate knowledge about where to seek support, as well as unavailability of relevant effective services9,12–15. Their experiences point to major weaknesses in health system responsiveness (HSR) to the mental health needs of refugees.
There are several definitions of HSR, although there is a consensus that it involves not just the system’s capacity and ability to respond but also its actual response16. The WHO conceptualisation of HSR is widely used16,17 and concerns the health system’s ability to meet the population’s legitimate expectations regarding non-medical aspects of their interactions with the system18. These aspects include patient experiences with the choice of health providers, quality of amenities, and whether they are treated with dignity and confidentiality18. Responsiveness is a complex construct and overlaps with elements of quality of care, coverage, access to care, equity in access, and patient satisfaction19,20. Individual expectations and experiences of the system shape perceived HSR, and consequently health behaviours and outcomes. Responsiveness is considered important for strengthening health system functioning, providing equitable and accountable services, and protecting the rights of citizens16. A recent mapping found an increasing volume of research on HSR in the last decade, but also significant gaps in knowledge of how it is experienced by vulnerable groups (e.g. refugees)16.
The Syrian REfuGees MeNTal HealTH Care Systems (STRENGTHS) study aims to strengthen mental health systems for Syrian refugees in Europe and the Middle East21 and includes, among others, randomized controlled trials (RCT) of MHPSS interventions developed by the World Health Organization (WHO) and informed by consultations with affected populations. Syrians represent the largest refugee population globally, with 6.5 million hosted in 131 countries1. The majority of Syrian refugees are based in neighbouring countries (i.e. Türkiye, Jordan, and Lebanon), but many have also sought refuge in high-income European countries, particularly Germany1. The scope and protracted nature of the Syrian displacement has put pressure on the MHPSS systems of host countries, which can be expected to challenge responsiveness. The purpose of this paper is to assess HSR to the MHPSS needs of Syrian refugees, comparing countries in Europe and the Middle East to inform recommendations to strengthen MHPSS systems.
Methods
Study design and settings
We employed a rapid appraisal methodology to assess HSR to the MHPSS needs of Syrian refugees in all eight countries participating in the STRENGTHS study: Egypt, Germany, Jordan, Lebanon, the Netherlands, Sweden, Switzerland, and Türkiye. These countries collectively host 91% of the global Syrian refugee population (6.2 out of 6.8 million)22.
Rapid appraisals are a pragmatic and systematic way to collect data across a range of health system domains in a feasible, timely and low-cost manner23,24. They are typically conducted by a small team (of two or more individuals) and triangulate data collected using a variety of methods and adopting different perspectives to identify key themes and areas of concern23,25. Rapid appraisals allow for selecting and combining primary and secondary data according to its relevance to the research objectives and context.
The multi-country rapid appraisal approach is appropriate for the STRENGTHS project, as an improved understanding of responsiveness of current health systems will inform decisions on ways to strengthen systems, for example, by integrating scalable psychological interventions21. Multi-country studies give an insight into commonalities and differences across diverse contexts.
Conceptual framework
Our conceptual framework is set out in Figure 1. Details are published elsewhere26 and can be found in Supplementary File 1 in the Extended data27. In brief, it is based on WHO definitions of a health system, its building blocks, and HSR18,28 and domains identified in reviews on HSR17,19. While the WHO framework posits HSR as a final goal, in our framework HSR is an intermediate goal, with improved health outcomes positioned as final goals (see Figure 1). This is because the intermediate health goals defined by WHO (i.e. access, coverage, quality, and safety) interrelate with their eight domains of responsiveness (i.e. autonomy, choice, communication, confidentiality, dignity, quality of amenities, prompt attention, access to family and community support)26,29. Therefore we have used the intermediate goals as proxy measures for HSR. Definitions of the intermediate goals are found in Table 1.
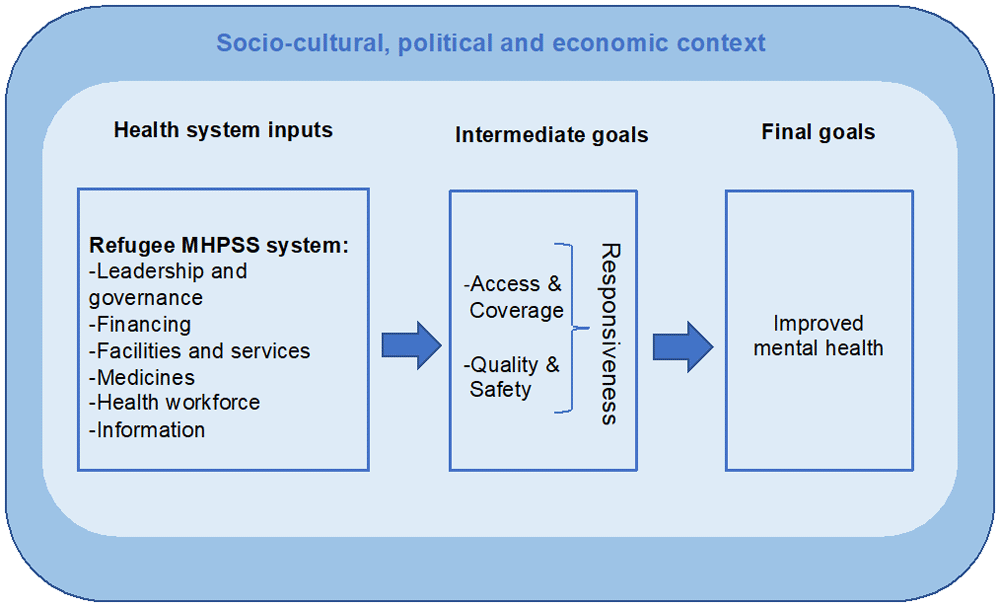
Figure 1. Conceptual framework on MHPSS system responsiveness to refugees’ needs, adapted from Fuhr, Roberts26.
Table 1. Definitions of intermediate health goals.
| Goals | Definitions |
|---|
Access and
coverage
(seven
elements) | i) Availability – the volume (coverage) and type of existing services and whether this is adequate for the volume and
needs of services users31. |
ii) Accessibility – the relationship between the location of the services and the location of the people in need of them
(e.g. transportation, travel time, distance, and cost)31. |
iii) Accommodation – the relationship between the organisation of resources (appointment systems, hours
of operation, walk-in facilities) and the ability of service users to accommodate to these factors31. |
| iv) Affordability – the prices of services in relation to the income of service users31. |
v) Acceptability – the relationship of attitudes of service users about personal and practice characteristics of services
to the actual characteristics of the existing services, including providers attitudes about acceptable personal
characteristics of service users31. |
| vi) Awareness of mental health and information about available MHPSS services. |
vii) Stigma towards mental health and seeking MHPSS services, with stigma defined as the co-occurrence of labelling,
stereotyping, separation, status loss, and discrimination in a context in which power is exercised32. |
| Quality | The scope of care (and quantity) which is provided to the patient (i.e. the amount of care necessary to achieve a
desired treatment outcome); the clinical quality of the service provided to the patients (e.g. cleanliness of the facility,
skills and decision-making of the provider, equipment and supplies); service quality and acceptability of the service
(e.g. convenience, interpersonal relationships)33. |
| Safety | The degree to which healthcare processes avoid, prevent and ameliorate adverse outcomes or injuries that stem
from the processes of healthcare itself34. |
The MHPSS system for refugees consists of two dominant subsystems: i) the ‘general MHPSS system’, which is commonly state governed and funded, and accessible to all citizens, including refugees with certain immigration statuses; and ii) the ‘parallel MHPSS system’, which is commonly run by non-governmental organisations (NGOs), civil society, and community groups and funded by UN organisations or from humanitarian budgets of donor countries. These parallel systems supplement care for vulnerable groups like refugees who are not (entirely) covered by or able to access the general MHPSS system. The type of MHPSS care provided in parallel systems is predominantly psychosocial support provided by non-specialists rather than specialist mental health services, which health professionals in the general system mainly provide. We recognise that in many contexts the MHPSS system is more complex. For example, in some countries there may be an overlap and linkages between these two subsystems, for example via referral pathways, while in other countries the private sector plays a large role in the health system30. We applied the simplified framework to this comparative rapid appraisal.
Data collection
In line with other rapid appraisals, a mixed-methods approach was used, with four different elements that used quantitative and qualitative methods, detailed below. Data collection and analysis was done iteratively by multiple team members, including local research partners. Supplementary File 2 in the Extended data gives an overview of all partner organisations and local ethical approvals27.
i. Structured literature reviews
Literature reviews were conducted for all eight countries. Selected databases and grey literature sources were searched for relevant qualitative and quantitative studies published between Jan 2011 and Sept 2021. Eligibility criteria and search terms are presented in Supplementary File 3, Extended data27. Database searches were conducted in English, with support from Endnote 20, and some grey literature searches in local languages (i.e. Dutch, German). Data from eligible studies was extracted and tabulated, listing source background (i.e. author, year, study country, objective, methods), summary of findings relevant to system responsiveness, and study population (i.e. refugees in general/asylum seekers/national population, country of origin, age). In total 436 studies were included in the literature reviews, covering single and multi-country studies. Most were conducted in Germany (n=135), followed by Jordan (n=94), Türkiye (n=52), the Netherlands (n=50), Sweden (n=50), Lebanon (n=49), Switzerland (n=27), and Egypt (n=13). A list of published sources, country level documents on specific indicators, and narrative reports on all countries are available on the STRENGTHS website. Supplementary File 4 in the Extended data contains all data extraction variables for the literature reviews27.
ii. MHPSS system indicators
Additionally, we searched selected websites and databases to obtain indicators covering general and parallel MHPSS systems (see Supplementary File 3 in the Extended data for data sources27). Indicators were derived based on the conceptual framework presented in Figure 1, and the Penchansky and Thomas31 framework (Box 1). Supplementary File 5 in the Extended data shows the entire list of indicators27. Relevant information was extracted and tabulated. If particular items of information could not be found, a search was conducted by local partners and, if not found, it was listed as ‘unknown’.
iii. Qualitative interviews
Qualitative interviews conducted in other components of the STRENGTHS project in the study countries were reanalysed for findings relevant to our study objectives. They included individual semi-structured interviews and focus group discussions (FGDs) with MHPSS providers, key-informants, and Syrian refugees. They had been conducted for three purposes: formative research for cultural adaptation of scalable psychological interventions; process evaluations of pilot and definitive RCTs of the psychological interventions; and scalability assessments of the psychological interventions. MHPSS providers and key informants were purposively sampled to include people from a variety of backgrounds and expertise. MHPSS providers included psychologists, psychiatrists, primary care providers, social workers and nurses working in mental health. Key informants included researchers, NGO workers, policy makers and advisors. Syrian refugees included a mix of those who had used MHPSS services before and those who had not. Syrian refugees interviewed were predominantly recruited from the STRENGTHS’ RCTs (Table 2). In total 228 interviews with individuals were included in the analysis. Additionally, summaries of FGDs with Syrian refugees were included in Jordan (12 groups; n=72), the Netherlands (4 groups; n=14), and Switzerland (2 groups; n=20). All qualitative data was collected between May 2017 and October 2021.
Table 2. Individual interviews by type of respondent and country.
| Country | Sample | MHPSS provider
(PR) | Key informant
(KI) | Syrian refugees
(SR) | Total |
|---|
| Egypt | 1 | 5 | 40 | 46 |
| Germany | 9 | 9 | 10 | 27 |
| Jordan | 14 | 7 | 15 | 36 |
| Lebanon | 3 | 0 | 0 | 3 |
| Netherlands | 36 | 17 | 22 | 75 |
| Sweden | 4 | 9 | 7 | 13 |
| Switzerland | 5 | 5 | 4 | 14 |
| Türkiye | 7 | 7 | 0 | 14 |
| Total | 79 | 59 | 57 | 228 |
iv. MHPSS access surveys
We also drew on data on previous utilisation of mental health care collected in the STRENGTHS project as part of the baseline for the RCT in Egypt (n=322), Germany (n=364), Lebanon (n=232), the Netherlands (n=206, Sweden (n=117), Switzerland (n=59), and Türkiye (n=368). Data for Jordan could not be used due to a data collection problem. In Egypt, Germany, the Netherlands, Sweden and Switzerland, the respondents were adult Syrian refugee women and men enrolled in the study with high levels of psychological distress (scoring above 15 on the 10-item Kessler Psychological Distress Scale (K10)) and functional impairment (scoring above 16 on the WHO Disability Assessment Schedule 2.0 (WHODAS 2.0)). For Lebanon, participants were official caregivers of children scoring 12 or above on the 17-item Paediatric Symptom Checklist. The respondents were asked whether they had experienced feelings such as anxiety, nervousness, depression, insomnia or any other emotional or behavioural problems since their displacement (and prior to their enrolment in the STRENGTHS RCT). If they had experienced these feelings, they were asked whether they had sought care for these feelings. Further details are available elsewhere35,36.
Ethics approval
Ethical approval for primary data collection (i.e. qualitative interviews, MHPSS access surveys) was provided by the Ethics Committee of the London School of Hygiene & Tropical Medicine (14330 -1) in the UK. Additionally, local ethical approval was sought by STRENGTHS partners in all study countries and granted by local ethics boards (see Supplementary File 2 in the Extended data27). All respondents in primary data collection gave written informed consent. Data protection, sharing, and confidentiality measures were in place.
Data analysis and synthesis
Primary and secondary data were extracted and analysed according to the MHPSS responsiveness conceptual framework (Figure 1)26. Quantitative primary data was analysed with Stata SE 17.0 and qualitative primary data was analysed with NVivo 12.6.1 and Atlas. TI 22.0.1. Since the interviews were collected primarily for other purposes, only units of data relevant to our conceptual framework were deductively coded and included in country reports. Preliminary findings were presented in country reports using a systematic narrative approach, structured according to our conceptual framework, and updated three times during the project (2017–2021). Several quality assurance processes were in place, such as training of interviewers (for primary data collection), verification of findings by local experts, and triangulation of methods. The final country reports were used to develop a comparative narrative synthesis.
The comparative synthesis drew on the approach for synthesis of multi-country qualitative research data used by Spicer, Aleshkina37. This synthesis was led by KIT and LSHTM teams, and followed six phases: 1) Reading of country reports and developing rationale for focusing on selected categories for comparison by two analysists from KIT; 2) KIT and LSHTM teams agree on rationale, focus and approach; 3) Cross-country findings analysed and summarised by the first analyst (ASB) with support from the second analyst (AW). Summaries of key findings were tabulated; 4) The paper was drafted by the second analyst and circulated to KIT and LSHTM for feedback on clarity and coherence; 5) The revised paper was reviewed by country teams to check accuracy of study findings, add information where needed, and to agree on the synthesis.
Results
Findings are structured according to the key elements in our conceptual framework, starting with the wider context, and ending with mental health outcomes. As we conceive HSR as overlapping with intermediate health goals, results are focused on these goals. Country reports with more detail on all elements of the framework, including used sources, are available on the STRENGTHS website.
Socio-cultural, political, and economic context
Health systems are embedded in and influenced by the wider socio-cultural, political, and economic context. While data from all four methods were triangulated to develop synthesis findings on the context, most were drawn from structured literature reviews and MHPSS indicators. Supplementary File 6 in the Extended data contains more elaborate summary results on context and inputs, including references to original sources27. Table 3 gives a summary overview of contextual indicators.
Table 3. Summary results on contextual factors.
| Egypt | Germany | Jordan | Lebanon | Sweden | Switzerland | The
Netherlands | Türkiye |
|---|
GDP per capita in
2020 (current USD)
and income group | 3,569.2 USD
Lower-MIC | 46,252.7 USD
HIC | 4,282.8 USD
Upper-MIC | 4,649.5 USD
Upper-MIC | 52,274.4 USD
HIC | 87,100.4 USD
HIC | 52,396 USD
HIC | 8,536.4 USD
Upper-MIC |
Total
unemployment in
2020 (% of total
labour force) | 7.9% | 3.8% | 19.2% | 11.4% | 8.3% | 4.8% | 3.8% | 13.1% |
Migration
Integration Index in
2019 (0-100)a | - | Health: 63
Overall: 58 | - | - | Health: 83
Overall: 86 | Health: 83
Overall: 50 | Health: 65
Overall: 57 | Health: 69
Overall: 43 |
Languages spoken
(%) | Modern Standard
(Egyptian) Arabic
(68%),
Sa’idi Arabic (29%).
Arabic (2%) | German (94%),
English (32%),
French (9%);
Russian (8%) | Arabic, English
widely spoken | Lebanese Arabic
(official), English
and French widely
spoken, Armenian | Swedish, and most able
to speak English | (Swiss) German (63%),
(Swiss) French (23%),
(Swiss) Italian (8%),
Romansh (<1%) | Dutch (98%),
majority also speak
English and German | Turkish (90%),
Kurdish (6%), Arabic
(1%), other (3%) |
The religion
practised in country
(%) | Islam (95%),
Christianity (5%),
other (<1%) | Christianity (61%), non-
religious (30%),
Islam (4%), other
(5%) | Islam (95%),
Christianity
(4%),
other (1%) | Islam (54%),
Christianity (40%),
Druze (6%) | Christianity (63%), non-
religious (35%), Islam
(2%), other (<1%) | Christianity (68%),
non-religious (24%),
Islam (5%), other (3%) | non-religious (68%),
Christianity (25%),
Islam (5%),
Hinduism and
Buddhism (2%) | Islam (80%),
Christianity (5%),
non-religious (7%),
other (8%) |
Number of
registered Syrian
refugees (year;
% total host
population) | 131,232 Syrian
refugees registered
(2021; 0.1%) | 572,818 Syrian
refugees
registered (2019;
0.7%) | 670,637 Syrian
refugees
registered
(2021; 6.6%) | 865,531 Syrian
refugees
registered (2020;
12.7%) | 123,431 Syrian asylum
seekers (2011–2020;
1.2%) | 21,105 Syrian asylum
seekers (2011–2020;
0.3% | 27,284 Syrians
granted residence
permits (2010–
2020; 0.2%) | 3,574,800 Syrian
refugees registered
(2021; 4.2%) |
Proportion of Syrian
refugees living
in camps in host
country (%) | Syrian refugees in
Egypt do not live in
camps but are living
among Egyptian
communities across
Egypt. | Newly arrived
Syrian refugees
begin in a
reception centre
but eventually
move into the
community
in one of the
country’s sixteen
states. | Approximately
17% of Syrian
refugees live in
camps. | Unknown as
official camps (e.g.
UNHCR camps) are
not allowed. | Asylum seekers are
offered accommodation
by the Swedish
Migration Agency (e.g.
apartment, centre,
house) or can live in
private accommodation. | All asylum seekers
live in one of the six
federal reception and
processing centres
across the country
for the first months
before being settled
into a host canton. | Asylum seekers
live in one of
the reception
centres for the
first months and
are then housed
by municipalities
across the country. | Approximately 6%
of Syrian refugees
remain in refugee
camps. |
In brief our contextual analyses showed that the three upper middle-income countries (MICs) hosted the largest number of registered Syrian refugees, with the highest absolute number in Türkiye (3,574,800). In Lebanon, Syrian refugees made up 12.7% of the total population, followed by Jordan (6.1%) and Türkiye (4%). Many refugees are not registered so actual numbers may be much higher. Most Syrian refugees lived in host communities rather than camps, although in the four high-income countries (HICs) Syrian asylum seekers initially resided in reception centres or, in the case of Sweden, private accommodation or other accommodation provided by the Swedish Migration Agency. Egypt, Jordan, and Lebanon are, like Syria, predominantly Arabic-speaking and Muslim countries. Whether Syrian refugees can work depended on their legal status and country-specific regulations. Unemployment rates were much higher in host populations in MICs compared to HICs. Refugee children were entitled to education in all eight countries, however, many access barriers to education were reported (e.g. legal status, poverty, transportation, quality of education). Sweden had, according to the Migration Integration Policy Index, the most favourable political context (compared to the four HICs and Türkiye) in relation to the integration of refugees and their health.
Health system inputs: refugee MHPSS system
Health systems can be represented as six building blocks (leadership and governance; financing; facilities and services; health workforce; medicines; and information), which through intermediate goals (access, coverage, quality, safety) reaches its final goal. Table 4 shows selected indicators on health system inputs.
Table 4. Summary results on health system inputs.
| Egypt | Germany | Jordan | Lebanon | Sweden | Switzerland | The Netherlands | Türkiye |
|---|
Leadership and
governance | | | | | | | | |
Mental health
policy | Yes | Yes | Yes | Unknown | Yes | No | Yes | Yes |
| Mental health plan | Yes | No | Yes | Unknown | Yes | Yes | Yes | Yes |
Mental health
legislation | Yes | No (covered in
other laws) | No | Yes | Decentralised to
municipalities | No (covered in
other laws) | Yes | Yes |
| Financing | | | | | | | | |
| % GDP on health | 5.6% | 11.4% | 7.7% | 6.0% | 10.8% | 11.9% | 9.9% | 4.1% |
% health
expenditure on
mental health | 0.5% | 11.0% | Unknown | 4.8% | Unknown | Unknown | 10.7% | Unknown |
% mental health
expenditure
towards mental
hospitals | Unknown | 11.3% | Unknown | 54.0% | Unknown | Unknown | 59.2% | Unknown |
% funding sources
for health system | Unknown | 77% social
security | 8.8% social
security, 30.7%
out-of-pocket | 52.5% social
security, 36.4%
out-of-pocket | Regional taxes,
13.8% out-of-
pocket | 71.5% social
security, 26.8%
out-of-pocket | 93.0% social security,
10.1% out-of-pocket | Unknown |
Costs utilising
MHPSS services for
refugees | None | None, but
coverage varies | Same as
uninsured
Jordanians and
coverage varies;
no cost at UNHCR
facilities | LBP 3,000 – 5,000
(1.75 – 3 EUR) for
consultation at
UNHCR facilities | Largely none, same
cost as for Swedish
citizens; can apply
for reimbursement
of out-of-pocket
fees | None if approved
by a doctor or
psychiatrist | Same as Dutch
citizens, pay the cost
of monthly insurance
premiums and out-of-
pocket costs | Once
registered,
same as
Türkiye’s
citizens. |
Facilities and
services | Ministry of
Health main
mental health
service provider.
MHPSS is
not yet fully
integrated into
PHC, and so
refugees either
pay specialists
or utilise NGO
services in the
parallel system. | All psychosocial
services are
available in the
public sector.
Alternatively,
refugees have
access to the
parallel system
in which many
organisations
offer
counselling. | Syrian refugees
can access
MHPSS through
primary care,
which is
increasingly
integrated, or
through UNHCR
and NGO
facilities that are
accessible at no
cost. | NGOs are
extensively
involved in care
provision (in
2006, over 80%
of the 110 PHC
centres and 734
dispensaries are
owned by NGOs).
A variety of
MHPSS is offered
to the general
population. | Refugees are
identified and
treated for mild
mental health
issues within PHC;
Syrian refugees
may be referred
to providers
who specialise in
treating this group,
who may be in a
parallel system. | Syrian refugees
with mental health
needs are referred
by nurses/social
workers in asylum
centres to PHC,
where GPs can
diagnose, treat,
and refer. Referral
is possible to
general socio-
psychiatric facilities,
outpatient clinics
for traumatised
migrants, or tertiary
care. | Early detection of
mental health issues
through prevention/
refugee integration
programmes in
the social domain;
screenings at
asylum centres;
PHC providers in
asylum centres or
communities. GPs can
treat or refer patients
to secondary or
tertiary care levels. | Syrians with
temporary
protection
status can
access
PHC and
community
mental health
centres for
diagnosis,
treatment,
and referral.
Those without
temporary
protection
status can
access
emergency
care in
hospitals. |
| Medicines | | | | | | | | |
| Essential drugs list | Yes | Yes | Yes | Yes | Yes, determined at
the county level | Yes | No, but registered
drugs list available
and measures to keep
them affordable. | Yes |
Psychotherapeutic
medicines included
in the list | Yes | Yes, under
‘neurological
diseases’ | Yes | Yes | Dependent on
county | Yes, under
‘neurological
diseases’ | N/A | N/A |
Cost of
psychotherapeutic
medicines | Unknown;
80.0% of the
population have
free access | Covered by
insurance | Unknown | Not covered by
social insurance
schemes, free at
UNHCR facilities
(but must pay
consultation fee) | Up to €109
annually for drugs
within the national
insurance scheme,
or €218 for drugs
not covered | Unknown | Up to €385 annually | Unknown |
PHC doctors
authorised
to prescribe
psychotherapeutic
medicines | Unknown | Yes | Unknown | Yes | Yes | Yes | Yes | Yes |
Health
workforce | | | | | | | | |
Mental health
workers per
100,000 | 8.40 mental
health workers,
1.6 psychiatrists,
0.26
psychologists,
4.8 mental
health nurses,
0.45 social
workers | 27.45
psychiatrists,
49.55
psychologists,
56.06 mental
health nurses | 7.8 mental health
workers, 1.125
psychiatrists,
1.266
psychologists,
3.297 mental
health nurses,
0.218 social
workers | 1.21 psychiatrists,
3.8 psychologists,
3.14 mental
health nurses,
1.33 social
workers | 20.86 psychiatrists,
0.93 psychologists,
50.57 mental health
nurses, 18.42 social
workers | 41.42 psychiatrists,
40.78 psychologists | 24.23 psychiatrists,
90.76 psychologists,
2.87 mental health
nurses | 1.64
psychiatrists,
2.54
psychologists,
0.76 social
workers |
Distribution of
mental health
professionals
between urban
and rural areas | Uneven | Uneven | Relatively even | Unknown | Uneven | Unknown | Unknown | Unknown |
Mental health
or cultural
competency
training | Covers
psychological
first aid and
basic mental
health care | None for
undergraduate;
majority of PHC
doctors have
not received
official in-service
mental health
training in last 5
years | Insufficient | 3% of training
for doctors, and
6% of training
for nurses, is
dedicated to
mental health | Unknown, although
nurses receive
theoretical and
clinical training in
mental illness | Cultural vcompetency
training is provided
in under- and
postgraduate
curricula for
medical students
and residents | Care for patients
with psychological
complaints is part of
GP training; nurses
can specialise in
mental health | Majority of
PHC doctors
have not
received
official in-
service mental
health training
in last 5 years |
| Information | | | | | | | | |
Data on the
epidemiology of
mental disorders
collected at the
national level | Unknown | Yes | Unknown | Yes | Yes | No | Yes | Unknown |
Mental health data
disaggregated
refugees | Unknown | No | Future plans to
disaggregate
health data by
refugee status;
Unknown if
includes mental
health | No | Unknown | No | No | Unknown |
NGO collection of
refugee mental
health data | Unknown | Unknown | Unknown | Database of the
Lebanon Crisis
Response Plan
encourages
partners to collect
disaggregated
data for displaced
Syrians, although
includes limited
data on mental
health indicators | NGOs involved in
MHPSS for refugees
publish data within
their annual reports | Unknown | NGOs involved in
social support do
not consistently
publish data, aside
from the Dutch
Refugee Council.
Knowledge centres
Pharos and ARQ
active in gathering
and distributing
information on
refugee mental health | Unknown |
In terms of information and governance, we found that information on the mental health of refugees was not routinely collected at national level in any country. All countries have a mental health policy or plan in place (unknown for Lebanon) and all, except Jordan, have specific mental health legislation. Mental health is integrated into primary health care (PHC) in the four HICs, and increasingly in the four MICs (e.g. mainly through expansion of the WHO Mental Health Gap Action Programme (mhGAP) involving training and supervision of non-specialist providers).
With regard to financing and services, we found that mental health received 0.5-11.0% (based on four countries) of national health budgets, which ranged from 4.1 to 11.9% of GDP across the eight countries. Health budgets were consistently lower in MICs compared to HICs. Important to note here is that MHPSS can be delivered outside of health facilities and is often not funded through health budgets. Syrian refugees who are granted asylum have the right to access similar MHPSS services under the same financial requirements as national citizens in Sweden, the Netherlands and Türkiye. In Germany and Switzerland local authorities determine financial access and coverage. In Jordan financial regulations for Syrian refugees for healthcare in governmental facilities changed regularly in recent years, with the latest regulation permitting refugees to access services for the same prices as uninsured Jordanians. Governmental PHC facilities and providers act as gatekeepers to specialist mental health services in the four HICs. In Türkiye, Lebanon, Jordan, and Egypt, PHC facilities are commonly run and financed or co-financed by NGOs, with MHPSS services increasingly integrated in their services. Refugees registered with the UNHCR or the government can access these NGO or government-NGO services generally at no cost and be referred to more advanced mental health care in the general health system. MHPSS services are more financially and legally restricted for unregistered refugees and asylum seekers compared to registered refugees and the host population. Separate facilities and services for children were not widely reported on, although in Lebanon it was noted that children with mental health needs are often first identified through awareness programmes in schools and referred through the same pathway as adults.
Assessment of the health workforce shows, as expected, that the four HICs had much higher numbers of psychiatrists and psychologists than the four MICs. The rural-urban distribution of the mental health workforce was rated in the WHO Assessment Instrument for Mental Health Systems as ‘disproportionate’ in Egypt and ‘relatively proportionate’ in Jordan. Other sources suggest this distribution was uneven in Germany and Sweden (for the other countries we rated this indicator as ‘unknown’). While NGOs serve as alternative health providers for Syrian refugees, particularly in the four MICs, there is limited publicly available data on the mental health workforce in parallel systems. Similarly, there are gaps in data on the mental health and cultural competency training of PHC nurses and doctors, although the limited information that we found may indicate training and supervision of non-specialists to be insufficient across all countries.
Finally in relation to medicines our appraisals confirmed that medicines for mental and behavioural disorders are available in all countries. Costs of medicines were either unknown or covered by health insurance up to a certain amount. PHC doctors in all countries were authorised to prescribe psychotherapeutic medicines (except for Jordan and Egypt where this was unknown).
Intermediate goals: responsiveness
Access and coverage, and quality and safety are intermediate health system outcomes, affecting care seeking and eventually health outcomes. All four methods were used and combined to generate these findings. Findings drawn from secondary data (i.e. literature reviews and MHPSS indicators) are referenced with an original source. If no reference is provided, those findings are drawn from a primary data source (i.e. qualitative interviews and/or survey data from STRENGTHS study).
Access & coverage. Availability and accessibility of mental health services were concerns in all countries. Demand outstrips supply of mental health resources, with insufficient numbers of mental health workers and/or services reported in Egypt, Jordan38–40, Türkiye, Switzerland41–44, Sweden45,46, Germany47–50, and in Lebanon:
Only the Netherlands reportedly had sufficient resources51,52, though it was noted that this was limited in rural areas53. Egypt similarly reported rural areas having fewer providers and MHPSS services54, while in Jordan there seemed to be a shortage in urban environments55. The unequal distribution of resources contributes to accessibility barriers, and the need to travel to seek services was perceived as a barrier not only in the Netherlands but also in Sweden, Switzerland, Germany, Lebanon, Jordan, and Türkiye. Travel was described as a challenge due to the time it took, the distance required, safety, the cost of the journey, and cultural norms surrounding women traveling38,56–60. Both Syrian men and women struggled to attend MHPSS services as explained by a key informant:
“Women are going through a hard time. Some of them cannot leave their houses. Thus, they cannot attend activities. It’s hard reaching out to the male group because they are working.” (Key informant, Türkiye)
Limited availability of culturally competent providers was reported in the Netherlands, Sweden, Germany, Switzerland, Egypt, and Türkiye. This is important, as acceptability seems to be a key issue across countries. Cultural and language barriers, as aspects of acceptability, were predominantly mentioned in European countries, likely due to the greater differences with Syrian society both culturally and linguistically47,48,53,61–66. A Syrian refugee in the Netherlands highlighted this communication challenge:
“They [primary health professionals] have been trying to find me a psychiatrist or psychologist to help me relieve the pains a little bit, but the problem is that the communication was very hard; that they couldn’t find me an Arabic[-speaking] doctor.” (Syrian refugee, the Netherlands)
There was low recognition by medical professionals of mental health issues by Syrian refugees when these are presented primarily through somatic symptoms in Switzerland67, the Netherlands53, Sweden, and Germany. Language barriers were not an issue in Jordan, Egypt, and Lebanon, but despite many similarities, a failure to provide culturally sensitive services may still present a challenge.
Stigma and limited mental health awareness in the Syrian community were reported barriers across all countries in the published literature38,41,53,60–62,68–72 and in our primary data. Our survey found that low mental health awareness, including beliefs about effectiveness of treatment and knowledge about where to seek help, generated barriers for Syrian refugees seeking support. It was widely reported that Syrian refugees may delay or refuse to seek support for mental health issues due to stigma rooted in a cultural belief that those who need MHPSS are “crazy”73:
“In my environment, I haven't ever heard of someone visiting a psychiatrist or even considering doing such no matter what they are going through [...] people may think you're crazy or something when you visit a psychiatrist” (Syrian refugee, Egypt)
Recommendations to overcome cultural acceptability barriers include: expanding cultural sensitivity training for providers, which may decrease their use of stigmatising language74,75; increasing awareness around mental health in the Syrian community; and ensuring access to either a professional interpreter41–44 or Arabic-speaking doctor.
In terms of affordability, the costs associated with professional interpreters were perceived as a barrier by health providers in the Netherlands75, Germany47,48, Türkiye, and Switzerland42. In contrast in Sweden, all non-native speakers accessing the health system have the legal right to an interpreter hired by Swedish authorities. Additional affordability concerns for Syrian refugees accessing the health system in the Netherlands extend to paying costs in excess of those covered by health insurance, while Germany also imposes co-payments for treatment. Costs for specialist mental health services were only covered by health insurance for Syrian asylum seekers in Sweden if this was deemed ‘necessary’. Overall, affordability concerns seemed to be more prevalent in MICs, which could be contributed to their economic status and having less developed welfare systems. For example, caregivers of children in the STRENGTHS’ RCT in Lebanon reported perceived cost of services as the principal reason for not seeking care (79%). A MHPSS provider in Jordan commented about the unaffordability of private mental healthcare:
In Egypt and Lebanon, Syrian refugees often have to pay out-of-pocket for psychological services in the general health system76. In Jordan, out-of-pocket costs for public healthcare were reduced (subsidised 80%) due to a policy change in 2019, however, unaffordability of public health was reported to remain a significant barrier for Syrian refugees to accessing public health services77. The cost of medications and transportation of people to health facilities in particular may be prohibitive in Jordan38,56,78. Lebanon, Germany, Switzerland, the Netherlands, and Türkiye74 also reported affordability barriers concerning the cost of transportation to services.
Information on accommodation was limited in the literature and therefore is solely based on primary data from the STRENGTHS RCTs. “Felt it would take up too much time/be inconvenient” was a principal reason for not seeking care reported amongst Syrian refugees participating in our MHPSS access surveys. Qualitative interview data further demonstrated that barriers to attending sessions of psychological interventions (in a research/RCT context) were lack of childcare and time, while facilitators were flexibility around appointment times, a convenient location, reimbursement of transportation costs, and the option of accessing the intervention online.
Information on access and coverage in parallel MHPSS systems was limited in all countries. While some psychosocial centres in study countries publish information on how many refugees they treat annually, they do not specify the proportions of people with a Syrian refugee background or provide information on access.
The findings from the MHPSS access survey data among adult Syrian refugee participants with elevated levels of psychological distress and functional impairment showed that 84% of them reported past emotional or behavioural problems since their displacement (ranging from 75% in Switzerland to 93% in Germany). Of these, 34% had previously sought care for these emotional problems (i.e., prior to enrolment in the STRENGTHS study) and this ranged from 24% in Egypt to 45% in Germany.
Quality & safety. For Middle Eastern countries, limited information was available on quality and safety of MHPSS systems for refugees. Among European countries, the main issue is long waiting times. Long waiting times for mental health care were reported in the Netherlands53,79, Sweden80,81, Switzerland, Lebanon, Jordan71, and Germany82:
In the Netherlands, it was noted that efforts were being made to reduce waiting times in specialist mental healthcare83. In Sweden, while 77% of patients accessed general health services within 90 days80,81, waiting lists for specialised psychiatric care were six to twelve months. This waiting time is similar to that reported for Germany82.
In Switzerland, a major concern was timely diagnosis. This is in part due to the time it takes a Syrian refugee to seek help in the first place, and in part due to the long waiting times for services; however, it may also be due to somatic presentations of distress impacting initial diagnosis. As mentioned above, psychological concerns often present somatically among Syrian refugees67, and if providers are not, or not sufficiently, trained in this they may miss cues and delay diagnosis and referral. Somatic presentations of distress amongst Syrian refugees were reported concerns in the Netherlands53, Germany, and Sweden. While a subsequent treatment delay was not explicitly mentioned in these countries, some comments made by interviewees indicated this was a challenge:
“When we [at NGO clinic] see [Syrian] patients, we often see that they have been circling around for quite some time in the health system. Because they have stomach problems, or headaches or pain in their body. And they have been sent around to various doctors to check the physical status. But it is rare for them to actually identify that there is something psychological behind the symptoms.” (Key informant, Sweden)
Language barriers affected service quality in the Netherlands64,65, and consequently so did the financial barrier created by the use of professional interpreter services. The fact that interpreters are not covered by health insurance also affected quality of care in Germany47,84,85. In Sweden, Syrian refugees were concerned that interpreters would not accurately communicate what the refugee wanted to express. In Switzerland, a lack of qualified interpreters was found to impact quality86,87:
“And when the interpreters then tell me that the therapists themselves are overwhelmed and do not know and are somewhat chaotic and confused and talk for too long or too short, then I notice that often the interpreter setting does not work. That in reality it often is not ideally applied because multiple people have not been trained enough for this setting.” (Health provider, Switzerland)
In Jordan88 and Lebanon, the small mental health workforce compromised service quality. In Lebanon, there was a lack of choice and providers when seeking care. In Jordan, there was a particular lack of specialised and qualified mental health workers38,57, leading to limited screening and referral78,89. Both Lebanon and Jordan also lacked certain quality assurance mechanisms. For example, Lebanon had no certifying body for psychotherapy90 while Jordan lacked a formal accreditation system78. There was limited information available on quality and safety of MHPSS services for Syrian refugees in Egypt, although one Syrian refugee described the negative experience of being prescribed sleeping pills rather than receiving the psychological support they sought. This is supported by accounts from key informants of the system’s emphasis on psychiatric diagnosis and psychopharmacologic treatment rather than psychological support. There was no information available on quality and safety of MHPSS services for Syrian refugees in Türkiye.
Information on quality and safety in parallel MHPSS systems was limited in all countries. MHPSS services offered by NGOs and civil society organisations in Germany reportedly had long waiting lists. Similarly in Switzerland, long waiting times in the outpatient clinics for victims of war and torture were reported. Syrian refugees in Egypt commented positively on the quality of psychological services they received through the nongovernmental sector.
Final goals: improve mental health
According to our conceptual framework, intermediate health outcomes influence health seeking behaviour and consequently the final goal, which are improved mental health outcomes. Studies included in our rapid appraisals typically did not make linkages between these outcomes or health system inputs. The majority of studies that reported on mental health outcomes focused on prevalence rates for depression, anxiety, and post-traumatic stress and were therefore used in this comparative synthesis. There were also studies reporting on other symptoms (e.g. prolonged grief disorder, psychological distress, psychological healthiness/wellbeing); however, these were excluded because they were less commonly reported and therefore more difficult to compare across countries.
We were not able to identify any nation-wide surveys of the prevalence of depression, anxiety, and post-traumatic stress among Syrian refugees in the study countries. Table 5 shows rates reported in several sub-national studies. Rates are for Syrian asylum seekers and refugees only. We excluded a considerable number of studies that did not present disaggregated data on Syrian refugees. Rates presented here need to be interpreted with caution: it is not an exhaustive list and rates are difficult to compare within and between countries due to differing methodologies, population groups studied (e.g. various age groups and stages of settlement), settings (e.g. camp-based, urban, health centre), and outcome measures (e.g. life-time or point prevalence; diagnostic criteria and tools). That said rates found amongst Syrian refugees and asylum seekers consistently appear much higher than those amongst the eight host populations, in which prevalence rates for depression ranges from 2.6 to 5.0% and for anxiety from 2.4 to 7.1%109–111 (no national figures available for post-traumatic stress). However, again caution is required in such comparisons given that the host population data are from Global Mental Health surveys, which have a different methodology.
Table 5. Observed prevalence (%) of common mental health symptoms for Syrian asylum seekers and refugees.
| Post-
traumatic
stress | Depression | Anxiety |
|---|
| Egypt | 33.591 | 30.091 | - |
| Germany | 11.492 | 14.592 | 13.592 |
| Jordan | 31.0-84.093–98 | 28.3-85.093,99,100 | 50.0-84.093,98,99 |
| Lebanon | 35.4-45.697,101 | 22.0102 | - |
| The Netherlands | - | - | - |
| Sweden | 29.9103 | 40.2103 | 31.8103 |
| Switzerland | - | - | - |
| Türkiye | 11.5-83.410,104–108 | 12.5-70.510,104–108 | 9.2-38.810,107,108 |
Discussion
The aim of this paper was to assess the responsiveness of health systems to the mental health needs of Syrian refugees in eight host countries. The prevalence of common mental disorders identified in our structured literature searches is in line with those found in systematic reviews and meta-analyses conducted amongst conflict-affected populations2,112, refugees and asylum seekers113,114, and Syrian refugees3,15. We found substantial heterogeneity, which can partly be explained by methodological differences. While there was no adequate information to link health system inputs with outcomes (intermediary and final), the poor outcomes found through our rapid appraisals are cause for concern and may point to health systems struggling to respond to the needs of Syrian refugees. Our study offers an insight into areas where responsiveness is particularly weak and how it may be improved.
Our conceptual framework explains that responsiveness to the mental health needs of individual Syrian refugees is achieved through intermediate health goals (access and coverage; quality and safety) and health system inputs (i.e. the six building blocks), which are embedded in a larger context (socio-cultural, political, economic). Therefore, a ‘response’ in our study means any action related to any of these levels (inputs, intermediate goals, context) that improves the mental health outcomes of Syrian refugees. Before we discuss ways to improve HSR, we first briefly discuss the main strengths and weaknesses in HSR towards the mental health needs of Syrian refugees.
Strengths and weaknesses in HSR
Our analysis reveals two notable strengths in HSR towards mental health needs of Syrian refugees. The first is that mental health is integrated in PHC in HICs and increasingly integrated in MICs, which is in line with global recommendations115. The second strength is that psychotherapeutic medicines were available in all study countries and, where known, PHC providers are able to prescribe them. These two strengths, however, have their limitations because of system-level resource and capacity challenges.
A shift from traditional hospital-based mental health care to primary care settings requires PHC providers (like GPs) to be competent in the detection, treatment, and referral of patients with mental health needs. Our findings indicate these competencies to be insufficient, because of limited mental health skills and cultural competency in PHC workers, limiting timely and appropriate diagnosis, treatment, and referral of Syrian patients. While in included HICs there were more mental health specialists, cultural and language barriers challenged the communication between Syrian refugees and health providers. This is mainly due to Arabic-speaking mental health professionals being limited in number and providing care through interpreters complicated (i.e. affordability, quality, confidentiality). Our findings showed that the availability of psychologists and psychotherapists was insufficient to meet the demand and therefore the health systems’ capacity for offering psychological therapies limited. In included MICs the number of mental health workers was even more limited and in addition systems in these countries may lack quality control structures for psychotherapy. Until these system-level resource and capacity challenges for psychotherapies are overcome, there is a danger that pharmacological treatment remains the dominant and only available treatment option for Syrian refugees with mental health needs in host populations.
Weaknesses in access and quality found in our study (e.g. stigma, language, cultural, knowledge/awareness, travel, costs, availability) are similar to those reported in reviews on access, barriers, and utilisation of MHPSS amongst refugees12,13,15. While some weaknesses were more profound in certain countries, like cultural and language barriers in European countries, and out-of-pocket costs in MICs, most weaknesses were shared across contexts. This means our following recommendations for ways to increase HSR will be relevant to most, if not all, eight study countries as well as similar refugee contexts. The order in which the recommendations are listed do not reflect their order of priority.
Recommendations
First, we recommend measures to strengthen the socio-economic situation of refugees. Our contextual analysis shows that employment of Syrian refugees was determined by existing policies; with rules varying by country, immigration status, work permits, and with fees for work permits possibly posing a financial obstacle for obtaining them. Similarly, our analysis highlighted that Syrian refugee children face access barriers to education. Unemployment, low income, and financial strain are social determinants of mental health and therefore can directly affect an individual’s mental health116. Having policies, and particularly practices, in place that reduce access barriers to education and employment are essential to create viable livelihoods for Syrian refugees. This would not only benefit their mental health directly (i.e. reduced stress) and indirectly (i.e. financial capacity to pay for and travel to services), but also protect refugees from taking illegal jobs – further putting their health at risk – and positively affect the integration of refugees into host countries. Making such structural changes will be a challenging process requiring political will and collaboration between the health and other sectors, such as those involved with social security and education. However, subsequent to our rapid appraisal study some European countries such as the Netherlands have implemented less strict employment rules specifically for Ukrainian refugees who fled the 2022 war, which may be extended to other refugee populations.
Second, we recommend rapidly expanding the mental health workforce. This may be achieved through the further implementation of recommended approaches like mhGAP and collaborative task-sharing – involving the transfer of some mental health care responsibilities from specialists to non-specialists115,117. Task-sharing approaches have a potential to address shortages of mental health specialists and reduce waiting times for specialist mental health care, which were major quality concerns put forward by our cross-country examination. For example, in Türkiye mhGAP training of primary care doctors was found useful in responding to the mental health needs of Syrian refugees, although refresher trainings were recommended118. Recent findings from the STRENGTHS project21 have shown that task-sharing psychological interventions like Problem Management Plus can significantly minimise distress under Syrian refugee beneficiaries119 and are scalable when taking into account key influencing factors and actors120–123. Similar results were found in a recent meta-analysis of the effectiveness of Problem Management Plus and its digital adaptation called Step-by-Step124. That said, further research is needed on how to sustain the health benefits of such interventions125.
Third, we recommend increasing the cultural competencies of the health workforce. The WHO recently developed Global Competency Standards to set a benchmark for the health workforce in providing culturally sensitive care to refugees and migrants126. Cultural competence training of mental health specialists and non-specialists can help providers to recognise presentations of distress specific to Syrian culture and to better understand and respond to the fear and stigma associated with mental illness amongst Syrian communities14,127,128. This again would enable more culturally appropriate and timely diagnosis, treatment, and referral. In non-Arabic speaking countries our results indicate it is vital in this regard to also increase the availability, affordability, and quality of professional interpreter services as well as to diversify the mental health workforce, such as through hiring Arabic-speaking health workers or cultural mediators. Participation of refugees themselves was reported important but underutilised in a review on current efforts to create more culturally sensitive refugee services129, meaning this should be considered in future initiatives.
Fourth, we recommend increasing mental health awareness, including knowledge of mental health resources, and reducing mental health stigma among refugee communities. A recent Lancet commission calls for more action on ending stigma and discrimination in mental health worldwide and recommends the involvement of people with lived experience of mental health conditions in anti-stigma programmes130. Other studies showed more research is needed on the effectiveness of anti-stigma interventions tailored to refugees128,131.
Fifth, we recommend strengthening national health information systems. Our results indicate that information on the mental health of Syrian refugees (and other refugees) was not routinely collected at national level in all study countries. Publicly available information on the parallel MHPSS systems was extremely limited. To offer a more holistic picture of the current situation, information from both general and parallel MHPSS systems need to be consolidated and interrelated by the national government and relevant UN agencies and NGOs. Besides data gaps, we found many data to be old and difficult to compare across countries. Reliable, timely, and disaggregated information is vital for health system actors (e.g. policymakers, managers service providers) to be more responsive to the needs and expectations of Syrian refugees (as well as refugees from other nationalities), as well as for measuring progress on health inequalities and for stimulating accountability mechanisms.
Sixth, and underpinning our other recommendations, we advise increasing national funding for mental health. Our appraisal showed that only 0.5–11.0% of national health budgets (which ranged from 4.1 to 11.9% of GDP) were allocated to mental health. This amount is disproportionate of the heavy individual, social, and economic burden of mental illness. Based on data from 28 EU countries, the OECD predicts the economic and social costs of mental ill-health to be more than 4% of GDP132. As previously recommended115,132, more efficient use of mental health funding is needed, including more investment in community-oriented care133. Strengthened MHPSS care in routine health and social care platforms has the potential to overcome some of the access barriers reported in this synthesis (e.g. unequal rural/urban distribution, physical access, and stigma).
Limitations
Our study has several limitations. Firstly, publicly available data on some key indicators was scarce, with variations in data collection tools and years across countries challenging cross-country comparison and drawing definitive conclusions. Secondly, while reanalysis of primary qualitative data is pragmatic and time-reducing (and therefore befitting of rapid appraisals), it meant that not all interview data was relevant to our research objectives, nor did it help to fully address our objectives. Thirdly, our structured literature reviews included literature from various sources (e.g. peer-reviewed journals and grey literature like NGO reports) without performing quality assessments. While this led to inclusiveness and breadth in our synthesis, the results presented here may repeat those from poor-quality studies. A central issue in rapid appraisals is to find a “balance between speed and trustworthiness”25. To account for these limitations, findings were discussed with country teams (who were involved in primary data collection and knowledgeable about the local context and literature) and the wider team of researchers involved in the synthesis. Also, triangulation of various data collection methods and perspectives validated our interpretations. Fourth, our study will be difficult to reproduce due to the number of methods and data used. To redress this, further information on our data can be found in the Supplementary Files, and authors can be contacted for more details. Fifth, since our focus was on MHPSS systems, issues such as social determinants of health were not addressed as much; however, we recognise their importance and recommend that this be a focus of future studies. Sixth, it was the beyond the scope of our analysis to compare HSR for Syrian refugees with citizens, however, this could be taken up by future research to generate further insights into common and refugee-specific bottlenecks in the MHPSS system.
Conclusions
This study is the first to assess and compare HSR to the mental health needs of Syrian refugees across countries. Our rapid appraisals show that all eight host countries struggle to provide responsive MHPSS care to Syrian refugees. The many issues in access to quality care found in our synthesis may explain why Syrian refugees struggle to seek support and have poor mental health outcomes.
While various positive changes have been made in the general health systems of study countries, such as increasing the integration of mental health into primary care, many problems remain. Parallel nongovernmental MHPSS systems may be more responsive than state systems. However, in the long run, these parallel structures may be less sustainable and can undermine efforts to strengthen national health systems.
Strengthening the capacity of the mental health workforce (in quantity, quality, diversity, and distribution) is urgently needed to enable care-seeking for vulnerable populations like Syrian refugees and reduce waiting times in mental healthcare. Increased financial investment in mental health and improved health information systems (i.e. regularly updated disaggregated data) are crucial. More refugee-responsive MHPSS systems will benefit not just Syrian refugees and refugees of other nationalities but likely also migrants and host populations. A social determinants of health approach can be recommended to address the complex mental health needs of the refugees, and this may include MHPSS interventions as well as a range of socio-economic policies.
Ethics and consent
Ethical approval for primary data collection (i.e. qualitative interviews, MHPSS access surveys) was provided by the Ethics Committee of the London School of Hygiene & Tropical Medicine (14330 -1) in the UK. Additionally, local ethical approval was sought by STRENGTHS partners in all study countries and granted by local ethics boards (see Supplementary File 2 in the Extended data27). All respondents in primary data collection gave written informed consent. Data protection, sharing, and confidentiality measures were in place.