Introduction
Onchocerciasis is a neglected tropical disease primarily found in Africa, caused by the filarial nematode Onchocerca volvulus and transmitted through bites of infectious blackflies (Simulium spp.)1. Onchocerciasis is known to cause dermatitis and blindness (“river blindness”) and is associated with a clinical spectrum of seizures and disorders grouped under the term onchocerciasis-associated epilepsy (OAE)2. In areas where there is high ongoing O. volvulus transmission, children are at risk of developing OAE, with seizure onset typically occurring between the ages of three to 18 years2. Prevention of onchocerciasis depends mainly on community-directed treatment with ivermectin (CDTi) in at-risk communities, which can be supplemented with vector control activities to eradicate the blackflies3.
Annual CDTi was introduced in South Sudan in the early 2000s. However, there have been several years without treatment due to insecurity, which has allowed the disease to remain endemic in the area. The CDTi programme effectively resumed annually in Maridi in 2017. Although CDTi was interrupted in 2020 because of the COVID-19 pandemic, it has been re-introduced biannually (six-monthly) since 2021.
Onchocerciasis transmission was assessed in December 2019 via an Ov16 serosurvey in children three to nine years of age and found a seroprevalence of 24.5%4. As these findings indicated high onchocerciasis transmission, a community-based vector control strategy, “Slash and Clear”, has been implemented at least once a year at the Maridi Dam since December 2019 (Figure 1)5. This strategy consists of clearing the trailing vegetation to eliminate the blackfly breeding site and reduce biting density in the nearby communities.

Figure 1. Slash-and-Clear at the Maridi Dam, South Sudan.
In February 2023, a follow-up O. volvulus serosurvey was conducted among children aged three to nine years in Maridi to evaluate possible changes in transmission patterns. This paper presented the effect of strengthening the onchocerciasis elimination interventions on the O. volvulus seroprevalence of children within the specified age range using the Ov16 SD BIOLINE rapid diagnostic test (RDT).
Methods
Ethical standards
Ethical approval for this study was obtained from the University of Antwerp’s ethics committee (Ref: BUN B300201940004) and from the ethics committee of the Ministry of Health of South Sudan (MOH/RERB 56/2022). All participants were recruited only after informed parental consent was granted (and assent for children aged seven years and above). The research procedures were in compliance with the declaration Helsinki, and all personal data were treated confidentially.
Study setting
South Sudan is known to have multiple endemic hotspots of onchocerciasis, including Maridi County in the Western Equatoria State (Figure 2).
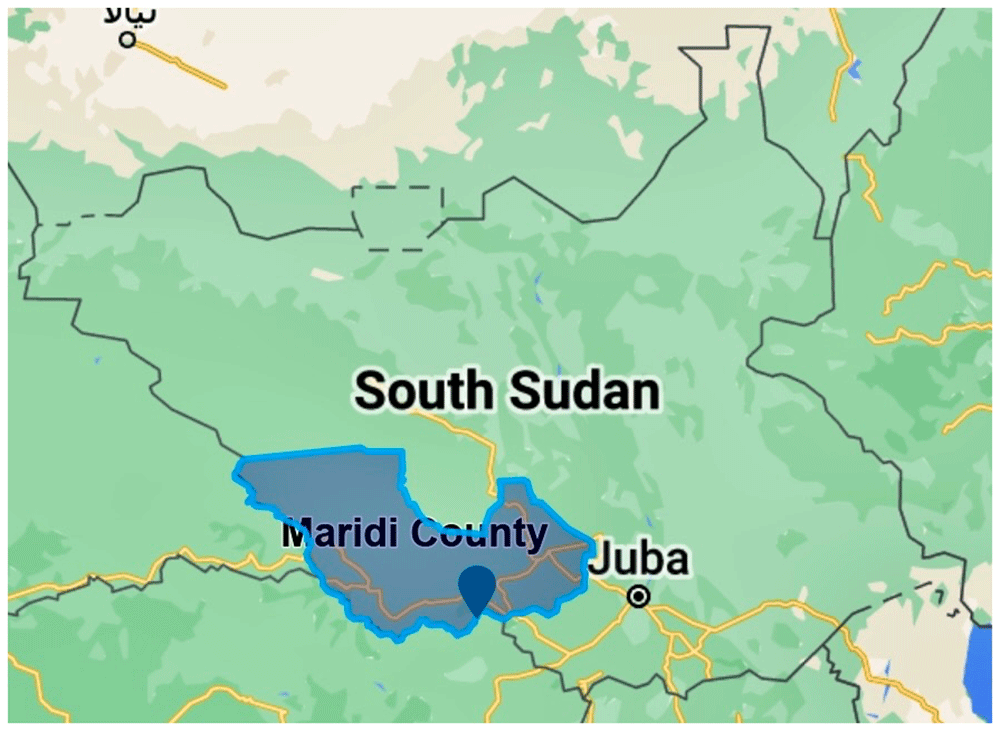
Figure 2. Location of Maridi County in Western-Equatorian State, South Sudan (produced in Scribble Maps).
Maridi County is home to over 115,000 individuals6 and is crossed by the Maridi River, upon which a dam was built in the 1950s. The dam spillway was identified as the sole blackfly breeding site in Maridi4, driving onchocerciasis transmission in the neighbouring villages. This study was conducted between 2019 (baseline) and 2023 (follow-up) in five villages, of which Kazana 1, Kazana 2, and Hai-Matara are situated in the proximity of the dam (high-transmission zone; HTZ) and Hai-Tarawa and Hai-Gabat are located further away from the dam (low-transmission zone; LTZ) (Figure 3).
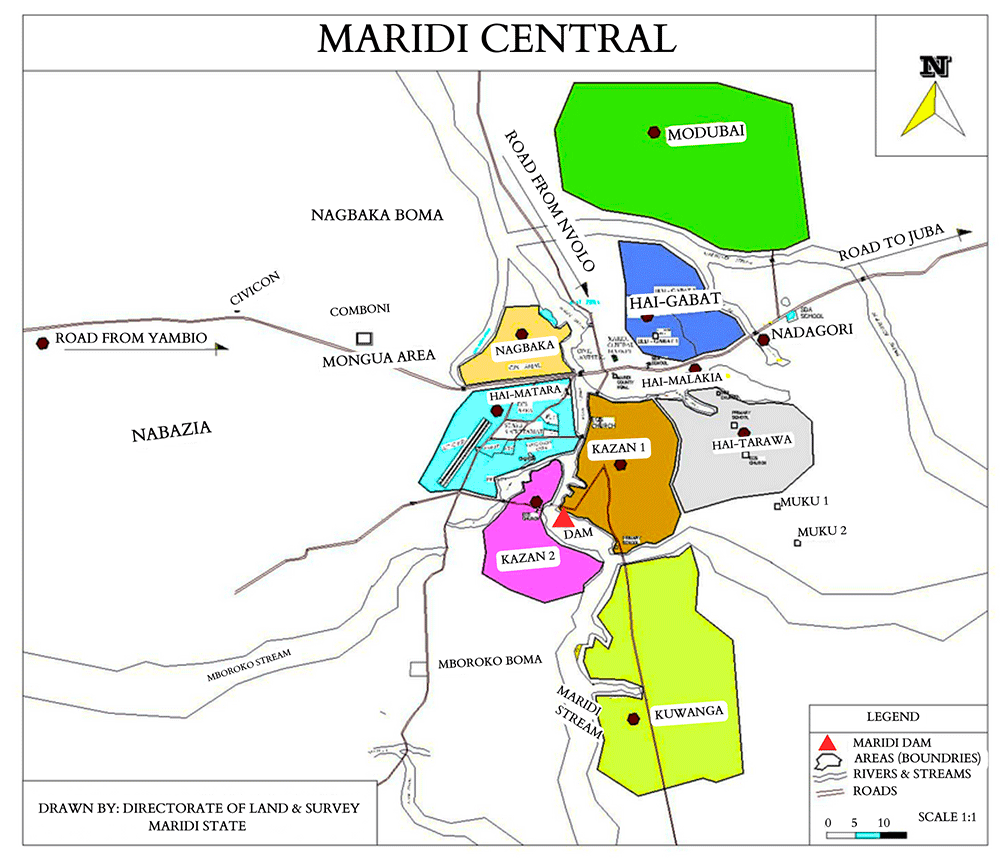
Figure 3. The Maridi central area with the location of high- (Kazana 1 and 2 and Hai-Matara sites) and low-onchocerciasis transmission zones (Hai-Gabat and Hai-Tarawa sites) and the Maridi Dam (adapted from Colebunders et al.7).
Study procedures
A cross-sectional study was conducted before and after strengthening the control interventions against onchocerciasis. The procedures of the baseline survey (2019) have been detailly described previously4. Several weeks before the follow-up survey in 2023, the research team contacted the community leaders to inform them about the study and obtain their consent and collaboration. One day before participant recruitment, community mobilisers notified villagers about the study and of the site(s) chosen in each village (schools, churches, etc.) to test the eligible children (three to nine years old). On the day of the study in each study site, the mobilisers used megaphones, and healthcare workers went from house to house to gather more participants. All children for whom informed consent was provided by a parent/guardian were enrolled in the study (assent was obtained from children aged seven to nine years).
A short questionnaire was administered to the parent/guardian and the child to collect relevant information about the child’s history (age, sex, village of residence, previous ivermectin intake, itching/skin lesions, epilepsy). Thereafter, all the participating children were finger-pricked with a single-use, retractable lancet of 2.00 millimetres (Ergo lance). Whole blood from each finger prick was used for Ov16 rapid diagnostic testing (RDT) (SD Bioline, Inc, Gyeonggi-do, South Korea). The Ov16 RDT test was read after 30 minutes and performed in the field following the manufacturers’ instructions.
Data analysis
Study data was checked daily and uploaded to the REDCap secure online platform. The final datasets were exported from REDCap and cleaned in Excel spreadsheets and then transferred to the R software version 4.2.2 for analysis. Continuous variables were summarised as median with interquartile range (IQR), while categorical variables were expressed as percentages. The findings of the baseline (2019)4 and follow-up (2023) surveys were compared using the Chi-squared test (or Fisher’s exact test when appropriate) and 95% confidence intervals (CIs) were produced using the Wilson score with continuity correction.
Results
Ov16 seroprevalence in Maridi 2023
During the 2023 O. volvulus seroprevalence study in Maridi, 248 children aged three to nine years were recruited. The median age was six years (IQR: 4-8), and 114 (46.0%) were males. Ninety-three (37.5%) of the participating children had some form of dermatitis, as evidenced by itching and/or visible skin lesions. Furthermore, four (1.6%) children were identified as having epilepsy.
The overall Ov16 RDT seroprevalence was 76/248 (30.7%). The seroprevalence was significantly different across villages (p<0.001), with Kazana 1 and Kazana 2 being the most affected and Hai-Gabat and Hai-Tarawa less affected (Figure 4).
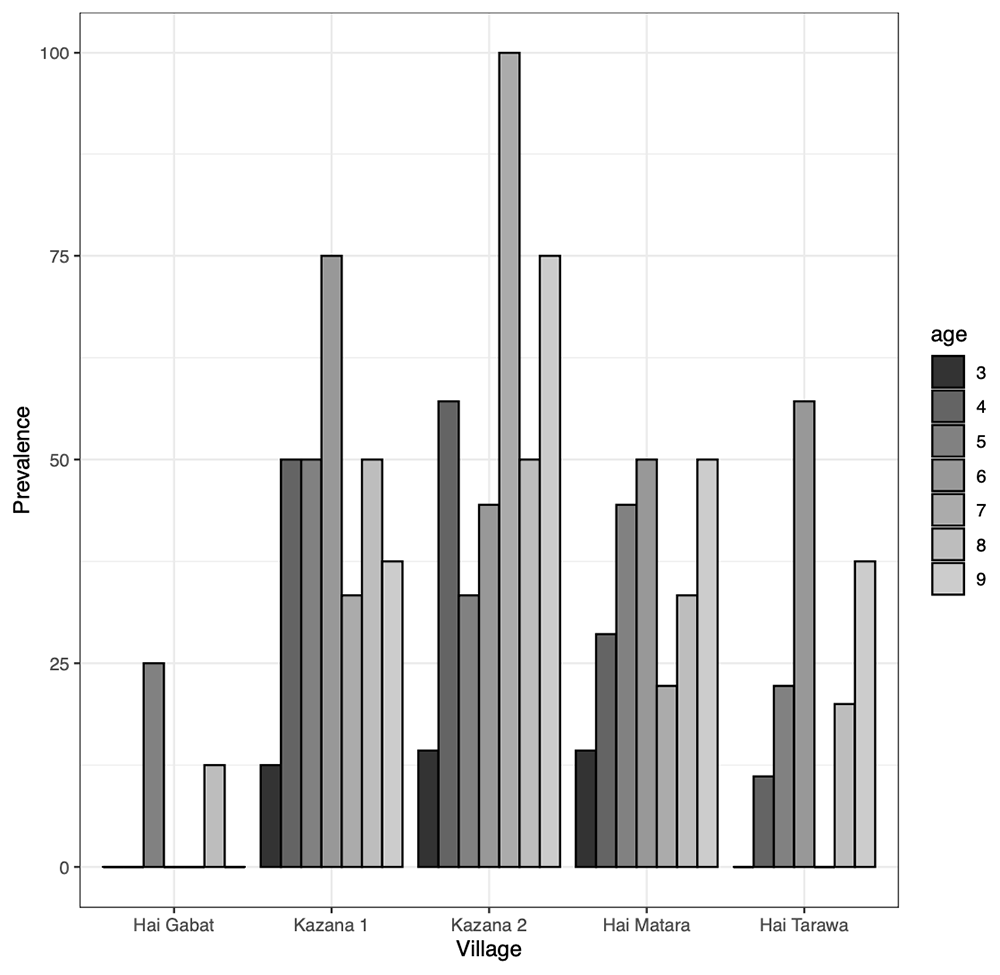
Figure 4. Ov16 rapid diagnostic test seroprevalence in 2023 per study site and age (years old).
The Ov16 RDT seroprevalence was similar for males and females (p=0.98) and did not vary significantly across the younger (30.7% seropositivity among children aged <7 years) and older (30.5% seropositivity among aged ≥7 years) age-groups (p=0.78) (Table 1). However, the 3-year-olds, had lower Ov16 seropositivity: 3/34 (8.8%) versus 73/214 (34.1%) in the older children; p<0.001.
Table 1. Ov16 rapid diagnostic test seroprevalence in 2023 by age group and sex across included villages.
| Ov16 RDT seroprevalence (%, 95%CI) | Comparisons |
|---|
| Village | Hai-Gabat | Kazana 1 | Kazana 2 | Hai-Matara | Hai-Tarawa | Overall | p-value* |
|---|
| Age-groups |
| 3–6 years | 1/29
(3.4, 0.2-19.6) | 14/30
(46.7, 28.8-65.4) | 14/32
(43.8, 26.0-60.6) | 11/31
(35.5, 19.8-54.6) | 7/30
(23.3, 10.6-42.7) | 47/153
(30.7, 23.7-38.8) | 0.98 |
| 7–9 years | 1/21
(4.8, 0.2-25.9) | 8/20
(40.0, 20.0-63.6) | 8/12
(66.7, 38.9-89.6) | 7/21
(33.3, 15.5-57.0) | 4/20
(20.0, 0.7-44.3) | 29/95
(30.5, 21.7-40.9) |
| Sex |
| Male | 1/28
(3.6, 0.2-20.2) | 8/16
(50.0, 28.0-72.0) | 11/20
(55.0, 32.0-76.2) | 7/18
(38.9, 18.3-64.0) | 6/31
(19.4, 8.1-38.1) | 33/113
(29.2, 21.2-38.6) | 0.78 |
| Female | 1/22
(4.5, 0.2-24.9) | 14/34
(42.2, 25.2-59.2) | 12/26
(46.6, 27.1-66.3) | 11/34
(32.4, 18.0-50.6) | 5/19
(26.3, 10.1-51.4) | 43/135
(31.9, 24.3-40.5) |
| Overall | 76/248
(30.6, 25.1-36.9) |
Children with dermatitis had a higher Ov16 RDT seroprevalence (40/92, 43.5%) compared to their peers without dermatitis (35/155, 22.6%); p<
0.001. Of the four children with epilepsy, none tested positive for Ov16 antibodies.
Ov16 seroprevalence in Maridi over time
Comparing baseline and follow-up Ov16 RDT results, the overall Ov16 seroprevalence increased non-significantly from 24.3% in 2019 to 30.6% in 2023 (p=0.22) (Figure 5). The seroprevalence among the three-year-olds, born after implementation of more robust onchocerciasis elimination measures like vector control and bi-annual CDTi, non-significantly decreased from 12.5% in 2019 to 8.8% in 2023 (p=0.68). Conversely, the Ov16 seropositivity rose non-significantly from 26.7% in 2019 to 34.1% in 2023 among children aged four years and above (p=0.16). Transmission zone-specific Ov16 seroprevalence did not significantly change across surveys (HTZ: p= 0.70; LTZ: p= 0.18; Table 2).
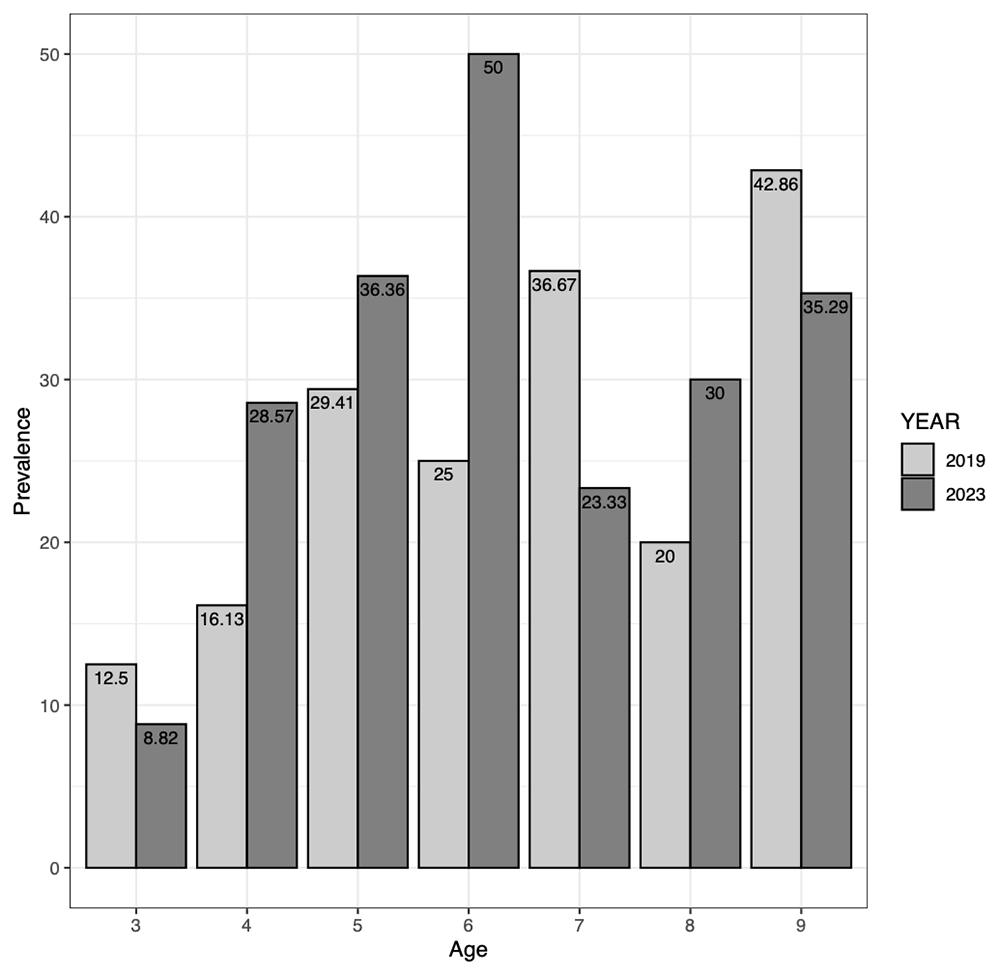
Figure 5. Ov16 rapid diagnostic test seroprevalence (%) by age and year surveyed (2019 and 2023).
Table 2. Ov16 rapid diagnostic test seroprevalence among three- to nine-year-olds per survey (2019/2023) and village.
| 2019 seroprevalence (%, 95%CI) | 2023 seroprevalence (%, 95%CI) | p-value* |
|---|
| Village |
| Hai-Gabat | 0/24 (0.0, 0.0-17.2) | 2/48 (4.2, 0.7-14.9) | N.A. |
| Kazana 1 | 14/40 (35.0, 21.1-51.7) | 22/50 (44.0, 30.3-58.7) | 0.52 |
| Kazana 2 | 12/24 (50.0, 31.4-68.6) | 23/46 (50.0, 36.1-63.9) | 1.00 |
| Hai-Matara | 4/27 (14.8, 4.9-34.6) | 18/52 (34.6, 22.3-49.2) | N.A. |
| Hai-Tarawa | 5/29 (17.2, 6.5-36.5) | 11/50 (22.0, 12.0-36.3) | 0.83 |
| Transmission zones |
| Low-transmission zone | 5/53 (9.4, 3.5-21.4) | 13/100 (13.0, 7.4-21.6) | 0.70 |
| High-transmission zone | 30/91 (33.0, 23.7-43.7) | 63/148 (42.6, 34.6-51.0) | 0.18 |
| Overall | 35/144 (24.3, 17.7-32.3) | 76/248 (30.7, 25.1-36.9) | 0.22 |
Discussion
In 2023, an Ov16 seroprevalence of 30.7% was found among children aged three to nine years in Maridi, representing a non-significant increase from the 24.3% seroprevalence documented in 20194 (p=0.98). These results suggest that the elimination measures did not significantly impact the seroprevalence of the study population and that there is still ongoing transmission of O. volvulus. As the elimination measures were only introduced three years ago, children between the ages of four and nine years in the 2023 cohort had already been highly exposed to onchocerciasis before strengthening the control interventions. Moreover, the non-significant increase in the seroprevalence among children aged four to nine years (26.7% in 2019 to 34.1% in 2023, p=0.16) may indicate an intensification of O. volvulus transmission in Maridi before the implementation of Slash and Clear and biannual CDTi and the lack of CDTi in 2020 due to the COVID-19 pandemic.
The fact that the seroprevalence among the three-year-olds did not decrease significantly may be related to the small sample size, short follow-up duration since the strengthening of the control interventions and the lack of CDTi in 2021. Indeed, mathematical modelling has suggested that a one-year CDTi interruption may significantly impact onchocerciasis elimination prospects in settings such as Maridi, with short CDTi histories and high onchocerciasis endemicity8,9. The one-year CDTi interruption in 2020 and the consistently low CDTi coverage rates achieved in Maridi (40.8% in 20177 and 56.6% in 202110) explains why some three-year-old children became infected with O. volvulus and that there was an increasing trend in seropositivity among the older children. Achieving a CDTi coverage of at least 80% of the total population is strongly recommended for the successful elimination of onchocerciasis transmission, particularly in areas with a high prevalence of the disease11. On the other hand, the “Slash and Clear” intervention did almost but not completely eradicate blackflies; hence, some residual onchocerciasis transmission may have continued post-intervention10.
The high Ov16 seroprevalence among young children in Maridi reveals that the onchocerciasis elimination measures must be further strengthened to protect children from developing onchocerciasis-associated morbidities. Over one-third (37.5%) of the children had some form of dermatitis, as evidenced by itching and/or visible skin lesions. A significantly higher proportion of children with dermatitis tested Ov16 RDT positive (43.5%) compared to their peers without dermatitis (22.6%, p<0.001), suggesting the dermatitis was likely caused by an active O. volvulus infection in a large proportion of children.
This study demonstrates the feasibility of using rapid diagnostic tests for evaluating onchocerciasis transmission in highly endemic settings. Until recently, field Ov16 RDTs were overlooked in monitoring onchocerciasis transmission in endemic foci since the gold standard technique recommended by the World Health Organization (WHO) was Ov16 enzyme-linked immunosorbent assay (ELISA). However, in practice, there are logistical challenges to performing Ov16 ELISA (need for a cold chain, specialised equipment, and capacity), particularly in remote sites like Maridi. Meanwhile, studies in Cameroon12 and the Democratic Republic of Congo13 have found that Ov16 RDT done in the field was helpful in investigating onchocerciasis transmission patterns. Therefore, it is worth considering the widespread of RDTs as a point-of-care approach for monitoring onchocerciasis in resource-limited sites.
Our study had some limitations. The sample size of our study sample was small, particularly among the 3-year-olds. A sufficiently large sample size of 3-year-old children needs to be Ov16 RDT tested before and after interventions to evaluate the short-term effect of strengthening an onchocerciasis elimination programme. Moreover, in the absence of skin snips for microfilariae quantification and blackfly infection rates, it is difficult to obtain precise estimates of the intensity of O. volvulus transmission in Maridi. Further research may be required to better understand the Ov16 antibodies dynamics during and after O. volvulus infection. Notwithstanding, our findings confirm the importance of the O. volvulus health problem in Maridi.
In conclusion, Maridi remains a hotspot for O. volvulus transmission even after the implementation of elimination measures. These measures should be continued and strengthened even further, including increasing the CDTi coverage, to protect children to develop OAE and to move towards the elimination goals of WHO in 2030.
Data availability
EUDAT. Rapid diagnostic testing for onchocerciasis in Maridi (South Sudan) before and after improving elimination strategies. DOI: 10.23728/b2share.e98101581be64e6188836d73a19d024314.
This project contains the following data:
- Baseline and follow-up serosurveys were conducted in Maridi in 2019 (prior to strengthening onchocerciasis elimination efforts) and 2023, respectively. During both surveys, children aged three to nine years were recruited from five study sites situated at different distances from the Maridi Dam. Ov16 antibodies were detected via rapid diagnostic tests (RDTs) using whole blood obtained by finger-pricking the participants. Baseline and follow-up Ov16 prevalence rates were calculated and compared.
Data are available under the terms of the Creative Commons Zero "No rights reserved" data waiver (CC0 1.0 Public domain dedication).
Author contributions
Conceptualisation by AH, SRJ and RC; data curation by AH and SRJ; formal analysis by AH and JNSF; funding acquisition by RC; investigation by SRJ and AH; methodology by SRJ, RC and AH; project administration by SRJ; resources by RC, JR; software by AH; supervision by RC and JNSF; validation by RC; visualisation by AH; writing – original draft by AH, JNSF, L-JA and RC; and writing – review & editing by AH, SRJ, L-JA, RC, and JNSF.
Acknowledgements
We are grateful to the clinical officers, nurses and research assistants who conducted the surveys; to the Maridi Health Sciences Institute and Amref Health Africa for using its facilities, equipment, and vehicles; to the Western Equatoria State and the Maridi County governments for their support; and to the population of the Maridi settlements for their cooperation and participation.
Faculty Opinions recommendedReferences
- 1.
Brattig NW, Cheke RA, Garms R:
Onchocerciasis (river blindness) – more than a century of research and control.
Acta Trop.
2021; 218: 105677. PubMed Abstract
| Publisher Full Text
- 2.
Colebunders R, Njamnshi AK, Menon S, et al.:
Onchocerca volvulus and epilepsy: A comprehensive review using the Bradford Hill criteria for causation.
PLoS Negl Trop Dis.
2021; 15(1): e0008965. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 3.
Boussinesq M, Fobi G, Kuesel AC:
Alternative treatment strategies to accelerate the elimination of onchocerciasis.
Int Health.
2018; 10(suppl_1): i40–i48. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 4.
Lakwo TL, Raimon S, Tionga M, et al.:
The Role of the Maridi Dam in Causing an Onchocerciasis-Associated Epilepsy Epidemic in Maridi, South Sudan: An Epidemiological, Sociological, and Entomological Study.
Pathogens.
2020; 9(4): 315. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 5.
Raimon S, Lakwo TL, Sebit WJ, et al.:
"Slash and Clear", a Community-Based Vector Control Method to Reduce Onchocerciasis Transmission by Simulium sirbanum in Maridi, South Sudan: A Prospective Study.
Pathogens.
2021; 10(10): 1329. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 6.
South Sudan - County Population Estimates - 2015-2020. Humanitarian Data Exchange. accessed 11 Mar 2023.
Reference Source
- 7.
Colebunders R, Carter JY, Olore PC, et al.:
High prevalence of onchocerciasis-associated epilepsy in villages in Maridi County, Republic of South Sudan: A community-based survey.
Seizure.
2018; 63: 93–101. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 8.
Nana-Djeunga HC, Djune-Yemeli L, Domche A, et al.:
High infection rates for onchocerciasis and soil-transmitted helminthiasis in children under five not receiving preventive chemotherapy: a bottleneck to elimination.
Infect Dis Poverty.
2022; 11(1): 47. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 9.
Hamley JID, Blok DJ, Walker M, et al.:
What does the COVID-19 pandemic mean for the next decade of onchocerciasis control and elimination?
Trans R Soc Trop Med Hyg.
2021; 115(3): 269–80. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 10.
Jada SR, Amaral LJ, Lakwo T, et al.:
Effect of Onchocerciasis Elimination Measures on the Incidence of Epilepsy in Maridi, South Sudan: A Three-Year Prospective Study.
The Lancet.
Preprint. Publisher Full Text
- 11.
Conceptual and operational framework of onchocerciasis elimination with ivermectin treatment.
African Programme for Onchocerciasis Control. World Health Organization & African Programme for Onchocerciasis Control. 2010; accessed 25 May 2023. Reference Source
- 12.
Ekanya R, Beng AA, Anim MA, et al.:
Concordance between Ov16 Rapid Diagnostic Test(RDT) and Ov16 Enzyme-Linked Immunosorbent Assay (ELISA) for the Diagnosis of Onchocerciasis in Areas of Contrasting Endemicity in Cameroon.
Parasite Epidemiol Control.
2023; 21: e00290. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 13.
Lenaerts E, Mandro M, Mukendi D, et al.:
High prevalence of epilepsy in onchocerciasis endemic health areas in Democratic Republic of the Congo.
Infect Dis Poverty.
2018; 7(1): 68. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 14.
Hadermann A, Jada SR, Amaral LJ, et al.:
Rapid diagnostic testing for onchocerciasis in Maridi (South Sudan) before and after improving elimination strategies. [Data set] 2023; https://b2share.eudat.eu. http://www.doi.org/10.23728/B2SHARE.E98101581BE64E6188836D73A19D0243










