Introduction
Leading in fourth place globally, among all the cancers that affect women, Cervical Cancer records approximately 660,000 new cases and nearly 360,000 new deaths worldwide1. It has been proven that approximately 90% of these cases occur in developing countries2, with Africa reporting close to 125,000 new cases annually, and is ranked second in causing cancer-related deaths, mostly among women age–14–44 years3. As of 2022, Cervical Cancer comes second after breast cancer as the commonly diagnosed type of cancer among women in Kenya, with about 6,000 new cases annually and is the major cause of cancer-related deaths among women recording 3,600 deaths., accounting for close to 12% of all cancer-related deaths among women in Kenya4.
Literature shows that the stage of cancer at the time of diagnosis is a vital prognostic factor that influences cancer treatment outcomes5. Delays in cancer diagnosis increase the risk of poor outcomes6. Early diagnosis (Stages I and II) is associated with a 98% 5-year survival rate, while delayed diagnosis (Stages III and IV) is associated with lower rates (17% 5-year survival rate)6. Globally, the prevalence of delayed diagnosis of Cervical Cancer is more than 50%, with this proportion rising to approximately 80% in developing countries6,7. Despite strategies that have been put in place to enhance early detection, such as creating awareness and screening, Cervical Cancer remains a threat to many sexually active women in Africa8.
Early diagnosis is attributed to functional health systems, such as timely patient referrals from less equipped facilities to better equipped hospitals, where they can access effective services for diagnosis. Inadequate Health systems can cause delays in primary health care, resulting in late-stage cancer7. Few studies in Kenya have focused on health facility level factors that contribute to delayed diagnosis of Cervical Cancer, causing high mortality rates due to poor outcomes. This study assessed the association between delayed diagnosis and patients’ experiences at the health facility level at Kenyatta National Hospital (KNH).
Methods
This was a hospital-sited, analytical, cross-sectional mixed method study (with both quantitative and qualitative techniques used) conducted between September to November 2023, at the KNH, a National Referral and Teaching Hospital, that offers both preventative and curative services for cancer patients referred from all over Kenya. Systematic sampling was used to select 139 Cervical Cancer inpatient and outpatient patients, diagnosed and receiving treatment at the KNH, aged above 18 years, and diagnosed within the last year since the time of data collection to minimize recall bias. Patients whose medical records did not have clear staging information, those diagnosed with other cancer types, those with recurrent Cervical Cancer, those in palliative care, those with psychotic health issues, and those who were unwilling to participate in the study were excluded. The participants were interviewed using a semi-structured questionnaire, with questions regarding their hospital and referral experiences, such as type of medical facility they visited first, number of hospital visits they made before diagnosis, if they were referred to KNH, Number of referral times, referral challenges they faced, and period taken to get diagnosis appointments and results. This allowed for quantitative data collection. A Key Informant Guide was used to conduct Key Informant Interviews (KIIs), to enable in-depth qualitative data collection from 8 Key Informants, such as; Medical, Surgical and Radio Oncologists, departmental nurses and social workers, in audio recorded sessions. The qualitative data was collected to support the quantitative findings in triangulation. The key outcome of delayed diagnosis was stage at diagnosis, categorized as either early (stages IA to IIB) or delayed (IIIA and IVC) using the International Federation of Gynecology Obstetrics (FIGO) staging for cervical cancer that is based on the cancer’s size, location and spread . The stage at diagnosis was retrieved as the stage of malignancy recorded by the doctor in the patients’ files, using abstraction forms. Statistical analyses were performed using Stata version 14.2 (https://www.stata.com/). The association between delayed diagnosis and health facility-level factors was determined by logistic regression test at 95% Confidence Interval and Odds Ratios and P-Values were reported. Audio recordings for qualitative data were transcribed verbatim, transcripts were verified, and then deductive thematic analysis was conducted using NVIVO 14 (https://lumivero.com/resources/free-trial/nvivo/).
Results
Sociodemographic characteristics
The mean age was 51 years (interquartile Range, 29–89. A majority of the 49(35.25%) participants were aged between 40–49 years. More than half 88(63.31%) were married, and 95(86.35%) were educated up to the primary level. Less than half of the 54 participants (38.85%) reported being employed (Table 1).
Table 1. Summary patients’ socio-demographic characteristics.
| Variable | Frequency(n=139) | Percent (%) |
|---|
| Age in years | | |
| <40 | 22 | 15.83 |
| 40-49 | 49 | 35.25 |
| 50-59 | 42 | 30.22 |
| 60-69 | 18 | 12.95 |
| 70 and above | 8 | 5.76 |
| Ethnicity | | |
| African | 139 | 100 |
| Religion | | |
| Christian | 139 | 100 |
| Marital Status | | |
| Married | 88 | 63.31 |
| Divorced/Widowed | 28 | 20.14 |
| Single | 23 | 16.55 |
| Residence | | |
| Urban | 59 | 42.45 |
| Semi-urban | 24 | 17.27 |
| Rural | 56 | 40.29 |
| County of Residence | | |
| Nairobi | 54 | 38.85 |
| Another County | 85 | 61.15 |
| Education | | |
| Primary and below | 95 | 68.35 |
| High school | 34 | 24.46 |
| Tertiary | 10 | 7.19 |
| Employment Status | | |
| Employed | 54 | 38.85 |
| Not employed | 85 | 61.15 |
| Monthly Income | | |
| >25,000 | 15 | 27.78 |
| 10,000-25,000 | 17 | 31.48 |
| <10,000 | 22 | 40.74 |
Prevalence of delayed diagnosis
The Prevalence of delayed diagnosis was 61.87% as 86 of the 139 participants were diagnosed at stages IIIA to IVC See Figure 1.
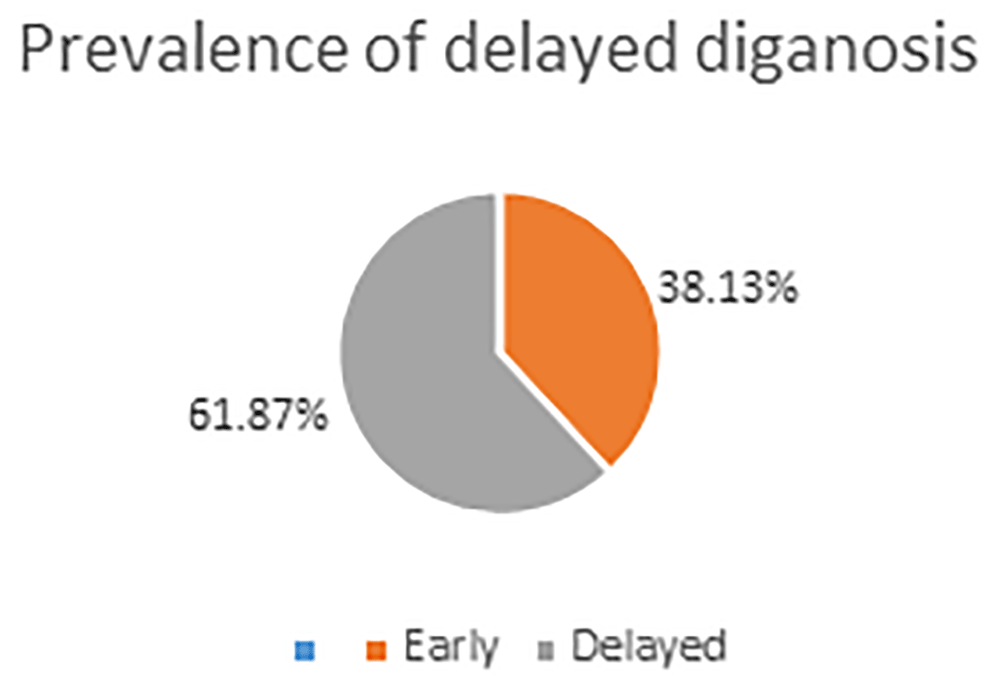
Figure 1. Prevalence of delayed diagnosis.
Figure 1 illustrates the prevalence of delayed diagnosis (67.81%) among cervical cancer patients at KNH. The pie chart is divided into two segments, each representing the percentage (size) of patients either diagnosed early or late. Data was collected from 139 participants, 86 who were found to be diagnosed late, while 53 were diagnosed early, as defined by the study.
Qualitatively, seven of the eight key informants confirmed that most KNH patients were diagnosed at advanced stages III to IV.
Health facility-level factors
Distribution of participants across of health facility factors
Over half of the participants 91(65.67%) first sought medical care from public health facilities, followed by 40(28.78%) who went to private health facilities, and 8(5.76%) who sought help from local chemists or traditionalists. Less than half 49(35.25%) of the participants visited the hospital five times or more before being diagnosed with cervical cancer. A total of 125(89.93%) participants were referred from lower-level facilities to the KNH, with 58(46.4%) reporting that they were referred twice or more. More than half of those who were referred to 72(57.6%) reported facing referral challenges that hindered access to appropriate and proper medical care, thus delaying their diagnosis. Most patients who faced challenges reported a lack of finances (40) as the major challenge they faced, followed by misdiagnosis (15) and prolonged appointments (14) See Figure 2. Those who reported misdiagnosis were diagnosed with vaginal infections, STIs, postmenopausal bleeding, hormonal contraceptive side effects, and fibroids, among other health issues.
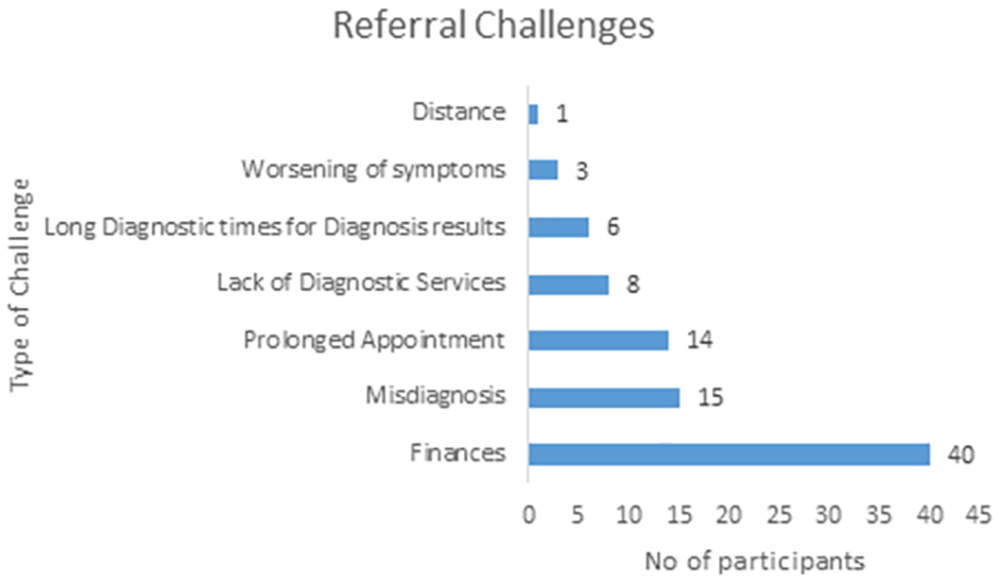
Figure 2. Distribution of Referral Challenges.
Figure 2 is a horizontal bar chart showing the different hospital referral challenges that the cervical cancer patients at KNH who reported to have been referred from another hospital to KNH for diagnosis, faced during the referral process. It also shows the distribution of patients across the challenges.
Most participants 64(46.04%) reported having received their diagnostic results in less than two weeks, while 32(23.02%) reported having received results in over a month (Table 2).
Table 2. Distribution of participants across of health facility factors.
| Variable | Frequency(n=139) | Percentage (%) |
|---|
| First Medical Care | | |
| Private | 40 | 28.78 |
| Public | 91 | 65.47 |
| Other | 8 | 5.76 |
| Hospital visits | | |
| Once | 29 | 20.86 |
| Twice | 22 | 15.83 |
| 3-4 times | 39 | 28.06 |
| 5 times and above | 49 | 35.25 |
| Referred | | |
| Yes | 125 | 89.93 |
| No | 14 | 10.07 |
| Referral times | | |
| Once | 67 | 53.6 |
| Twice and above | 58 | 46.4 |
| Referral Challenges | | |
| Yes | 72 | 57.6 |
| No | 53 | 42.4 |
| Diagnosis Appointment | | |
| <2 weeks | 119 | 85.61 |
| 2 weeks - 1 month | 12 | 8.63 |
| > 1 month | 8 | 5.76 |
| Diagnostic Results | | |
| <2 weeks | 64 | 46.04 |
| 2 weeks - 1 month | 43 | 30.94 |
| > 1 month | 32 | 23.02 |
Association between health facility level-factors by delayed Cervical Cancer diagnosis
A structured approach was adopted for the analysis. Bivariate analysis was performed to examine the relationship between each independent variable individually and the dependent variable (delayed diagnosis) using binary logistic regression, and to identify potential predictors of the outcome at a 95% confidence level (p < 0.05). Variables found to be statistically significant (p <0.05) were selected for the multivariate logistic regression test model to show the independent variables that were independently associated with delayed diagnosis after controlling for confounders.
Table 3 summaries the relationship between delayed diagnosis and health facility level factors assed in bivariate analysis. Across the seven health facility factors, four were found to be potential risk factors for delayed diagnosis in the bivariate analysis.
Table 3. Association between health facility level-factors by delayed Cervical Cancer diagnosis.
| Variable | | Early (%)
n=53 | Delayed
(%) n=86 | Crude Odds Ratio (95%
Confidence Interval) | P-value |
|---|
| First Medical care | | | | |
| Private | 15(37.50) | 25(62.50) | Ref | |
| Public | 36(39.56) | 55(60.44) | 0.917(0.426-1.971) | 0.824 |
| Other | 2(25.00) | 6(75.00) | 1.800(0.321-10.088) | 0.504 |
| Hospital visits | | | | |
| Once | 12(41.38) | 17(58.62) | Ref | |
| Twice | 10(45.45) | 12(54.55) | 0.847(0.277-2.591 | 0.771 |
| 3-4 times | 14(35.90) | 25(64.10) | 1.261(0.470-3.382 | 0.646 |
| 5times and above | 17(34.69) | 32(65.31) | 1.329(0.517-3.417) | 0.555 |
| Referred | | | | | |
| Yes | 46(36.80) | 79(63.20) | Ref | |
| No | 7(50.00) | 7(50.00) | 0.582(0.192-1.765) | 0.339 |
| Referral times | | | | |
| Once | 35(52.24) | 32(47.76) | Ref | |
| Two and above | 11(18.97) | 47(81.03) | 4.673(2.073-10.535) | 0.000* |
| Referral Challenges | | | | |
| Yes | 21(29.17) | 51(70.83) | 2.168(1.034-4.550) | 0.041* |
| No | 25(47.17) | 28(52.53) | Ref | |
| Diagnosis Appointment | | | |
| <2 weeks | 48(40.34) | 71(59.66) | Ref | |
| 2 weeks- 1 Month | 1(8.33) | 11(91.67) | 7.437(0.929-59.504 | 0.059* |
| I Month and above | 4(50.00) | 4(50.00) | 0.676(0.161-2.835) | 0.592 |
| Diagnostic Results | | | | |
| <2 weeks | 31(48.44) | 33(51.56) | Ref | |
| 2 weeks- 1 Month | 16(37.21) | 27(62.79) | 1.585(0.720-3.490) | 0.252 |
| I month and above | 6(18.75) | 26(81.25) | 4.071(1.477-11.222) | 0.007* |
Although referral was not found to be statistically significantly associated with delayed diagnosis of cervical cancer in this study, among the 125(89.93%) participants who were reported to have been referred from lower-level facilities to the referral hospital KNH, 79(63.20%) were found to have been diagnosed late. Patients who had been referred two times and more were potentially found to be 4.7 times more likely to have delayed diagnosis compared to those who were only referred once (Odds Ratio (OR)=4.673,95%Confidence Interval(CI):2.073-10.535, p-value=0.000). Patients who reported facing referral challenges were potentially found to be 2.2 times more likely to be diagnosed at late stages than those who reported not to have faced any referral challenges (OR=2.168,95%CI:1.034-4.550, p-value=0.041). While the majority of the patients reported that their diagnosis took less than two weeks, 36(23%) of the participants reported that their diagnosis took longer than one month, with 26(81.25%) of them being diagnosed at advanced stages. Patients who reported that their diagnosis appointment took 2 weeks to 1 month were potentially found to be 7.4 times more likely to be diagnosed at late stages than those who reported that their diagnosis appointment took less than 2 weeks (OR=7.437,95%CI:0.929-59.504, p-value=0.059), while patients whose diagnostic results took 1 month and above were potentially found to be 4.1 times more likely to be diagnosed at late stages than those whose results took less than 1 month (OR=4.071,95%CI:1.477-11.222,p-value=0.007). (Table 3)
A multicollinearity check was performed on the significant health facility-level factors that were found to be potential predictors from the bivariate analysis, and none had any collinearity (Table 4).
Table 4. Multi-collinearity check among health facility-level factors.
| Referral
times | Referral
challenges | Diagnosis
appointment | Diagnosis
results |
|---|
| Referral times | 1 | | | |
| Referral challenges | -0.0517 | 1 | | |
| Diagnosis appointment | 0.0431 | -0.1738 | 1 | |
| Diagnosis results | 0.1098 | -0.0794 | 0.1791 | 1 |
A multivariate logistic regression test model was run for the four health facility-level factors, and two remained independently and statistically significantly associated with delayed diagnosis: the number of referrals and the time taken to obtain diagnostic results. Patients who were referred twice or more were 4.5 times more likely to be diagnosed at advanced stages of cervical cancer (Adjusted Odds Ratio (AOR)=4.532,95%CI:1.908-10.767, p-value=0.001) when compared to those who were referred only once, while those reported to have received their diagnostic results in a month and more were 4 times more likely to be diagnosed at late stages of cervical cancer than those who received their results earlier in less than two weeks (AOR=3.933,95%CI:1.187-13.032,p-value=0.025)
The Pseudo R squared was 0.185, indicating that the logistic regression model explained 19% of the variability in delayed diagnosis, as captured by the proportion of variability explained by the model relative to the maximum variability that could be explained. The probability associated with the chi-square statistic (Prob > chi2), was 0.0000 indicating a very high statistical significance, and that the predictors in the model improved the fit. This result provides evidence to support the inclusion of predictors in the model to explain the outcome variable See Table 5.
Table 5. A multivariate logistic regression test model for delayed diagnosis against health facility-level factors.
| Variable | Adjusted
Odds Ratio | Std
Error | Z statistic | 95% Confidence
Interval | P-value |
|---|
| Referral times | | | | | |
| Once | Ref | | | | |
| Two and above | 4.532 | 2.000 | 3.42 | 1.908-10.767 | 0.001* |
| Referral Challenges | | | | | |
| Yes | 2.222 | 0.954 | 1.86 | 0.958-5.153 | 0.063 |
| No | Ref | | | | |
| Diagnosis Appointment | | | | | |
| <2 weeks | Ref | | | | |
| 2 weeks-1 Month | 6.013 | 6.890 | 1.57 | 0.636-56.811 | 0.117 |
| 1 month and above | 0.233 | 0.221 | -1.54 | 0.037-1.491 | 0.124 |
| Diagnostic Results | | | | | |
| <2 weeks | Ref | | | | |
| 2 weeks-1 Month | 1.158 | 0.569 | 0.30 | 0.442-3.034 | 0.765 |
| 1 Month and above | 3.933 | 2.404 | 2.24 | 1.187-13.032 | 0.025 |
Qualitative findings
The qualitative findings from the KIIs aligned with the confirmed associations between referral times, referral challenges, prolonged appointments, and delayed results with delayed diagnosis. It was reported that due to the referral challenges that patients face from local facilities to KNH, such as misdiagnosis and cost of diagnosis, patients often reach the facility when the disease has advanced to late stages and incurs more costs See Figure 3.
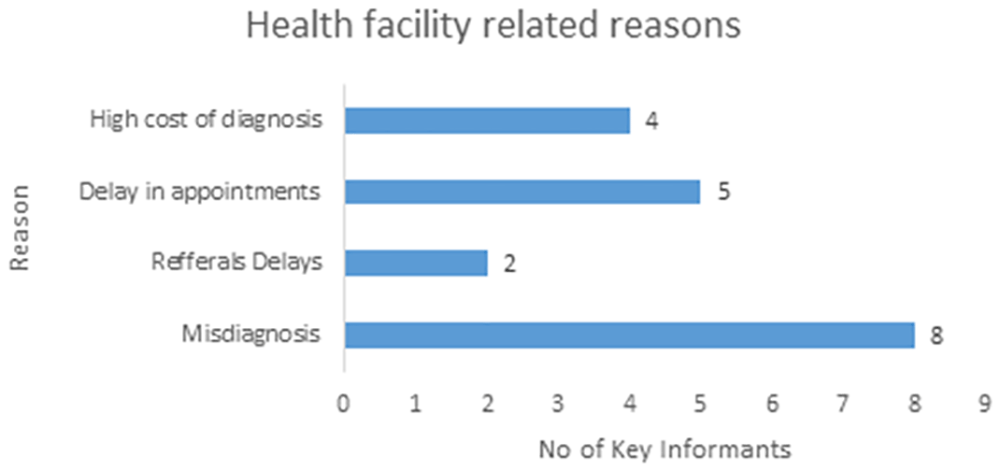
Figure 3. Health facility reason contributing to delayed diagnosis; KIIs views.
Figure three is a representation of the Key Informant views on reasons that may facilitate delayed diagnosis or hinder cervical cancer patients from accessing early care for timely diagnosis. This views were triangulated to support the qualitative findings and provide in-depth understanding of the study findings.
“Like, if someone has irregular bleeding for long periods, and they visit a smaller hospital, they are misdiagnosed with things like postmenopausal bleeding, ...this can make it to take longer for them to be correctly diagnosed.” (KII_6RO)
“Each referral means an extra cost for the patient. For example, KNH asks for new scans from a referred patient because most of the time the patient comes in delayed...so they ask for another scan to get a more current state of the disease.” (KII_8MO)
“...there is poor diagnosis from peripheral facilities due to lack of specialized personnel. A clinician should have a high index of diagnosis” (KII_7MO)
Appointment dates for diagnosis also take too long because of congestion owing to the high number of patients.
“Do you know if you came here today for diagnosis you will be booked to have scanning or MRI in two months, that is the least time...they say patients are many...biopsy take even longer than 2 months...Only those who can afford scanning in private facilities do it quicker” (KII_5N)
Discussion
Prevalence of delayed diagnosis
The study found that most participants were diagnosed at the late stages of Cervical Cancer. The prevalence of delayed diagnosis found in this study (61.87%) was slightly lower than that of a cross-sectional study conducted in Uganda (66%) and close to that of a population study conducted in Ethiopia (60.4%)9,10.
Health facility-level factors
In this study, 90% of participants sought medical help from other facilities before being referred to the KNH. The lack of decentralized diagnostic facilities in Kenya is one of the major barriers to accessing cancer testing, especially in local facilities11, leading to patients being referred to better-equipped facilities to access diagnostic services. While assessing referral dynamics, this study found that patients referred twice or more were reported to face referral challenges and were found to be more likely to have delayed Cervical Cancer diagnosis compared to those who were only referred once with no or fewer referral challenges. Patients were reported to have experienced misdiagnoses of other diseases, such as fibroids, postmenopausal bleeding, and infections. Medical staff noted that several medical personnel from local facilities were not well trained and lacked a high index in suspecting cancer cases; thus, there were a high number of misdiagnosed cases. These findings were in agreement with another study, in which almost half of the participants were referred more than once, and 35% of them blamed medical personnel at local facilities for having misdiagnosed them with other diseases and lack of diagnostic equipment as major referral challenges7. This could be explained by challenges presented by poor referral systems, such as lack of finances, misdiagnosis, lack of specialized personnel, and equipment, which may lead to delays in primary health care7. The availability and accessibility of effective cancer diagnostic equipment are important hospital factors that improve early diagnosis in cancer patients7. Inadequate access to screening and diagnostic services and trained medical personnel, especially in rural settings, forces patients to travel long distances to seek better primary healthcare7,11. Qualitatively, patients had to incur extra financial costs at all referral stages as they were required to pay for consultations, tests, and treatment. Referrals have also led to inconsistencies in medical information due to the misplacement of medical records. This would further cause misdiagnosis and financial burden on patients. Qualitative findings from a previous study reported that inadequate knowledge of Cervical Cancer and patient information provided by healthcare providers are factors that may lead to delayed diagnosis12.
This study also found that longer waiting periods for diagnosis appointments and results lead to delayed diagnosis. These findings are consistent with those of a study that reported that delays in diagnosis hinder primary healthcare, as medical care decisions are dependent on them7. Centralization of diagnostic and treatment equipment in major government hospitals causes congestion in patients due to higher patient to medical personnel ratios and few equipment for diagnosis11. Needy patients are required to travel long distances to seek diagnostic services11. Qualitative findings revealed that due to the high number of cancer patients at KNH, patients take longer to get diagnosis appointments and close to two months or more to obtain scanning or biopsy results. During this waiting period, the disease progresses further with the worsening of symptoms, especially in late-stage patients. These delays could implicate more treatment financial burden on late patients. Delays in diagnosis also hinder primary healthcare, as medical care decisions are dependent on them7. This study found that patients who are able to afford private facilities are able to quickly track this process and receive early diagnosis and treatment because private facilities experience less congestion as only patients who can afford their services visit them.
Conclusion
The study identified gaps in the organization of health referral systems such as referral times, challenges, and systemic delays in appointments, and the results were health facility-related factors that were associated with delayed cervical cancer diagnosis. With these gaps, poor health systems are a major hindrance to access and availability of quality medical care, leading to delayed diagnosis.
Measures such as decentralization and increased HPV screening and cancer diagnosis resources, including trained medical officers, are recommended to lessen the burden of referral challenges and diagnosis delays while targeting women from all socio-demographic settings to improve timely diagnosis. Further studies should assess why misdiagnosis is a major challenge in cervical cancer diagnosis.
Study limitation
The study was limited by recall issues from participants who may not have clearly remembered the date and stage of their diagnosis. Recall bias was minimized by including only participants diagnosed within a year before data collection. The study also adopted abstraction forms to obtain clear information on the date and stage of diagnosis from patients’ medical files, thus minimizing recall bias.
Ethical approval and consent
Ethical clearance and approval were obtained from the JKUAT and KNH-University of Nairobi (UON) Ethical Review Committees (ERCs) under approval numbers JKU/ISERC/02316/0818 and P522/06/2023, on 23rd February and 24th August 2023, respectively. A Research permit was also obtained from the National Commission for Science, Technology & Innovation (NACOSTI) under license number NACOSTI/P/23/24644, on 17th April 2023. A study certificate was also issued by the KNH Medical Research Department, to allow the registration of the research project and data collection process, on 31st August 2023. All participants gave written or oral informed consent to participate in this study. Authorization to access and use patient contact information to seek consent, schedule interviews and access hospital medical records for data, was sought from the KNH Administration. Patients available physically at the hospital as either in or out patients and gave written consent to participate in the study, were interviewed face to face by trained Research Assistants (RAs), while those who were unavailable physically gave oral consent during telephone interviews. Permission to waive written consent for telephone interviewed participants was sought in the proposal approved by the KNH-UON ERC. Participants were interviewed in privacy, and data collected was handled with confidentiality through the use of identity codes to conceal the patient identities and by limiting access to the raw data collected to the Principal Investigator only.
Data availability
Underlying data
Dryad: Research data on health facility-level factors that contribute to delayed diagnosis of cervical cancer, https://doi.org/10.5061/dryad.dz08kps5m12
This project contains the following underlying data:
- Data.xlsx
- README.md
Data are available under the terms of the Creative Commons Zero “No rights reserved” data waiver (CCO 1.0 Public domain dedication)
Extended data
Dryad: Research data on health facility-level factors that contribute to delayed diagnosis of cervical cancer, https://doi.org/10.5061/dryad.dz08kps5m12
This project contains the following extended data:
- INFORMED CONSENT FORM.pdf
Data are available under the terms of the Creative Commons Zero “No rights reserved” data waiver (CCO 1.0 Public domain dedication)
Software availability statement
The quantitative analysis in this article was performed using Stata version 14.2, a proprietary statistical software (https://www.stata.com/). For those without access to Stata, equivalent analyses can be performed using open-source alternatives such as R (https://cran.r-project.org/bin/windows/base/).
The qualitative analysis in this article was performed using NVivo 14, a proprietary qualitative data analysis software. For more information about NVivo, visit the NVivo website (https://lumivero.com/resources/free-trial/nvivo/). For those without access to Stata, equivalent analyses can be performed using open-source alternatives such as Taguette (https://www.taguette.org/).
Acknowledgements
We acknowledge the JKUAT School of Public Health and the KNH administration and staff for their approval and support in mobilization and actualization of this project.
Faculty Opinions recommendedReferences
- 1.
Cervix uteri. 2020. Reference Source
- 2.
Rendle KA, Ramogola-Masire D, Monare B, et al.:
Patient perspectives on delays in cervical cancer screening and follow-up care in Botswana: a mixed methods study.
BMC Womens Health.
2022; 22(01): 195. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 3.
Globocan:
Africa. [cited 2022 Sep 28]. Reference Source
- 4.
Globocan:
Kenya. [cited 2022 Sep 28]. Reference Source
- 5.
Osok D, Karanja S, Kombe Y, et al.:
Assessing factors associated with survival among cervical cancer patients in Kenya: a retrospective follow-up study.
East Afr Health Res J.
2018; 02(02): 118–127. PubMed Abstract
| Free Full Text
- 6.
Makena Frida K, Carole Atieno WM, Habtu M:
Socio-demographic factors associated with advanced stage of cervical cancer at diagnosis in Kenyatta National Hospital, Kenya: a cross sectional study.
J Cancer Sci Ther.
2017; 09(07): 554–561. Publisher Full Text
- 7.
Korir Anne Rugutt B:
Barriers to early diagnosis of invasive cervical cancer among patients receiving treatment at Kenyatta National Hospital, Nairobi Kenya. 2014. Reference Source
- 8.
Zeleke S, Anley M, Kefale D, et al.:
Factors associated with delayed diagnosis of cervical cancer in Tikur Anbesa Specialized Hospital, Ethiopia, 2019: cross-sectional study.
Cancer Manag Res.
2021; 13: 579–585. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 9.
Dereje N, Addissie A, Worku A, et al.:
Extent and predictors of delays in diagnosis of cervical cancer in Addis Ababa, Ethiopia: a population-based prospective study.
JCO Glob Oncol.
2020; 6: 277–284. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 10.
Deogratius Mwaka A, Garimoi CO, Maloba E, et al.:
Social, demographic and healthcare factors associated with stage at diagnosis of cervical cancer: cross-sectional study in a tertiary hospital in Northern Uganda.
BMJ Open.
2016; 6(1): 277–284, e007690.
PubMed Abstract
| Publisher Full Text
| Free Full Text
- 11.
Plaisy MK, Boni SP, Coffie PA, et al.:
Barriers to early diagnosis of cervical cancer: a mixed-method study in Côte d’Ivoire, West Africa.
BMC Womens Health.
2023; 23(1): 135. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 12.
Zammit M:
Research data on health facility-level factors that contribute to delayed diagnosis of cervical cancer. [Dataset]. Dryad. 2024. http://www.doi.org/10.5061/dryad.dz08kps5m