Introduction
Since the outbreak of COVID-19 pandemic, testing strategies were a critical component in the EU’s efforts to prevent, contain and mitigate the impact of the disease. Identifying infected individuals and preventing further virus transmission was essential to rapidly mitigate the pandemic, and for its subsequent control, allowing citizens to restart travelling and re-joining social activities and work-related tasks. The European Commission (EC) adopted various policy documents and legal acts to support Member States (MS) in the implementation of their COVID-19 testing strategies1. The EU Digital COVID Certificate (EUDCC) was introduced on July 1, 20212, serving as the digital proof that, amongst others, a person had received a negative COVID-19 test result.
To support EU level public health decision-making on COVID-19 antigen testing, a scientific process was put in place, consisting of three connected parts, for i) evidence identification and clarification, ii) evidence-based policymaking, and iii) policy implementation for citizen Benefit via the EUDCC. A graphical overview of the whole process for ensuring safe and reliable COVID-19 antigen testing is presented in Figure 1.
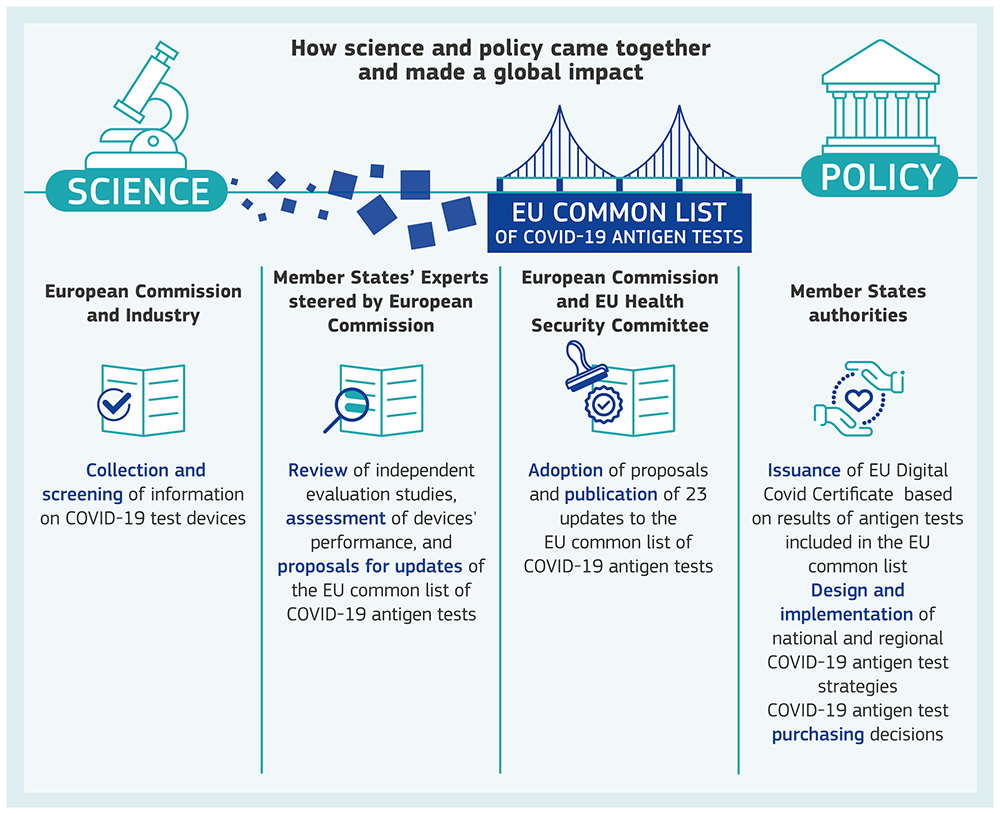
Figure 1. Science and policy together.
Visual of how science and policy came together and made a global impact for ensuring safe and reliable COVID-19 antigen testing.
Policy outcomes and implications
Evidence identification and clarification
At the start of the pandemic, evidence on efficiency and reliability of COVID-19 antigen testing policies as well as available antigen devices was scarce. Later during the pandemic, the situation turned around and available information became extensive but scattered. There was therefore a need to create a platform to make information and data provided by the research community, as well as manufacturers, available in one place.
Testing strategies are a key element in the control of a pandemic event, in terms of identification of infected individuals and application of related measures, such as like self-isolation, controlling social interactions3, or facilitating an early return to work after quarantine or isolation. Effective testing needs to be fast (to minimise the time an infected person can have contact with others), reliable (to avoid false negatives), at a low cost (to be accessible across different population groups), and widely deployable (to be available to the whole population).
The COVID-19 in Vitro Diagnostic Devices and Test Methods Database (DB) was developed4 to meet this need. It stands as one of the most comprehensive inventories of COVID-19 testing devices and methods globally. It makes relevant information on the performance of in vitro diagnostic medical devices and laboratory-developed methods for COVID-19 publicly available and up to date. With more than 2 600 testing devices and methods stored, it has been accessed by visitors from more than 168 countries5. The information and metadata collected in the database remain publicly accessible and available for eventual studies needs on methods and devices.
Evidence-based policymaking
Among the testing possibilities, rapid antigen tests (RATs), despite being less accurate than PCR tests in identifying presence of viral RNA and thus infection, are more suitable to detect infectiousness, being much faster, cheaper, and easy to use, enabling immediate interventions and guiding quarantine and mobility decisions6,7. Consequently, the role played by COVID-19 RATs became significant, and the number of devices available on the EU market increased exponentially during the pandemic.
In September 2020, the EU Health Security Committee (HSC) began gathering data on RATs performance from evaluation studies conducted within MS.
Following this, the Council of the European Union issued a Council Recommendation8 in January 2021. This recommendation called upon EU MS to agree on and maintain a common list of COVID-19 antigen tests, and to mutually recognise the result of those tests included. As a result, the first EU common list of COVID-19 antigen tests was published in February 2021.
Initially, device inclusion in the list was based on market availability and manufacturer’s claims. However, RATs efficacy was vital for the effectiveness of the EUDCC implementation, needing an efficacy verification system, through a transparent evaluation procedure with well-defined scientific criteria. For this, in May 2021, the HSC set up a specialised Technical Working Group on COVID-19 diagnostic tests (TWG). The purpose of the TWG was to evaluate submissions from countries and manufacturers for devices to be included to the EU common list, based on the criteria established by the Council Recommendation of January 2021 (CE marking, minimum performance requirements of ≥ 90% sensitivity and ≥ 97% specificity, and validated by at least one Member State). These criteria were updated and expanded by the TWG and underwent a constant verification process to ensure their correspondence to the fast changing scientific and epidemiological situation9.
Furthermore, the TWG, along with the Commission and the European Centre for Disease Prevention and Control, was tasked with drafting a technical guidance for the independent validation of the devices.
A dedicated system (based on EUSurvey, CIRCABC and the DB) was developed and used by manufacturers to upload applications, and by the TWG to collect relevant information and data to be reviewed for their devices assessment for possible inclusion in the EU common list. The system ensured confidentiality and expert anonymity while swiftly managing sensitive information. This workflow facilitated the integration of science into policy. It allowed for the responsibility of EU common list modifications to remain in MS’ hands, through the HSC, while ensuring that decisions were based on scientifically solid evaluations.
Since its first publication, the EU common list and the list of criteria have undergone 23 revisions, taking into account the results of new validation studies, the introduction of new devices to the market, the epidemiological developments, and the emergence of new SARS-CoV-2 variants. Around 50% of the submitted applications of devices were successful and thus included in the EU common list10. The latest version of the list can be found on the TWG COVID-19 diagnostic tests webpage11.
As of 1 July 2021, under the EUDCC Regulation (EU) 2021/953, all devices enclosed in the EU common list and carried out by health professionals or qualified testing personnel could be used by MS to issue EUDCC test certificates, and (as of 22 February 2022) EUDCC recovery certificate.
Policy implementation for citizen benefit via the EUDCC
The DB was updated and adapted to include the evolving EU common list. The list was automatically extracted from the database on daily basis. The extracted information, converted into a language-independent data format file (JSON), was and still is accessible at a static URL12.
This served as the foundation for the information displayed on the EUDCC test and recovery certificates that were based on antigen testing. The EUDCC facilitated safe travel for citizens across the European Union, enabled the establishment of mitigation measures, and allowed to coordinate the lifting of restrictions when possible.
The EUDCC has also been a success worldwide: it has set a global standard for international travel and has been the only system in operation at international level. An example of digital EUDCC is presented in Figure 2.

Figure 2. Example of digital EUDCC.
The figure is the mobile screenshot of an EUDCC issued in Italy after testing, in which “RAT Test name and manufacturer” are expressed as the numerical code (1610) assigned to the antigen tests in the COVID-19 in Vitro Diagnostic Devices and Test Methods Database.
Actionable recommendations
The capitalization of lessons learned in the context of the EU common list and its related evaluation process by experts can be precious for future needs, as they can facilitate the development of a workflow in case of future public health emergencies, such as reflected also by other multi-stakeholder communities13.
The work that was carried out by the TWG came with a heavy workload that required proper and efficient management. In total, the TWG reviewed over 1 100 manufacturer applications, declining over time without reaching a plateau. To support their work, the Commission screened applications for compliance before transmitting them to TWG experts, significantly reducing the TWG workload by approximately 40%. For future needs, it is recommended to foresee a screening process with dedicated personnel.
EC platforms were used for information exchange and document management. When the amount of documents to be included in the manufacturer’s applications increased, due to evaluation criteria becoming stricter, the limits of the platforms capacity became a limiting factor. Future systems should be more flexible or anticipate increased documentation load.
Dedicated mailboxes were established for communication with manufacturers and TWG: the volume of non-compliant applications and support requests reached an overwhelming amount of over 18 000 emails. Thus, adequate resources for help-desk staff are recommended for future needs.
The TWG conducted independent evaluations of applications, with plenary meetings both for reaching consensus and for revising requirements. While written procedures were employed when a meeting could not be arranged, meetings demonstrated to be essential for discussing device performance and revising guidelines and criteria. Adequate resources for the organisation of regular meetings are recommended for future planning.
The initial version of the common list featured 26 devices, reaching 279 devices by the end of the exercise. The dynamic list required a comprehensive management approach, leading to the adoption of a "master file" for discussions and assessments. Future planning should anticipate such solution and allocate necessary resources accordingly.
Challenges, solutions, and recommendations are summarised in Table 1.
Table 1. Challenges, solutions and recommendations.
| Challenge | Adopted solution | Recommendation |
|---|
| High and irregular workload for experts | Initial screening of data | Foresee skilled support staff |
| High volume of confidential data | Platforms for information exchange and for document management and storage | Foresee a flexible and scalable system since the beginning |
| Need for constant exchange of information with manufacturers | E-mail help desk | Foresee flexible staff for secretarial support |
| Need to discuss data and criteria | Written procedure and organisation of meetings | Foresee organization of regular meetings |
| Enormous amount of data processed, re-processed and adjusted, and relative discussions, outcomes and assessments | Creation of a master-file | Allocation of resources for file management |
Conclusions/Discussion
The crisis prompted the development of an action protocol that had a direct impact on the health and well-being of EU citizens. It facilitated secure information exchange between manufacturers and experts, with swift adaptability and robust security measures. Within the EU, it allowed to agree on a list of antigen tests that were meeting common criteria. This supported countries in developing and implementing COVID-19 testing strategies as well as issuing the relevant EUDCC test and recovery certificates, allowing the introduction of societal measures to contain the infectiousness and curb the infection. In preparation for potential future pandemics, a list of agreed rapid tests is crucial for the implementation of quarantine measures. In addition, the EU common list provided support to MS procurement procedures and national insurance and reimbursement schemes. At the global level, the EU common list also facilitated travelling through the EUDCC, and indirectly provided quality standards to be used as a global reference. In total, 51 countries across four continents have benefited from the EUDCC system, lately adopted (including its links to the DB) as the first building block of the WHO Global Digital Health Certification Network that will develop digital products “to deliver better health for all”14, potentially widening the use of digital certificates.
A unified evaluation framework by Member State experts reduced duplication of efforts and ensured uniform decisions, benefiting all. Furthermore, industry had to follow guidelines based on the scientific criteria set by the TWG.
The coordinated EU response minimized duplication and conflicting standards among Member States, enabling faster citizen-centric actions and knowledge sharing. To ensure a swift and effective response to future emergencies, key proposed actions include the immediate nomination of a Team of Experts, the establishment of an independent management team, the development of working procedures and performance criteria, and the creation of detailed guidance and of a solid information exchange system.
Lessons learnt are crucial for future preparedness.
This knowledge can help minimise delays between evidence availability and policy implementation across various critical public health issues.
The universality of the scientific method transcends political boundaries, ensuring its applicability across diverse contexts. As evidenced by the adoption of the EUDCC not only in Europe but also in nations worldwide, our reliance on the scientific method underscores its efficacy in informing evidence-based policy decisions globally.
Disclaimer
The views expressed in this article are those of the author(s). Publication in Open Research Europe does not imply endorsement of the European Commission.
List of abbreviations
CIRCABC: Communication and Information Resource Centre for Administrations, Businesses and Citizens.
DB: COVID-19 in Vitro Diagnostic Devices and Test Methods Database
EU: European Union
EUDCC: EU Digital COVID Certificate
EUSurvey: European Union Survey management system
HSC: Health Security Committee
MS: Member States
RATs: Rapid antigen tests
TWG: Technical Working Group on COVID-19 diagnostic tests
Data availability
No data are associated with this article.
Contributions
BR, MP drafted the manuscript. BR, MP, GL, MQ provided technical comments to improve the manuscript. BR, MP, GL, MQ reviewed & edited. All authors read and approved the final manuscript.
Acknowledgements
We would like to acknowledge Veronique Vanherck for her great graphic skills that managed to summarise a complex process into the nice visual we used as Figure 1.
Faculty Opinions recommendedReferences
- 1.
Commission Recommendation (EU) 2020/1595 of 28 October 2020 on COVID-19 testing strategies, including the use of rapid antigen tests. OJ L 360, 30.10.2020; 43. Reference Source
- 2.
Regulation (EU) 2021/953 of the European parliament and of the council of 14 June 2021 on a framework for the issuance, verification and acceptance of interoperable COVID-19 vaccination, test and recovery certificates (EU Digital COVID Certificate) to facilitate free movement during the COVID-19 pandemic. OJ L 211, 15.6.2021; 1–22. Reference Source
- 3.
Burnside G, Cheyne CP, Leeming G, et al.:
COVID-19 risk mitigation in reopening mass cultural events: population-based observational study for the UK Events Research Programme in Liverpool City Region.
J R Soc Med.
2024; 117(1): 11–23. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 4.
Petrillo M, Querci M, Tkachenko O, et al.:
The EU one-stop-shop collection of publicly available information on COVID-19 in vitro diagnostic medical devices [version 1; peer review: 2 approved].
F1000Res.
2020; 9: 1296. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 5.
Raffael B, Munoz-Pineiro MA, Petrillo M, et al.:
JRC: the one-stop-shop for COVID-19 test information. European Commission, 2023; JRC128837. Reference Source
- 6.
Mina MJ, Peto TE, García-Fiñana M, et al.:
Clarifying the evidence on SARS-CoV-2 antigen rapid tests in public health responses to COVID-19.
Lancet.
2021; 397(10283): 1425–1427. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 7.
Crozier A, Rajan S, Buchan I, et al.:
Put to the test: use of rapid testing technologies for COVID-19.
BMJ.
2021; 372: n208. PubMed Abstract
| Publisher Full Text
- 8.
Council Recommendation on a common framework for the use and validation of rapid antigen tests and the mutual recognition of COVID-19 test results in the EU 2021/C 24/01. OJ C 24, 22.1.2021; 1–5. Reference Source
- 9.
EU Common list of COVID-19 antigen tests - Agreed by the Health Security Committee.
Reference Source
- 10.
Raffael B, Petrillo M, Leoni G, et al.:
How science supported EU policy making in ensuring safe and reliable COVID-19 antigen testing. Publications Office of the European Union, Luxembourg, 2024. Publisher Full Text
- 11.
Technical working group on COVID-19 diagnostic tests. Reference Source
- 12.
https://covid-19-diagnostics.jrc.ec.europa.eu/devices/hsc-common-recognition-rat
- 13.
Community Testing Review. Reference Source
- 14.
https://www.who.int/initiatives/global-digital-health-certification-network




