Background
Virtual reality (VR) is a fully computer-generated environment that, through the use of head-mounted stereo displays (HMDs) and spatial tracking of the head, aims to provide a sense of immersion in the generated environment (XR Safety Initiative, 2025). Although the spatial, spectral and temporal fidelity of HMDs continues to advance, all current commercially available HMDs remain constrained by a single fixed focal plane, limiting natural depth perception. In natural stereoscopic vision, accommodation (the ability to focus and maintain clear vision) and vergence (coordinated eye movements to maintain single vision) are complementary and necessary to fuse the two retinal images into a single stereoscopic percept. The HMD’s stereoscopic displays can generate appropriate binocular disparities that initiate vergence responses consistent with the simulated depth of virtual objects. However, because the displays share a single, fixed focal distance, the accommodation demand remains constant and fixed regardless of the simulated depth. Thus, VR technologies suffer from a vergence-accommodation conflict (VAC) (Wann & Mon-Williams, 1996). The VAC has been linked to increased subjective discomfort such as visual fatigue and cybersickness symptoms (Kim et al., 2014; Saredakis et al., 2020), disrupted depth perception (Naceri et al., 2015), slower decision-making, and changes in oculomotor functions (Szpak et al., 2019).
The growing adoption of immersive technologies across areas such as gaming, entertainment, education, healthcare, and the military (Perkins Coie, 2024) has led to increasing integration of VR technologies in everyday life. However, successful adaptation to VR environments may be limited by widespread common vision problems, such as refractive errors (Williams et al., 2015), anomalous binocular vision (Garcia-Munoz et al., 2016; Gomes & Franco, 2024; Hagen et al., 2020), and poor or absent depth perception (Hess et al., 2015). Affecting more than half of the population (Vision Loss Expert Group of the Global Burden of Disease et al., 2024; Yekta et al., 2022; Williams et al., 2015), these conditions can be effectively corrected with prescription eyeglasses or contact lenses (Hess et al., 2015) and do not cause visual impairment such as blindness, low vision or eye diseases. Despite this, common vision problems may still influence user performance and comfort in VR environments. Even subtle limitations in visual or oculomotor capabilities, such as not using the necessary prescription correction or having reduced binocular vision, may become more pronounced during VR use and negatively impact user experience. Furthermore, VR use itself may affect visual and oculomotor function, even among individuals with normal or corrected-to-normal vision (Sumarokova et al., 2024). Here, visual function refers to visual acuity and depth perception, while oculomotor function refers to accommodation, vergence and other eye movements. Studies have reported both improvement (Munsamy et al., 2020) and deterioration (Szpak et al., 2020) of oculomotor functions post-VR, but no change in visual function (Tychsen & Foeller, 2020). These findings suggest that the use of VR technologies may affect visual and oculomotor functions differently across individuals, possibly due to differences in baseline visual and oculomotor capabilities, or characteristics of the VR environment.
As the use of VR technologies is predicted to increase (Alsop, 2024), it is important to understand how the use of VR technologies affects visual and oculomotor functions in individuals with normal vision, corrected-to-normal vision and common vision problems, as well as how visual and oculomotor capabilities influence performance and user comfort during and following VR exposure. A clear understanding of the interaction between visual and oculomotor functions and use of VR is essential for designing inclusive VR technologies that ensure accessibility and user comfort. Existing research on this topic remains inconclusive, with findings reporting both improvements and deteriorations in oculomotor functions following VR exposure. This inconsistency suggests gaps in current knowledge and underscores the need for an overview of existing evidence.
Review objective and questions
The primary objective of this scoping review was to map the current knowledge on the interaction between visual and oculomotor functions and the use of VR technologies in individuals with or without common vision problems. In this review, common vision problems are defined as prevalent conditions such as refractive errors, abnormal binocular vision, or poor or absent depth perception. This definition explicitly excludes visual impairments that occur less frequently, such as blindness, low vision, and vision loss due to eye diseases (World Health Organization, 2019).
Review questions were:
- How do visual and oculomotor factors impact performance and user comfort during and following VR exposure?
- How does the use of VR technologies affect visual and oculomotor functions?
- What are the current knowledge gaps of the interaction between visual and oculomotor functions and the use of VR?
Methods
The scoping review was conducted in accordance with the Joanna Briggs Institute (JBI) Manual for Evidence Synthesis (Peters et al., 2020) and followed the Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR) reporting guidelines (Tricco et al., 2018). A preliminary search in the Cochrane Database of Systematic Reviews and JBI Evidence Synthesis in January 2025, confirmed that no existing scoping review protocols on the topic were available. However, one systematic literature review on vergence and accommodation changes post-VR was identified (Gomez-Patino et al., 2024), but the present scoping review aims to explore broader contexts, such as the interaction between visual and oculomotor functions and VR use. A protocol was developed prior to conducting the review with its details described further in the text.
Eligibility criteria
Eligibility criteria were defined using the Participants, Concept and Context framework proposed by JBI (Peters et al., 2020). The review included studies that examined the interaction between visual and oculomotor functions and the use of VR technologies. Studies on human participants of any age were included. To be included, the studies had to report measurements of vision parameters, such as assessment of visual acuity, accommodation, binocular vision, or interpupillary distance, either before, during, or after the participants engage with VR. Studies conducted in experimental, clinical, or research settings, using fully immersive stand-alone or tethered stereoscopic VR headsets (Angelov et al., 2020), were included. Since the scoping review focuses on common vision problems, studies addressing vision impairment, such as blindness, low vision, or eye diseases, as well as vision rehabilitation or enhancement were excluded.
Only peer-reviewed studies published in English and available in full text were considered. Additionally, the review focused on studies published from 2016 onwards, as this period marks the introduction of accessible consumer headsets (VR Space, 2024; Wang et al., 2022).
Information sources
The review included quantitative studies with experimental and epidemiological designs, such as randomized and non-randomized trials, quasi-experimental, pre-post, cohort, case-control, and cross-sectional studies. Qualitative studies, reviews, letters, editorials, conference proceedings, and abstracts were excluded.
Search strategy
To identify relevant studies, a systematic search was performed. Controlled vocabulary terms, synonyms, and related terms for the concepts visual or oculomotor functions and virtual reality technologies were mapped and reviewed by the authors. The search strategy was adapted for each database and its thesaurus, in consultation with specialist librarians. Searches were conducted in Medline (Ovid), Web of Science, and Scopus on May 1, 2025, while an updated search was performed on December 4, 2025. Medline (Ovid) provides a comprehensive coverage of biomedical research, while Web of Science and Scopus offer a broad multidisciplinary scope, including engineering and technology fields overlapping with specialized databases such as IEEE Xplore. Backward citation chaining was conducted on December 8, 2025, by screening the reference lists of all included studies. The detailed search strategy for each database and the protocol for backward citation chaining used in this scoping review are openly available in the DataverseNO repository via doi: 10.18710/HJDTX7 (Krastina et al., 2026).
Source of evidence selection
After the search was conducted, all records were imported into EndNote (Clarivate, 2013). Duplicate removal was performed using the built-in duplicate detection function, followed by a manual check based on titles, journal names, and other metadata. Title and abstract screening was performed independently by two reviewers (IK, LAH) using Rayyan (Ouzzani et al., 2016). Disagreements were resolved by consulting a third reviewer (ES). Two reviewers (IK, LAH) independently screened full-text studies to determine study inclusion and reasons for exclusion. After consistency between the reviewers was achieved, the eligible full-text studies were reviewed by the first reviewer (IK).
Data extraction
A data extraction table was developed to align with the review objectives and validated by two reviewers (IK, LAH). To ensure consistency in extraction process, both reviewers independently extracted data from a subset of studies (n = 5; 19%). After agreement between reviewers was achieved, data extraction for all included studies was performed by the first reviewer (IK) using the data extraction table. The extracted data included:
•
Study characteristics: Authors, title, publication year, journal, and country of data collection. The country of data collection was determined from the location given in the methods section or, if not stated, from the country where ethical approval was obtained.
•
Participant characteristics: Sample size, age and sex/gender distribution, and eligibility criteria for each study related to vision parameters.
•
VR intervention characteristics: Type of VR headset and its specifications (as provided in the study), type and duration of the VR task.
•
Vision data: Type of vision measurements performed, vision measurement outcomes, vision-associated comfort measures (visual fatigue, eyestrain, cybersickness recorded during or following VR exposure), as well as performance measures related to vision (distance and size perception, task-solving ability).
•
Main outcome: The main results on the interaction between visual and oculomotor functions and VR exposure, as reported in the study.
In line with scoping review methodology (Peters et al., 2020), a formal critical appraisal of included studies was not conducted, as the aim was to map the available evidence rather than to evaluate methodological quality of studies.
Analysis and presentation of results
A PRISMA flow diagram (Tricco et al., 2018) was used to illustrate the study selection process, and Microsoft Excel for Mac V.16.100.1 (Microsoft Corporation, Redmond, Washington, USA) was used for evidence mapping and to perform descriptive analysis.
Study, participant, and VR intervention characteristics were summarised to highlight areas where current research may be incomplete or lack diversity. The remaining findings were presented in two sections. The first section included studies that evaluated how visual and oculomotor factors affected performance and user comfort during and after the use of VR technologies. The second section included studies that assessed how the use of VR technologies affected visual and/or oculomotor functions.
Results
The study selection process is illustrated in the PRISMA flow diagram (Tricco et al., 2018) in
Figure 1. The search identified 2917 records, of which 1342 were duplicates, resulting in 1575 records for screening. Of these, 1531 were excluded in the title- and abstract-screening stage. For full text review, 44 reports were assessed, of which one was not possible to retrieve in full text. Seventeen studies were excluded for one of the following four reasons: (1) did not use fully immersive stereoscopic VR headsets; (2) did not report the type of VR HMD used; (3) did not report measurements of vision parameters; (4) was out of scope. After full-text review, 26 studies were included in the scoping review for data extraction. Two additional reports were identified and included through updated search and citation chaining.
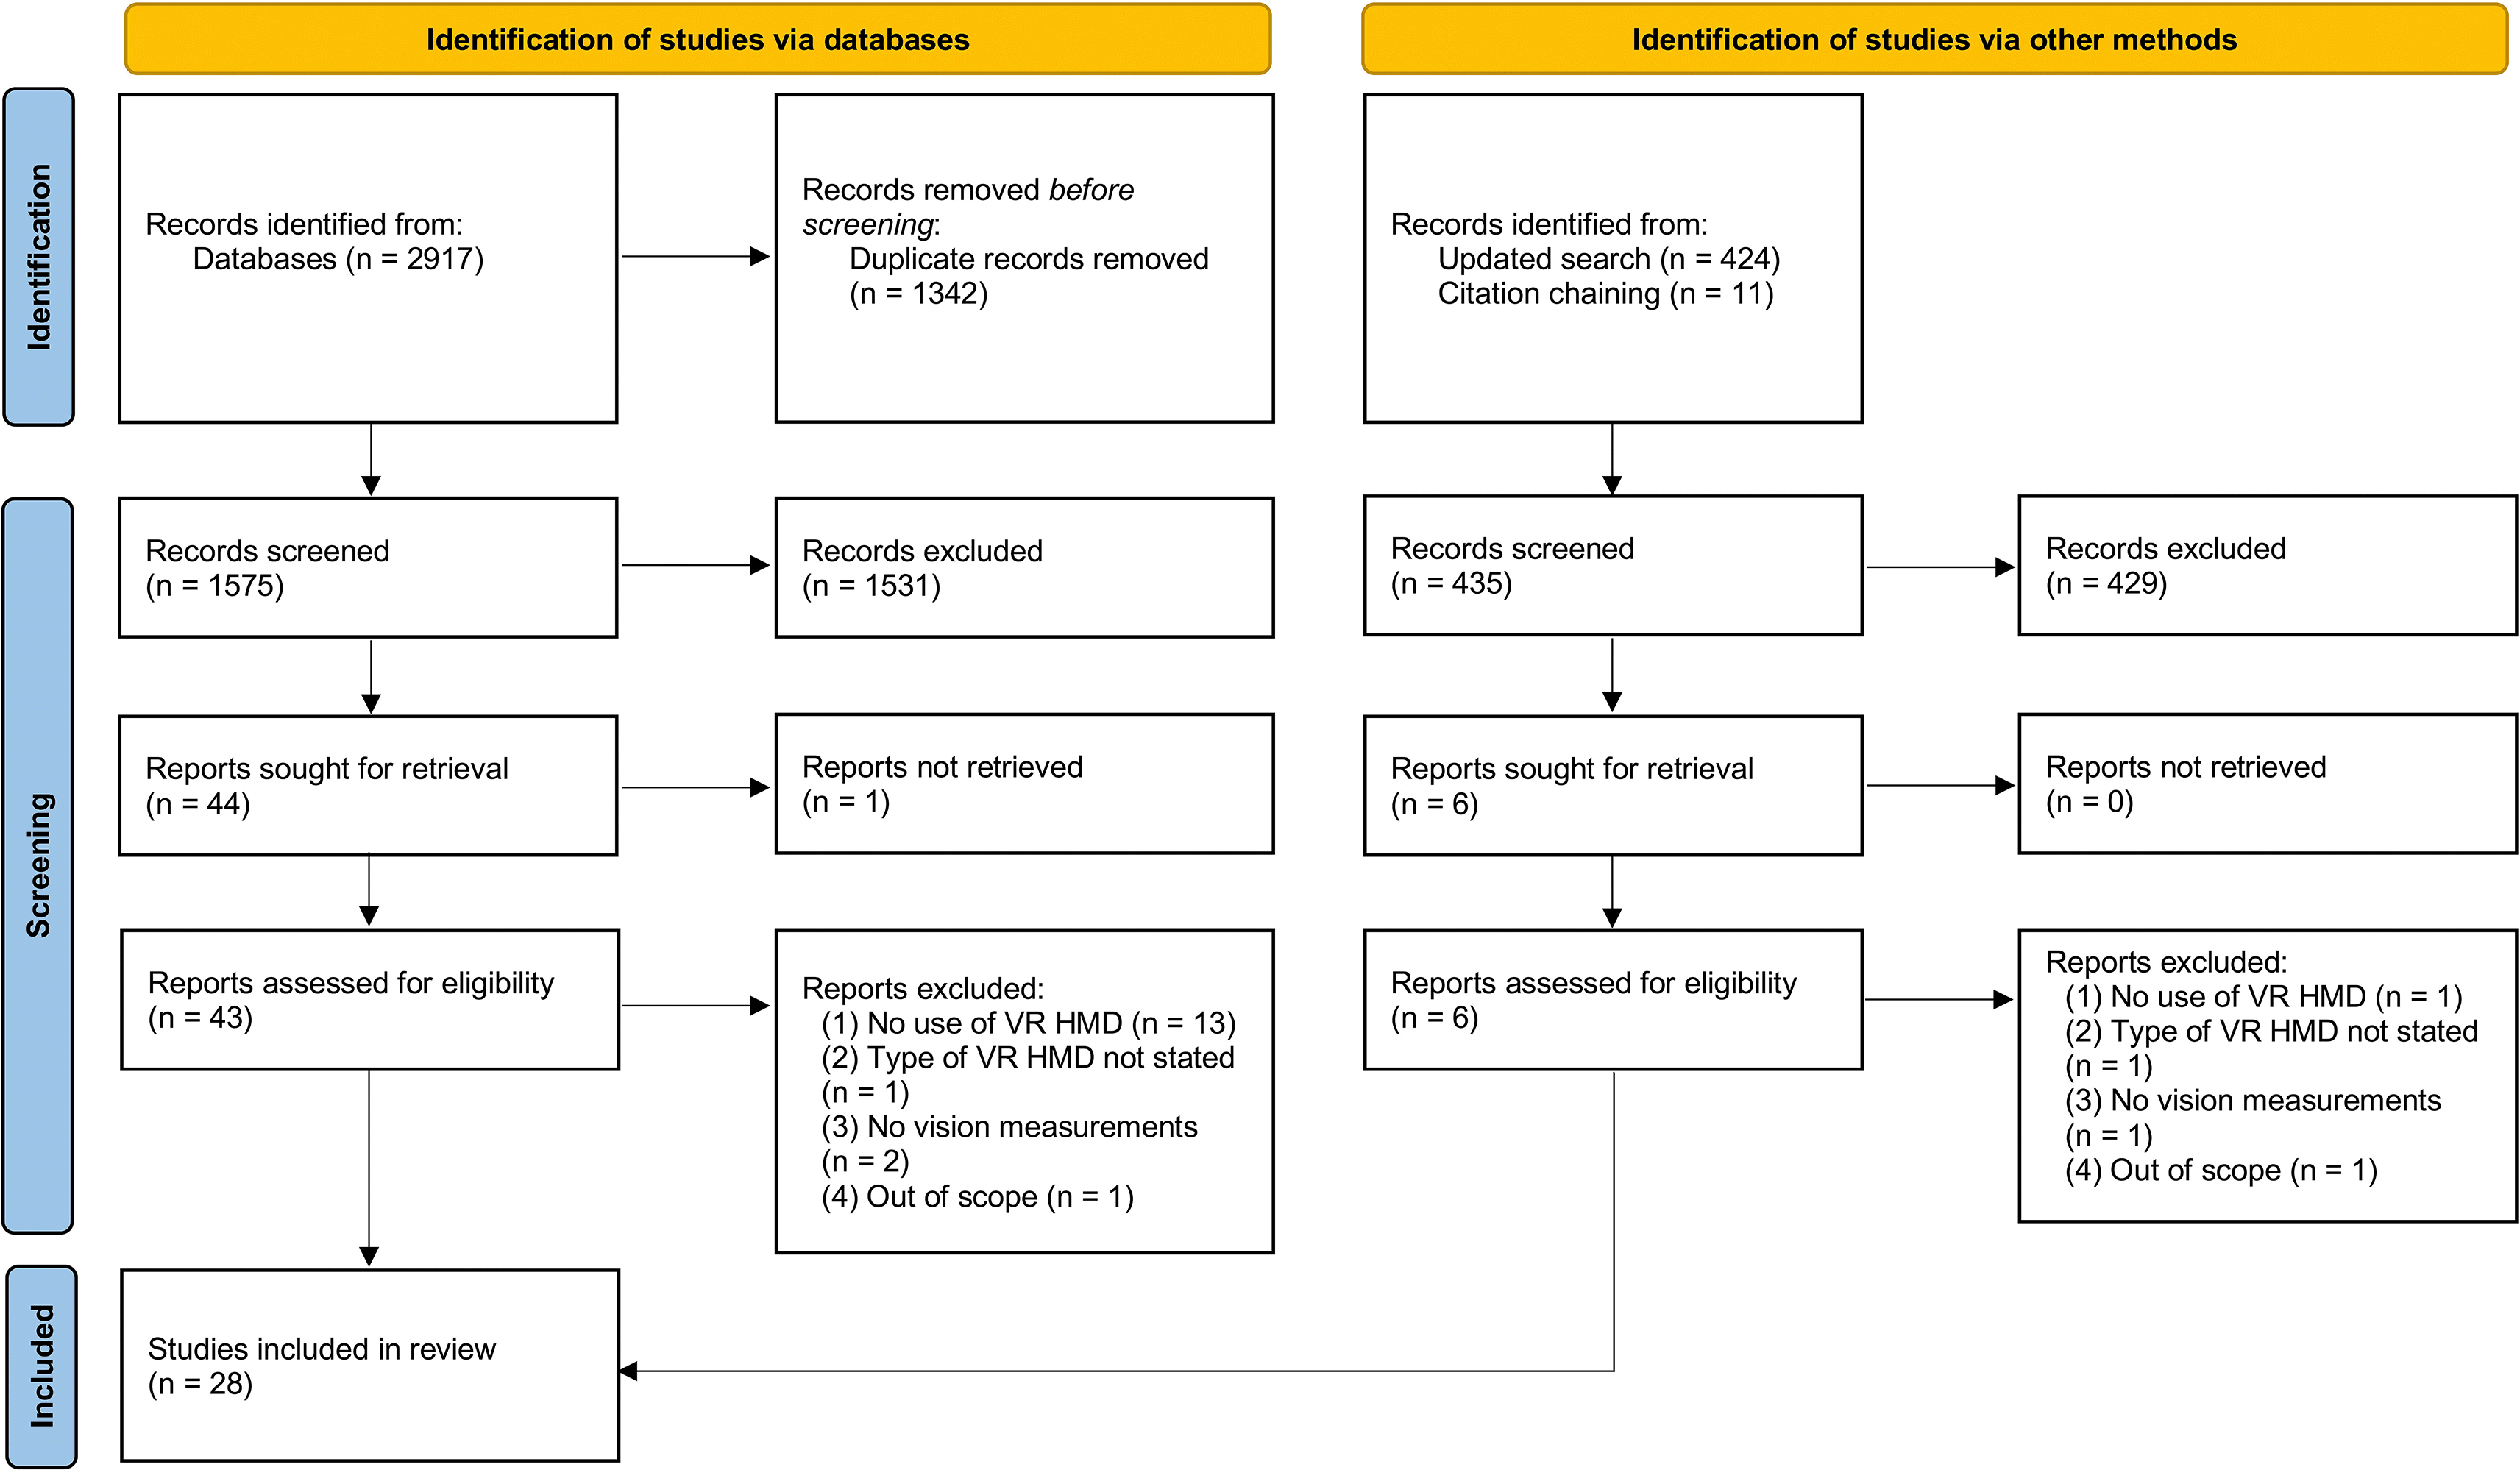
Figure 1. PRISMA flow diagram.
PRISMA flow diagram illustrating the study selection process, including records identified from Medline (Ovid), Web of Science, and Scopus as well as from updated search and backward citation chaining.
Study characteristics
A total of 28 studies from 13 countries were included, the majority of which were from Australia (n = 5) and Canada (n = 5), followed by the Republic of Korea (n = 4). The scoping review included studies published since 2016, the majority being published in 2021 (n = 7) and 2020 (n = 6). Distribution of studies by country of data collection and publication year is shown in
Figure 2.
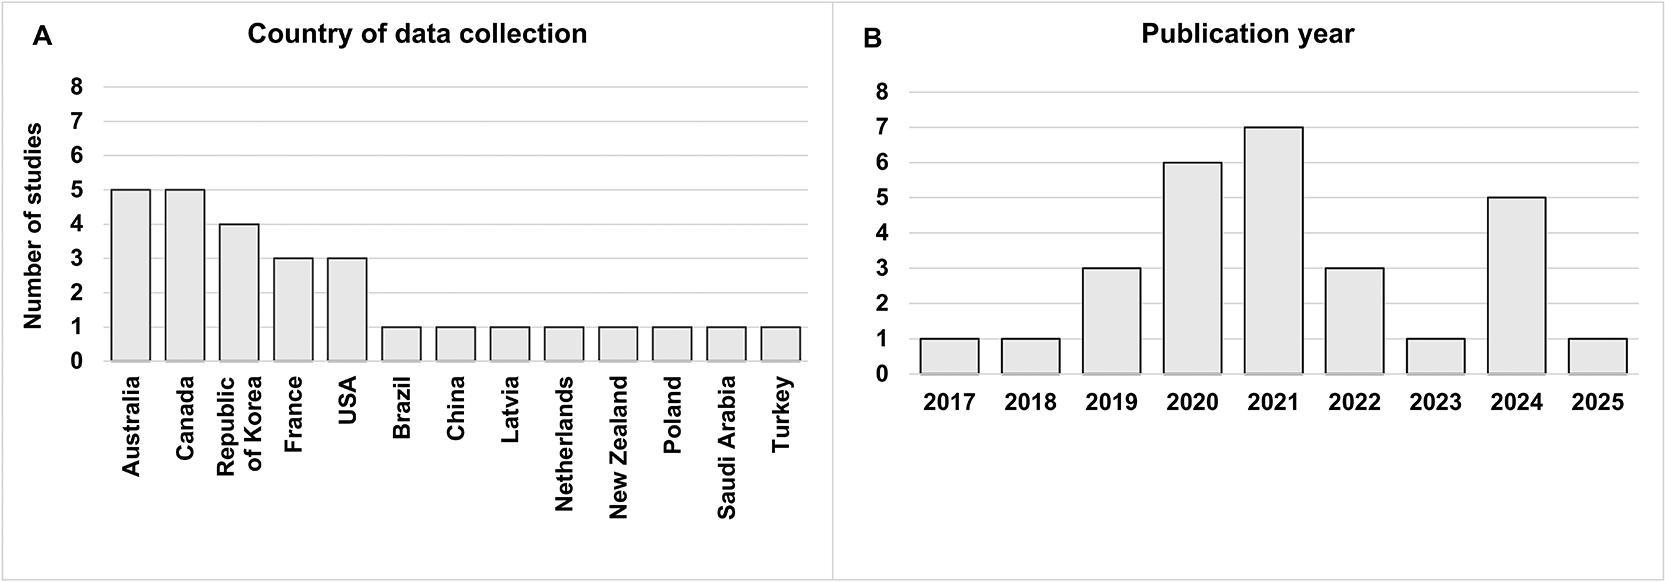
Figure 2. Characteristics of reviewed studies.
Number of studies by (A) country of data collection, and (B) publication year.
Participant characteristics
Figure 3 shows an overview of sample size, age and sex/gender distribution of the reviewed studies. The sample size varied from eight (Hartle & Wilcox, 2021) to 140 participants (Wainman et al., 2020), with the majority (46%) having 11 to 30 participants (Figure 3A). Most studies (64%) conducted their research with participants aged 18 to 32 years (Figure 3B). Regarding sex/gender distribution, 54% of the studies reported having between 40% and 60% female participants (Figure 3C). Two studies (7%) included fewer than 40% females, whereas five (18%) studies included more than 60% females. Three studies (11%) reported participant dropout due to discomfort, affecting 2% (Pala et al., 2021a), 6% (Tychsen & Foeller, 2020), and 4% (Yoon et al., 2020) of their participants. In another study (Sumarokova et al., 2024), 2% were unable to complete the VR task, but the reason was not specified.
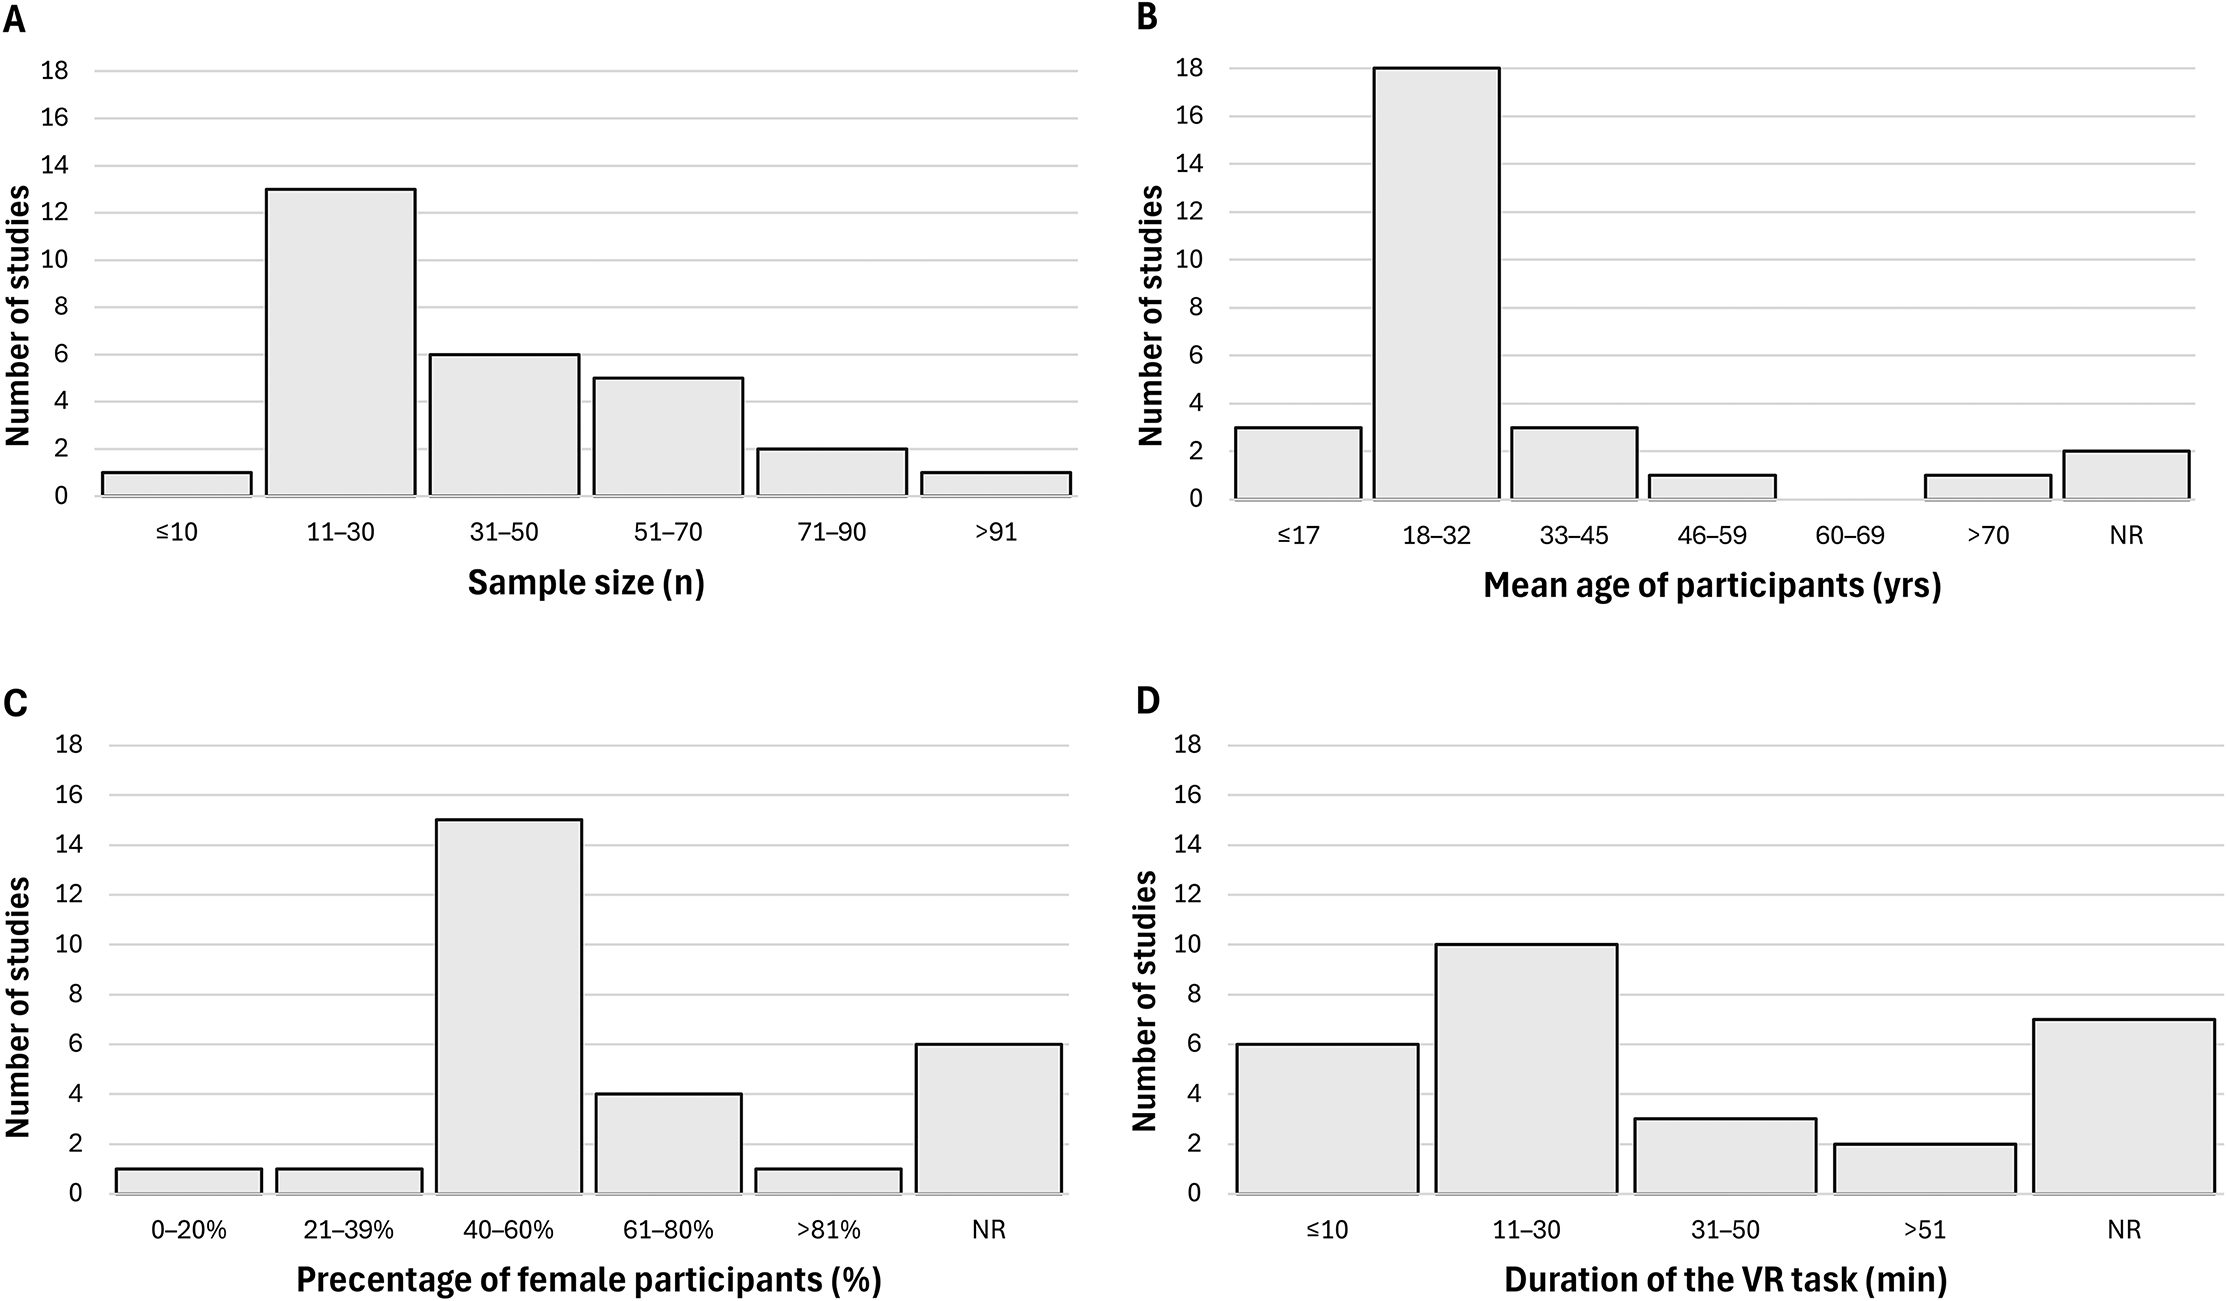
Figure 3. Participant characteristics and duration in VR across studies.
Participant characteristics, including (A) sample size, (B) age, and (C) sex/gender distribution presented as percentage of females (%), as well as (D) duration of the VR task performed. NR = not reported.
Eligibility criteria related to vision parameters
Of the 28 studies reviewed, 23 (82%) reported eligibility criteria related to vision parameters, as summarised in
Table 1. The most common inclusion criterion was normal or corrected-to-normal distance visual acuity (71%, n = 20), however, half of these studies did not define any threshold for normal visual acuity and/or relied on the participants’ subjective self-assessment.
Table 1. Eligibility criteria related to vision parameters.
Summary of inclusion criteria for vision parameters as identified in the reviewed studies (n = 23). Five studies did not report any eligibility criteria related to vision. NS = not specified.
VR intervention characteristics
Figure 3D summarises the duration of VR exposure across the studies. In ten studies (36%), the duration ranged from 11 to 30 minutes, while five studies (18%) reported sessions shorter than 11 minutes. In seven (25%) of the studies, duration was not reported, but task descriptions suggest most lasted less than 20 minutes. In four studies (14%), VR immersion was repeated at least twice, with visual and oculomotor functions measured after each session (Collet et al., 2025; Szpak et al., 2020; Turnbull & Phillips, 2017; Tychsen & Foeller, 2020). The remaining studies had one VR session. For the VR task, the studies used commercially available VR games (43%, n = 12), custom-made tasks designed for VR (39%, n = 11), playback of a 3D video (11%, n = 3), or learning simulations (7%, n = 2).
Impact of visual and oculomotor factors on performance and user comfort in VR
Eleven (39%) of the 28 reviewed studies evaluated how visual and oculomotor factors affected user comfort and performance during and after VR use.
Table 2 gives an overview of the five studies focusing on user comfort, addressing cybersickness and visual fatigue in adult participants with sample sizes ranging 20–46 participants. Ten minutes of VR gameplay was associated with greater degree of cybersickness in participants with slightly reduced stereoacuity or presence of exophoria (latent divergent misalignment of the eyes) (Dericioglu & Kubat, 2024). Iskander and Hossny (2021) reported that the vergence-accommodation conflict may increase the load on the vergence system in VR, leading to changes in vergence eye movements and increased visual fatigue. Note that only one-third of the participants who habitually wore prescription glasses used them during this experiment (Iskander & Hossny, 2021). Lee et al. (2021) found that simulated anisometropia (difference in refractive error between eyes) of 1 D had a minimal impact on visual fatigue during or post-VR exposure. Longer exposures (20–30 minutes) were linked to greater cybersickness symptoms in participants with smaller positive fusional vergence (Son et al., 2024) or a mismatch between the user’s interpupillary distance (IPD) and the inter-display distance in the VR headset (Stanney et al., 2020). Interpretation of these findings is limited by short VR durations (10–30 minutes) and incomplete reporting of baseline visual and oculomotor functions.
Table 2. Overview of studies on the impact of visual and oculomotor parameters on VR user comfort.
User comfort is here limited to cybersickness symptoms and visual fatigue. Sex/gender distribution is given as percentage of females (%F). NR = not reported. IPD = interpupillary distance. NPC = near point of convergence. NPA = near point of accommodation.
|
Study | Time in VR | VR task | Participant characteristics | Vision measurements | Summary of visual-oculomotor interaction with VR |
|---|
| n | Mean age (yrs) ± SD (range) |
%F |
|---|
| Stanney et al. (2020) | 20 min | Riding a virtual rollercoaster | 46 | 18 to 30 | 50 | Pre-VR: field of view, IPD | A larger mismatch between IPD and the inter-display distance in VR headsets was associated with higher levels of cybersickness. |
| Iskander and Hossny (2021) | ~10 min | Visually following a cube across different depths, and moving virtual balls between two height levels | 26 | 29.84 ± 7.28 (21 to 45) | NR | During VR: eye movements | Greater variability in vergence angle and reduced stability of eye movements in VR were associated with visual fatigue. |
| Lee et al. (2021) | 10 min | VR gameplay during simulation of 1D anisometropia | 34 | 35.3 ± 7.6 (21 to 50) | 47 | Pre-VR: dominant eye
Pre- and post-VR: accommodative micro fluctuation, NPA, refractive error | Simulated anisometropia of 1D had minimal effect on visual fatigue. |
| Dericioglu and Kubat (2024) | 10 min | VR gameplay | 20 | 29.8 ± 0.57 | 55 | Pre-VR: refractive error, phoria
Pre- and post-VR: accommodation, stereoacuity, pupil size | Increased cybersickness symptoms post-VR were associated with poorer stereopsis and exophoria pre-VR. |
| Son et al. (2024) | 30 min | VR gameplay | 32 | 24.94 ± 4.20 | 63 | Pre-VR: refractive error
Pre- and post-VR: distance and near phoria, NPC, positive and negative fusional vergence at distance and near, vergence facility | Smaller positive vergence reserves at baseline were associated with increased cybersickness. |
Six studies explored how visual and oculomotor factors affected performance in VR. See
Table 3 for an overview. Performance was assessed using task-based measures, including learning outcomes, block-building, depth and object perception tasks. Based on the methods descriptions, it was not possible to establish visual demand, and although most studies required participants to have good distance vision, definitions and assessment methods were rarely reported, whereas stereovision criteria was defined as better than 50 (Hartle & Wilcox, 2021, 2022; Rzepka et al., 2023; Wainman et al., 2020). Most studies (83%) did not report the time spent in VR. The presence of stereovision was associated with higher precision of depth estimates (n = 8 and 16) (Hartle & Wilcox, 2021, 2022) and with higher test scores in a learning task (Wainman et al., 2020), whereas its absence was associated with lower test scores (n = 40) (Wainman et al., 2020). However, in an object size perception task, participants relied more on their prior knowledge than binocular cues (n = 22) (Rzepka et al., 2023). Exotropia (manifest divergent misalignment of the eyes) was associated with slower completion of block-building tasks (n = 39) (Chung et al., 2021). Additionally, a mismatch between the user’s IPD and the inter-display distance in the VR headset, was associated with perceptual distortions (n = 14) (Tong et al., 2022). Interpretation of these findings remains limited by small sample sizes, in some cases as few as 8 participants, poorly described baseline visual and oculomotor functions, and unclear duration of VR exposure.
Table 3. Overview of studies on the impact of visual and oculomotor parameters on performance in VR.
Performance refers here to distance and size judgement, as well as learning outcomes. Sex/gender distribution is given as percentage of females (%F). NR = not reported. IPD = interpupillary distance.
|
Study | Time in VR | Task in VR | Participant characteristics | Vision measurements | Summary of visual-oculomotor interaction with VR |
|---|
| n | Mean age (yrs) ± SD (range) |
%F |
|---|
| Wainman et al. (2020) | 10 min | Learning anatomy in physical, mixed and virtual environments with and without binocular cues | 140 | 18.9 ± 1.5 | NR | Pre-VR: stereoacuity | Removing binocular cues reduced learning more in VR than in physical or mixed environments. |
| Chung et al. (2021) | NR | Watching a car moving away and performing a block-building task | 76 | 6 to 12 | 45 | Pre-VR: stereoacuity, ocular deviation During VR: amount of divergence | Children with exotropia completed block-building tasks in VR more slowly than their peers. |
| Hartle and Wilcox (2021) | NR | Estimating depth in three conditions: (1) motion parallax alone, (2) binocular disparity alone, and (3) both combined | 8 | NR | NR | Pre-VR: IPD | Depth perception was more precise with binocular disparity alone or in combination with motion parallax, compared with motion parallax alone. Similar results were found in a physical environment. |
| Hartle and Wilcox (2022) | NR | Estimating depth at two distances (83 cm and 130 cm) in physical and virtual environments under both monocular and binocular viewing conditions | 16 | NR | NR | Pre-VR: IPD | Depth judgments were more precise under binocular than monocular viewing conditions, however, it was worse in VR than in physical environments. |
| Tong et al. (2022) | NR | Adjusting the angle between two surfaces to 90° under various viewing conditions and IPD settings | 14 | 33 | 50 | Pre-VR: IPD | Minor mismatches between IPD and inter-display distance in the VR headsets led to slant misperception. |
| Rzepka et al. (2023) | NR | Estimating the perceived size and distance of virtual objects in binocular and monocular conditions | 22 | 18 to 25 | NR | Post-VR: dominant eye, stereoacuity | Participants relied on familiar size despite available binocular cues in VR. |
Impact of VR technology use on visual and oculomotor functions
Twenty of the 28 reviewed studies (71%) evaluated the impact of VR technology use on visual and/or oculomotor functions, by performing vision measurements during or pre- and post-VR exposure.
Tables 4–7 provide an overview of the studies, categorized by the vision parameters assessed: vergence eye movements and accommodation (
Table 4), heterophoria (latent misalignment of the eyes) and heterotropia (manifest misalignment of the eyes) (
Table 5), stereoacuity (
Table 6), and refractive error and visual acuity (
Table 7).
Table 4. Overview of studies on the impact of VR technology use on vergence and/or accommodation.
Sex/gender distribution is given as percentage of females (%F). NR = not reported. IPD = interpupillary distance. NPA = near point of accommodation. NPC = near point of convergence.
|
Study |
Time in VR | Task in VR | Participant characteristics | Vision measurements | Summary of visual-oculomotor interaction with VR |
|---|
| n | Mean age (yrs) ± SD (range) |
%F |
|---|
| Turnbull and Phillips (2017) | 40 min + 40 min | Exploring physical and virtual indoor environments, and physical and virtual outdoor environments | 19 | 24.7 ± 4.0 (18 to 35) | 53 | Pre- and post-VR: fixation stability and disparity, NPA, phoria, stereoacuity, choroidal thickness | No changes in NPA post-VR, nor between conditions. |
| Guo et al. (2019) | 60 min | VR gameplay with and without breaks compared to smartphone gameplay with and without breaks | 80 | 23.23 ± 1.78 | 34 | Pre- and post-VR: distance visual acuity, pupil size, accommodation response | VR use had minimal impact on accommodation compared to smartphone use, and taking breaks improved accommodation recovery. |
| Iskander et al. (2019) | ~3 min | Focusing on a cube changing position and depth, and following a slowly moving cube at a constant depth | 26 | 29.46 ± 7.5 (21 to 45) | NR | During VR: calculated vergence angles, fixation | Vergence angles varied more in VR than in physical environments, leading to visual fatigue. |
| Szpak et al. (2019) | 30 min | VR gameplay | 55 | 21.60 ± 3.13 | 40 | Pre-VR: stereoacuity, visual acuity
Pre- and post-VR: NPA, NPC | Poorer NPA post-VR, with no change in NPC. |
| Drew et al. (2020) | ~30 min | Gameplay in VR and physical environment | 41 | ≥ 18 | 46 | Pre-VR: stereoacuity, fixation disparity
Pre- and post-VR: vergence facility, binocular accommodative facility | Binocular accommodative and vergence facility improved post-VR, similar to after a comparable physical task. |
| Szpak et al. (2020) | 10 min (day 1) + 50 min (day 2) | VR gameplay | 36 | 20.55 ± 2.29 | 42 | Pre-VR: stereoacuity, visual acuity
Pre- and post-VR: NPA, NPC | Poorer NPA and NPC after 10- and 50-min VR gameplay. Results returned to baseline after approximately 40 min. |
| Yoon et al. (2020) | 30 min | VR gameplay in two settings: immersive (360-degree VR environment) vs. non-immersive (fixed, static VR environment) | 23 | 23.9 ± 3.7 (20 to 35) | 52 | Pre- and post-VR: refraction, accommodation response, NPA, NPC, stereoacuity, distance and near phoria | Poorer NPA and NPC post-VR. Similar decrease in NPC as after non-immersive gameplay. No changes in other measurements of accommodation. |
| Alhassan et al. (2021) | 45 min | VR gameplay | 52 | 22.5 ± 2.0 (19 to 27) | 50 | Pre- and post-VR: monocular NPA, accommodation accuracy, negative and positive relative accommodation, monocular and binocular accommodative facility, distance and near phoria, NPC, positive and negative fusional vergence ranges, vergence facility | Diminished monocular and binocular accommodative facility, accommodation accuracy, negative relative accommodation, fusional vergence at near, and vergence facility. No change in NPA, positive relative accommodation, NPC, or fusional vergence at distance. |
| Lee et al. (2021) | 10 min | VR gameplay during simulation of 1D anisometropia | 34 | 35.3 ± 7.6 (21 to 50) | 47 | Pre-VR: dominant eye
Pre- and post-VR: accommodative micro fluctuation, NPA, refractive error | Decrease in NPA and increase in accommodative micro fluctuation post-VR, but no effect of simulated anisometropia. |
| Pielage et al. (2022) | NR | Fixating a target moving from periphery-to-centre or far-to-near | 29 | 25.9 (19 to 40) | 66 | During VR: pupil size | Pupil near response intact in VR, despite their direct link to vergence. |
| Dericioglu and Kubat (2024) | 10 min | VR gameplay | 20 | 29.8 ± 0.57 | 55 | Pre-VR: refractive error, associated and dissociated phoria
Pre- and post-VR: accommodation response, stereoacuity, pupil size | No changes in accommodation. Increase in pupil diameter. |
| Dymczyk et al. (2024) | 30 min | VR gameplay with simulation of two different levels of VAC: small and large | 18 | 22.5 (19 to 27) | 100 | Pre- and post-VR: accommodation response, associated and dissociated phoria, fusional vergence ranges, NPC | No change in accommodation response, NPC, or fusional vergence at near or distance post-VR, nor between the levels of VAC. |
| McAnally et al. (2024) | ~2 min | Alternating fixation between near (0.3 m) and far (100 m) targets | 30 | 27.2 | 67 | During VR: eye movements (vergence), pupil size | Frequent errors in vergence eye movements in VR, especially at near. |
| Son et al. (2024) | 30 min | VR gameplay | 32 | 24.94 ± 4.20 | 63 | Pre-VR: refractive error
Pre- and post-VR: distance and near phoria, NPC, positive and negative fusional vergence at distance and near, vergence facility | Diminished NPC, vergence facility, fusional reserves, and increase in exophoria at distance and near post-VR. |
| Sumarokova et al. (2024) | 20 min | VR gameplay for two groups: with and without binocular and/or accommodative disorders | 62 | 22 ± 4 | 79 | Pre-VR: subjective refractive error, stereoacuity, phoria, positive and negative fusional vergence, positive and negative relative accommodation, vergence facility, binocular accommodative facility
Pre- and post-VR: objective refractive error, NPA, NPC, accommodation response | Diminished NPA and NPC, and decrease in accommodation lag post-VR, with no significant effect of group. Accommodative micro fluctuations were more prevalent in the group with than without binocular and accommodative disorders. |
| Collet et al. (2025) | 20 min (day 1) + 40 min (day 2) + 60 min (day 3) | VR training simulation for pilots | 26 | 50.5 ± 4.6 (43 to 57) | 4 | Pre-VR: IPD, stereoacuity, visual acuity
Pre- and post-VR: NPA, NPC | No significant difference between NPA and NPC measurements taken pre- and post-VR sessions on any day. |
Table 5. Overview of studies on the impact of VR technology use on heterophoria and heterotropia.
Sex/gender distribution is given as percentage of females (%F). NR = not reported. IPD = interpupillary distance. NPA = near point of accommodation. NPC = near point of convergence.
|
Study | Time in VR | Task in VR | Participant characteristics | Vision measurements | Summary of visual-oculomotor interaction with VR |
|---|
| n | Mean age (yrs) ± SD (range) |
%F |
|---|
| Turnbull and Phillips (2017) | 40 min + 40 min | Exploring physical and virtual indoor environments, and physical and virtual outdoor environments. | 19 | 24.7 ± 4.0 (18 to 35) | 53 | Pre- and post-VR: fixation stability and disparity, NPA, phoria, stereoacuity, choroidal thickness | No differences in phoria or fixation disparity pre- vs post-VR or across conditions. |
| Kim et al. (2018) | NR | VR gameplay | 21 | 28.38 ± 6.87 | NR | Pre-VR: IPD, heterophoria
During VR: blink rate | Reduced blink rate in VR, associated with larger exophorias. |
| Tychsen and Foeller (2020) | 30 min + 30 min | VR gameplay | 50 | 7.2 ± 1.8 (4 to 10) | 42 | Pre-VR: IPD, visual-vestibulo-ocular reflex
Pre- and post-VR: visual acuity, refractive error, stereoacuity, associated and dissociated phoria | No change in heterophoria post-VR. |
| Yoon et al. (2020) | 30 min | VR gameplay in two settings: immersive (360-degree VR environment) vs. non-immersive (fixed, static VR environment) | 23 | 23.9 ± 3.7 (20 to 35) | 52 | Pre- and post-VR: refractive error, accommodation response, NPA, NPC, stereoacuity, distance and near phoria | No change in near heterophoria post-VR in any setting. |
| Alhassan et al. (2021) | 45 min | VR gameplay | 52 | 22.5 ± 2.0 (19 to 27) | 50 | Pre- and post-VR: monocular NPA, accommodation accuracy, negative and positive relative accommodation, monocular and binocular accommodative facility, distance and near phoria, NPC, positive and negative fusional vergence ranges, vergence facility | No change in phoria post-VR. |
| Chung et al. (2021) | NR | Watching a car moving away and performing a block-building task | 76 | 6 to 12 | 45 | Pre-VR: stereoacuity, ocular deviation
During VR: amount of divergence | Increase in exodeviation during VR in participants with exotropia. |
| Dymczyk et al. (2024) | 30 min | VR gameplay with simulation of two levels of VAC conditions: small and large | 18 | 22.5 (19 to 27) | 100 | Pre- and post-VR: accommodation response, associated and dissociated phoria, fusional vergence ranges, NPC | Associated heterophoria tended to shift to eso-direction with large VAC and exo-direction with small VAC, but the difference was not significant. No change and no effect of small vs. large VAC for dissociated heterophoria. |
| Son et al. (2024) | 30 min | VR gameplay | 32 | 24.94 ± 4.20 | 63% | Pre-VR: refractive error
Pre- and post-VR: distance and near phoria, NPC, positive and negative fusional vergence at distance and near, vergence facility | Increase in exophoria at distance and near post-VR. |
Table 6. Overview of studies on the impact of VR technology use on stereoacuity.
Sex/gender distribution is given as percentage of females (%F). NR = not reported. IPD = interpupillary distance. NPA = near point of accommodation. NPC = near point of convergence.
|
Study | Time in VR | Task in VR | Participant characteristics | Vision measurements | Summary of visual-oculomotor interaction with VR |
|---|
| n | Mean age (yrs) ± SD (range) |
%F |
|---|
| Turnbull and Phillips (2017) | 40 min + 40 min | Exploring physical and virtual indoor environments, and physical and virtual outdoor environments | 19 | 24.7 ± 4.0 (18 to 35) | 53 | Pre- and post-VR: fixation stability and disparity, NPA, phoria, stereoacuity, choroidal thickness | No change in stereoacuity post-VR, and no differences between virtual and physical environments. |
| Tychsen and Foeller (2020) | 30 min + 30 min | VR gameplay | 50 | 7.2 ± 1.8 (4 to 10) | 42 | Pre-VR: IPD, visual-vestibulo-ocular reflex
Pre- and post-VR: visual acuity, refractive error, stereoacuity, associated and dissociated phoria | No change in stereoacuity post-VR. |
| Yoon et al. (2020) | 30 min | VR gameplay in two settings: immersive (360-degree VR environment) vs. non-immersive (fixed, static VR environment) | 23 | 23.9 ± 3.7 (20 to 35) | 52 | Pre- and post-VR: refractive error, accommodation response, NPA, NPC, stereoacuity, distance and near phoria | No change in stereoacuity post-VR in any setting. |
| Pala et al. (2021a) | 15 min | Street crossing task | 55 | 70.96 ± 4.83 (64 to 81), 32.67 ± 4.66 (25 to 42) | 44, 47 | Pre- and post-VR: stereoacuity | No change in stereoacuity post-VR. |
| Pala et al. (2021b) | 30 min | Street crossing task | 56 | 32.67 ± 4.66 (25 to 42), 11.90 ± 0.28 (11 to 12) | 53, 50 | Pre- and post-VR: stereoacuity | No change in stereoacuity post-VR. |
| Dericioglu and Kubat (2024) | 10 min | VR gameplay | 20 | 29.8 ± 0.57 | 55 | Pre-VR: refractive error, associated and dissociated phoria
Pre- and post-VR: accommodation response, stereoacuity, pupil size | Decrease in stereoacuity post-VR. |
Table 7. Overview of studies on the impact of VR technology use on refractive error and/or visual acuity.
Sex/gender distribution is given as percentage of females (%F). IPD = interpupillary distance. NPA = near point of accommodation. NPC = near point of convergence.
|
Study | Time in VR | Task in VR | Participant characteristics | Vision measurements | Summary of visual-oculomotor interaction with VR |
|---|
| n | Mean age (yrs) ± SD (range) |
%F |
|---|
| Guo et al. (2019) | 60 min | VR gameplay with and without breaks compared to smartphone gameplay with and without breaks | 80 | 23.23 ± 1.78 | 34 | Pre- and post-VR: distance visual acuity, pupil size, accommodation response | No change in visual acuity post-VR, no effect of breaks on accommodation results. |
| Tychsen and Foeller (2020) | 30 min + 30 min | VR gameplay | 50 | 7.2 ± 1.8 (4 to 10) | 42 | Pre-VR: IPD, visual-vestibulo-ocular reflex
Pre- and post-VR: distance visual acuity, refractive error, stereoacuity, associated and dissociated phoria | No change in visual acuity or refractive error post-VR. |
| Yoon et al. (2020) | 30 min | VR gameplay in two settings: immersive (360-degree VR environment) vs. non-immersive (fixed, static VR environment) | 23 | 23.9 ± 3.7 (20 to 35) | 52 | Pre- and post-VR: refractive error, accommodation response, NPA, NPC, stereoacuity, distance and near phoria | No change in visual acuity or refractive error post-VR gameplay in any setting. |
| Lee et al. (2021) | 10 min | VR gameplay during simulation of anisometropia (1 D) | 34 | 35.3 ± 7.6 (21 to 50) | 47 | Pre-VR: dominant eye Pre- and post-VR: accommodative micro fluctuation and NPA, refractive error | Myopic shift post-VR, but no effect of 1D simulated anisometropia. |
| Sumarokova et al. (2024) | 20 min | VR gameplay for two groups: with and without binocular and/or accommodative disorders | 62 | 22 ± 4 | 79 | Pre-VR: subjective refractive error, stereoacuity, phoria, positive and negative fusional reserves, positive and negative relative accommodation, vergence facility, binocular accommodative facility
Pre- and post-VR: objective refractive error, NPA, NPC, accommodation response | Hyperopic shift post-VR gameplay, with no effect of group. |
Vergence eye movements
Across studies, 10–50 minutes of VR exposure was associated with a decline in near point of convergence (NPC, the closest distance at which single vision is maintained). All studies employed the same method (“push-up”) for NPC assessment in adult participants with sample size ranging from 18 to 62 participants. Four studies reported significant declines of 1–2 cm in NPC (Son et al., 2024; Sumarokova et al., 2024; Szpak et al., 2020; Yoon et al., 2020), another four studies observed non–significant declines of 0.4–1.2 cm (Alhassan et al., 2021; Collet et al., 2025; Dymczyk et al., 2024; Szpak et al., 2019). Studies (Collet et al., 2025; Szpak et al., 2020) assessing NPC following repeated sessions and during recovery reported a return to baseline within 30–40 minutes, suggesting that the observed effects were transient. However, interpretation is limited by incomplete description of baseline visual and oculomotor functions, short VR exposures and limited assessment of effect persistence.
Three studies assessed vergence facility (the ability to rapidly and precisely shift the gaze between near and far objects) after 30–45 minutes of VR gameplay in young adults with sample size ranging from 32 to 52 participants. Two studies (Alhassan et al., 2021; Son et al., 2024) reported statistically significant reductions of 1–2 cycles per minute (cpm) in vergence facility. In contrast, one study reported a significant improvement (Drew et al., 2020), however, the same effect was also measured in the control group performing a comparable task in a physical environment, suggesting a potential learning effect. All three studies used a binocular flipper equipped with 3 prism dioptres (PD) base-in and 12 PD base-out to assess vergence facility. Drew et al. (2020) conducted the measurement over two minutes as opposed to one minute in the other studies (Alhassan et al., 2021; Son et al., 2024). Comparison across studies was limited by variability in baseline vergence facility values and inconsistent reporting (Drew et al., 2020). The persistence of vergence facility changes was not assessed.
Three studies assessed fusional vergence following VR gameplay, using prism bars in 52 participants (Alhassan et al., 2021) or Risley prisms in a phoropter in 18 and 32 participants (Dymczyk et al., 2024; Son et al., 2024). Son et al. (2024) reported a significant decrease in both distance and near fusional vergences after 30 minutes in VR, with a reduction of up to 2 PD at distance and 5.5 PD at near, while Alhassan et al. (2021) reported a significant decrease of 3 PD in near fusional vergence after 45 minutes. In contrast, Dymczyk et al. (2024) reported no significant change after 30 minutes, regardless of the degree of the simulated vergence-accommodation conflict in the VR task. None of the studies reported abnormal baseline fusional vergence levels, and baseline values were comparable across the studies. Alhassan et al. (2021) interpreted the observed deterioration as an indication for binocular vision dysfunction. However, other studies did not discuss the clinical relevance.
Two studies explored vergence eye movements in VR and suggested that the use of VR may increase the vergence load, leading to higher vergence angle variability (n = 26) (Iskander et al., 2019) and errors in vergence eye movements (n = 30) (McAnally et al., 2024). In the study by Iskander et al. (2019), approximately one third of the participants who usually wear prescription glasses wore them during the experiment (Iskander et al., 2019). The pupil near response is primarily coupled to vergence (Pielage et al., 2022), and, despite the vergence-accommodation conflict, pupil responses were found to be intact and unaffected in VR (n = 29) (Pielage et al., 2022). These findings are limited by poorly described baseline visual and oculomotor functions. The duration in VR was not explicitly reported, but task descriptions suggested most lasted less than 5 minutes.
Accommodation
Across studies, the effects of VR on accommodation varied. Eight studies evaluated short-term (10–50 minutes) VR exposure impact on accommodation amplitude or near point of accommodation (nearest distance where focus is maintained) in sample sizes ranging from 19 to 62 participants. Five studies (Lee et al., 2021; Sumarokova et al., 2024; Szpak et al., 2020; Szpak et al., 2019; Yoon et al., 2020) reported poorer accommodation measured either as diminished amplitude or near point of accommodation, with declines of 0.9–1.5 cm. In contrast, three studies reported a smaller deterioration in accommodation of approximately 0.5 D (Alhassan et al., 2021; Collet et al., 2025; Turnbull & Phillips, 2017). Studies assessing recovery reported a return to baseline within 30–40 minutes (Collet et al., 2025; Szpak et al., 2020). Although most studies included participants with normal accommodation and binocular vision, those that included individuals with pre-existing accommodative problems or simulated anisometropia suggested greater susceptibility to VR induced changes (Lee et al., 2021; Sumarokova et al., 2024). Baseline visual and oculomotor functions were inconsistently described, limiting comparability between the studies and generalizability.
Findings on short-term (30–45 minutes) VR impact on accommodative facility (ability to rapidly and precisely change focus between near and far) were inconclusive, with only two studies assessing this using the standard optometric practice of ±2 D flipper lenses (n = 52 and 41) (Alhassan et al., 2021; Drew et al., 2020). Both reported changes of approximately 2 cpm, with one study showing a deterioration (Alhassan et al., 2021) and the other an improvement (Drew et al., 2020). However, the improvement was also observed in the control group that performed a similar activity in a physical environment (Drew et al., 2020), suggesting a potential learning effect. Both studies included young adult participants with reported normal visual acuity and binocular vision. However, baseline accommodation function was not consistently reported.
Overall, minimal effects were observed across studies assessing accommodation response. Accommodation response was evaluated in four studies using an autorefractometer (Dericioglu & Kubat, 2024; Dymczyk et al., 2024; Guo et al., 2019) or a photorefractor (Sumarokova et al., 2024), with sample sizes ranging from 18 to 80. Only one study (Sumarokova et al., 2024) reported a significant decrease of 0.14 D in accommodation lag, indicating that the accommodation response more closely matched the image distance after 30 minutes of VR gameplay, with greater changes observed in participants with binocular or accommodative disorders compared to those without. The remaining studies reported no change after 10–60 minutes of VR gameplay (Dericioglu & Kubat, 2024; Dymczyk et al., 2024; Guo et al., 2019).
Accommodation reserves were assessed in one study (n = 52) (Alhassan et al., 2021), which reported reduced negative relative accommodation following 45 minutes of VR gameplay.
Heterophoria and heterotropia
Heterophoria and heterotropia following short-term (30–60 minutes) VR use were evaluated in seven studies, with smaple sizes ranging from 18 to 52 participants. Statistically significant exophoric shift of 2 PD was observed in participants with mild exophoria (Son et al., 2024) and increased exodeviation in children with exotropia (Chung et al., 2021). Large exophorias were also associated with reduced blink rate in VR, and consequently increased dry eye symptoms (Kim et al., 2018). The five remaining studies reported no significant changes (Alhassan et al., 2021; Dymczyk et al., 2024; Turnbull & Phillips, 2017; Tychsen & Foeller, 2020; Yoon et al., 2020). The magnitude of reported changes was small. Most studies included participants with normal distance visual acuity (typically ≥ 0.8), no heterotropia and low degrees of heterophoria, limiting generalizability. The persistence of the observed effect was not assessed.
No changes were observed in associated phoria (Dymczyk et al., 2024) after 10 minutes of VR gameplay or in fixation disparity (Turnbull & Phillips, 2017) after 40 minutes of immersion or across repeated sessions.
Stereoacuity
Changes in stereoacuity following short-term (10–60 minutes) VR gameplay were assessed in six studies, with sample sizes ranging from 10 to 55 participants. Five studies assessing stereoacuity with the Titmus Stereo Fly test (Turnbull & Phillips, 2017; Tychsen & Foeller, 2020; Yoon et al., 2020) or the Randot Stereotest (Pala et al., 2021a, 2021b; Tychsen & Foeller, 2020) reported unchanged stereoacuity. In contrast, one study (Dericioglu & Kubat, 2024) using the TNO test reported a statistically significant deterioration of 30″ after 10 minutes VR gameplay. Interpretation of the measured effects is limited by the inclusion of participants with normal visual acuity and stereoacuity, alongside inconsistent description of baseline oculomotor functions, and the methodological differences.
Refractive error and visual acuity
Small and inconsistent refractive shifts were reported following short-term (10–60 minutes) VR gameplay in sample sizes ranging from 23 to 62 participants. Sumarokova et al. (2024) reported a mean hyperopic shift of 0.05 D, measured by photorefractor. In contrast, Lee et al. (2021) reported a mean myopic shift ranging from −0.14 D to − 0.17 D, measured by subjective refraction. These shifts were unaffected by simulated anisometropia of 1 D (Lee et al., 2021) or by the presence of binocular or accommodative disorders (Sumarokova et al., 2024). Although statistically significant, the magnitudes were minimal. Two other studies reported no significant chnges in refractive error, measured by autorefraction, in young adults (Yoon et al., 2020) and children (Tychsen and Foeller, 2020) with normal binocular vision and distance visual acuity. None of the studies performed the measurements under cycloplegia, limiting comparability and accuracy of refractive assessment.
Distance visual acuity remained unchanged after 60 minutes VR gameplay in both children (Tychsen & Foeller, 2020) and young adults (Guo et al., 2019), suggesting no measurable short-term effect on visual acuity.
Discussion
A scoping review review of the current knowledge on the interaction between visual and oculomotor functions and VR use was conducted. The reviewed studies suggested that binocular vision status and improper adjustment of the VR headset could influence user comfort and performance. Studies reported inconsistent effects of VR immersion on vergence and accommodation functions, whereas most found no significant changes in visual acuity and stereoacuity. However, interpretation of these findings is limited by incomplete baseline visual and oculomotor function description, short-term durations in VR and other methodological variabilities across studies. The observed oculomotor changes may reflect the visual demand imposed by VR technologies, such as the vergence-accommodation conflict. This mismatch between vergence and accommodation cues may increase a load on the visual system, causing changes in oculomotor functions and user comfort.
Most of the reviewed studies focused on adults up to 45 years old, with limited research involving children (Chung et al., 2021; Tychsen & Foeller, 2020) and adults older than 45 (Collet et al., 2025; Pala et al., 2021a). Some studies explicitly excluded presbyopes, due to their age-related decline in accommodation ability (Dericioglu & Kubat, 2024) and concerns about increased susceptibility to cybersickness (Son et al., 2024). Studies reporting participants discontinuing VR use due to discomfort included children (Tychsen & Foeller, 2020), adults over the age of 45 (Pala et al., 2021a), participants with binocular or accommodative disorders (Sumarokova et al., 2024), and young adults (Yoon et al., 2020). Although these studies did not explore the association between dropouts and visual and oculomotor functions, age-related or baseline differences in oculomotor functions might have contributed to these findings. Further research is needed to understand how the use of VR technologies interacts with visual and oculomotor functions across diverse groups.
An important limitation across studies is the lack of comprehensive baseline assessment of visual and oculomotor functions. In many cases, studies defined eligibility criteria for normal baseline vision parameters, but often the eligibility criteria were incompletely defined or relied on participants self-reported assessment. This limits the interpretation both of the role of baseline visual and oculomotor functions in user comfort and performance in VR and the clinical relevance of post-VR changes. Furthermore, studies examining refractive error changes (Lee et al., 2021; Sumarokova et al., 2024; Tychsen & Foeller, 2020; Yoon et al., 2020) did not use cycloplegia, despite cycloplegic refraction being the gold standard for accurate measurements of refractive error and recommended for both children and young adults (Hagen et al., 2023; Morgan et al., 2015; Sun et al., 2018). Consequently, the reported changes in refractive errors (Lee et al., 2021; Sumarokova et al., 2024) may merely represent variations in accommodative responses (Morgan et al., 2015) with refractive errors remaining undetected. Undetected visual or oculomotor function problems could consequently have affected study results, thereby limiting the strength and generalisability of the evidence. Furthermore, while appropriate for controlled studies, the inclusion of participants with predominantly normal baseline vision parameters limits the generalizability of the findings, as the included populations do not reflect the variability in visual and oculomotor functions seen in actual VR users. For instance, more than half of the European population has refractive errors (Williams et al., 2015), yet many do not use prescription correction, as reflected by uncorrected refractive errors remaining the leading cause of visual impairment in both children and adults (Vision Loss Expert Group of the Global Burden of Disease et al., 2024; Yekta et al., 2022). Furthermore, approximately 30% of the general population has poor or absent depth perception (Hess et al., 2015), and up to one-third of young adults have binocular vision and/or accommodative disorders (Garcia-Munoz et al., 2016; Gomes & Franco, 2024; Hagen et al., 2020). Despite this, only few studies have explored these problems in the context of VR use. Two studies reported that one third of participants who normally wear prescription correction glasses did not wear them during VR immersion (Iskander & Hossny, 2021; Iskander et al., 2019). However, they did not discuss the potential impact this might have on performance or oculomotor functions. Some studies excluded participants who wore prescription glasses due to concerns about prismatic effects that can create barriers to VR usability (Son et al., 2024). In summary, research exploring how common vision problems interact with VR use remains limited.
The reviewed studies mainly involved short-term VR exposure, typically 10–30 minutes and demonstrated that even a brief 10-minute engagement in VR can lead to subjective discomfort (Dericioglu & Kubat, 2024; Szpak et al., 2020) and changes in oculomotor functions (Szpak et al., 2020). While short exposures may reveal initial effects (Saredakis et al., 2020), they do not reflect real-world settings, where VR sessions may be longer or repeated over time. Studies exploring longer exposure times and repeated effects (Collet et al., 2025; Szpak et al., 2020) reported that oculomotor changes often returned to baseline within 30–40 minutes (Collet et al., 2025; Szpak et al., 2020). However, adaptation and long-term effects remain unclear, as few studies have examined longer or repeated exposures. Consequently, the current evidence primarly reflects immediate responses rather that sustained alterations.
The type of VR task is another factor that needs to be considered when discussing the interaction between human vision and the use of VR technologies. Some studies employed controlled psychophysical experiments (Hartle & Wilcox, 2021, 2022; Rzepka et al., 2023), whereas most used commercially available VR gameplays, involving active participant engagement (Dericioglu & Kubat, 2024; Sumarokova et al., 2024; Szpak et al., 2020) or passive viewing (Stanney et al., 2020). Visual demand is influenced by the task characteristics, including stimulus complexity and environmental dynamics, as well as the vergence-accommodation conflict (VAC). The degree of the VAC is determined by the discrepancy between the focal plane distance and the percieved distance of the virtual image. However, the size of the VAC is often not reported or unknown and can vary both within one task and within the same study, as it depends on headset optics and task characteristics. The only reviewed study that examined the size of the vergence-accommodation conflict (Dymczyk et al., 2024) reported higher levels of cybersickness when the vergence-accommodation conflict was greater, but associations with oculomotor changes remains unclear, particularly in VR users with existing binocular vision or accommodative disorders.
Headset characteristics, such as IPD adjustment, have an impact on user comfort in VR. Mismatches between the user’s IPD and the inter-display distance in the VR headset has been linked to cybersickness symptoms (Stanney et al., 2020) and perceptual distortions (Tong et al., 2022). Previously, studies have suggested associations between IPD mismatch and changes in accommodation (Livitcuka et al., 2023) and vergence (Hibbard et al., 2020; Livitcuka et al., 2023). This is particularly relevant for children and females, as their IPD is typically smaller than that of adult males (MacLachlan & Howland, 2002). Small IPDs may pose a limitation for proper VR headset fit in these populations (Pala et al., 2021b). Although studies often mentioned adjusting the headsets, they rarely reported whether the participants’ IPD was within the headset’s adjustable range or whether IPD mismatch could be related to the study results, limiting the interpretation of results.
While most studies reported no changes in distance visual acuity and stereoacuity post-VR, accommodation and vergence outcomes were more variable. The only study that reported changes in stereoacuity post-VR gaming used the TNO test for stereovision assessment (Dericioglu & Kubat, 2024). This test contains no monocular cues, so that depth cannot be perceived with poor or no stereovision ( Fawcett & Birch, 2003). In contrast, studies reporting no change used either the Titmus Stereo Fly test (Turnbull & Phillips, 2017; Tychsen & Foeller, 2020; Yoon et al., 2020) or the Randot Stereotest (Pala et al., 2021a, 2021b; Tychsen & Foeller, 2020), both of which rely on contour detection that may be detectable monocularly (Fawcett & Birch, 2003). Because these tests assess different aspects of stereovision they are not directly comparable (Fawcett & Birch, 2003; Garnham & Sloper, 2006). Consequently, differences in reported stereoacuity outcomes and their interpretation may partly reflect the choice of the test. However, the decline in stereoacuity found by Dericioglu & Kubat (2024) is interesting because it corresponds with other oculomotor function effects such as significant deteriorations in near point of convergence (Son et al., 2024; Sumarokova et al., 2024; Szpak et al., 2020; Yoon et al., 2020), fusional vergence reserves (Alhassan et al., 2021; Son et al., 2024), amplitude of accommodation (Lee et al., 2021; Sumarokova et al., 2024; Szpak et al., 2020; Szpak et al., 2019; Yoon et al., 2020), and increase in exophoria and exotropia (Chung et al., 2021; Son et al., 2024). Although these changes were generally small and often remained within normal clinical ranges, they are commonly associated with binocular vision and accommodative disorders (Franco et al., 2022; Gantz & Stiebel-Kalish, 2022; Wajuihian, 2019). This suggests that VR exposure may exacerbate symptoms of binocular vision problems.
Although the reported changes in various oculomotor parameters were typically small and not clinically significant in individuals with normal visual and oculomotor functions, they may be relevant in those with pre-existing binocular or accommodative disorders, exodeviations or reduced fusional reserves. Emerging evidence from this review indicates that individuals with binocular vision or accommodative disorders (Sumarokova et al., 2024), exotropia (Chung et al., 2021), or anisometropia (Lee et al., 2021) may experience greater oculomotor changes, poorer performance, and increased discomfort in VR. However, interpretation and clinical relevance assessment remains limited by incomplete baseline assessment of visual and oculomotor functions, variability in study design and tasks. Notably, studies that reported reduced performance in VR (Hartle & Wilcox, 2021, 2022; Rzepka et al., 2023; Wainman et al., 2020) did not describe participants’ baseline visual and oculomotor functions, making it unclear whether the findings reflect underlying binocular vision problems or technical factors as IPD mismatch due to poorly adjusted VR headsets. Small sample sizes in many of the reviewed studies may further reduce the statistical power and the reliability of the findings.
Even though VR technologies have demonstrated relevance in vision therapy (Li et al., 2022; Shao et al., 2023) and visuomotor skill assessment (Chung et al. (2021)), this review highlights several risks that must be considered to ensure effective VR implementation. User comfort may be reduced by increased dry eye symptoms due to reduced blink rate during VR immersion (Kim et al., 2018) or limitations in headset design for children and others with small head sizes and narrow IPDs (Pala et al., 2021b). It is important to note that changes in visual and oculomotor functions can occur after as little as 10 minutes of VR immersion (Dericioglu & Kubat, 2024; Szpak et al., 2020), and discomfort following VR use tends to worsen with prolonged immersion (Szpak et al., 2020). The findings underscore the need for further research and clear guidelines for VR use and adjustable headset designs to accommodate diverse users, as also promoted by the Code of Conduct for the Human-Centered and Ethical Development of Immersive Technologies (Bernabe et al., 2025).
Strengths and limitations
Strengths of this review include the systematic search and methodology, both conducted in accordance with JBI guidelines (Peters et al., 2020) and PRISMA-ScR standards (Tricco et al., 2018). The eligibility criteria were designed to ensure that the VR technologies studied were relevant and currently in use, thereby enhancing the generalizability of findings. Including only peer-reviewed journal articles in the search strengthens the quality of the reviewed studies and further enhances the power of this review. Meanwhile, limiting the search to three databases and including only peer-reviewed journal articles in English language, may have restricted the scope and comprehensiveness of the review.
Conclusion
This scoping review suggests that VR use may be associated with potential disturbances in oculomotor functions, particularly in vergence and accommodation, while visual acuity is unaffected by short-term exposure. However, the interpretation of these findings is limited by small sample sizes, short durations and lack of baseline visual and oculomotor functions assessments. The observed changes were typically small and often whitin normal clinical ranges. Current research focuses mainly on young adults with no vision problems, leaving gaps in the knowledge about interaction between VR use and human vision across diverse populations. Understanding these gaps is important for accessible VR use, as common vision problems can affect user comfort, performance and safety. Future research should include comprehensive visual and oculomotor function assessments, exploring the effects in users with binocular or accommodative disorders, and examine long-term and repeated VR exposure to obtain robust conclusion on the interaction between human vision and the use of VR.







