Introduction
The increasing number and complexity of health research conducted in sub-Saharan Africa continue to drive the demand for robust research ethics oversight, efficient and consistent regulatory review, and functional pharmacovigilance systems.1 Public health emergencies, outbreaks, and evolving technologies have increased the need for regulatory bodies and ethics committees to adapt their processes while maintaining the protection of participants and quality standards in clinical trials.2
Despite bearing approximately 25% of the global disease burden, Africa accounts for only 0.02% of the clinical trials registered globally, even though the region represents approximately 15% of the world's population.3 Recent analyses highlight persistent under-representation: the 2024 Access to Medicine Index found that only 27.5% of late-stage research and development projects from 20 leading pharmaceutical companies included one or more African countries, and just 16 of 80 candidate medicines targeting priority diseases were tested in African settings.4 Common challenges facing clinical trial regulatory authorities and ethics committees in the region include limited funding, staffing constraints, infrastructure gaps, and shortages of specialized expertise. These constraints may contribute to delays in protocol review, reduce the frequency and quality of inspection and monitoring, and limit the capacity to manage safety reporting and data governance as the volume of clinical research increases.2
Several continental and regional initiatives support harmonization and shared learning in clinical trial oversight. The African Vaccine Regulatory Forum (AVAREF) facilitates joint reviews, capacity building, and emergency preparedness,5 while the African Medicines Agency (AMA) is being established to coordinate regulatory harmonization across the continent.6 The African Medicines Regulatory Harmonization (AMRH) initiative, led by the African Union Development Agency (AUDA-NEPAD), has advanced progress toward the African Medicines Agency (AMA), with milestones such as the 2025 Memorandum of Understanding among World Health Organization (WHO) Maturity Level 3 National Regulatory Authorities to foster collaboration and reliance.7–9 In Tanzania, strengthening ethics and regulatory systems has been supported through partnerships among regulatory bodies, universities, and research institutions, including capacity development initiatives funded by the European and Developing Countries Clinical Trials Partnership (EDCTP).10
The ASCEND project “Moving Tanzania’s Clinical Research Ethics and Medicines Regulatory Capacity to the Next Level” was implemented to enhance clinical trial oversight and pharmacovigilance capabilities in the Tanzania Mainland and Zanzibar. The project combined training, the operationalization, upgrading, and linkage of digital systems, community engagement in safety reporting, guideline domestication, and networking among researchers and regulators.
A qualitative synthesis of the lessons learned from the ASCEND project was published previously by the consortium.10 The present manuscript differs by presenting an implementation-focused case study that documents the components delivered, approaches used, and project period outputs. This manuscript is presented as a case study to support transparency and practical learning in capacity development for research ethics and clinical trial oversight.
Program description
Overview of implementation approach
The ASCEND project implemented a multi-component capacity development approach that combined targeted training, operationalization, upgrading, and linkage of digital systems, community engagement in pharmacovigilance, guideline domestication, and networking among key stakeholders (
Figure 1). Implementation activities were coordinated by partner institutions in Tanzania Mainland and Zanzibar, with roles aligned with institutional mandates for research ethics oversight, clinical trial regulation, and pharmacovigilance.
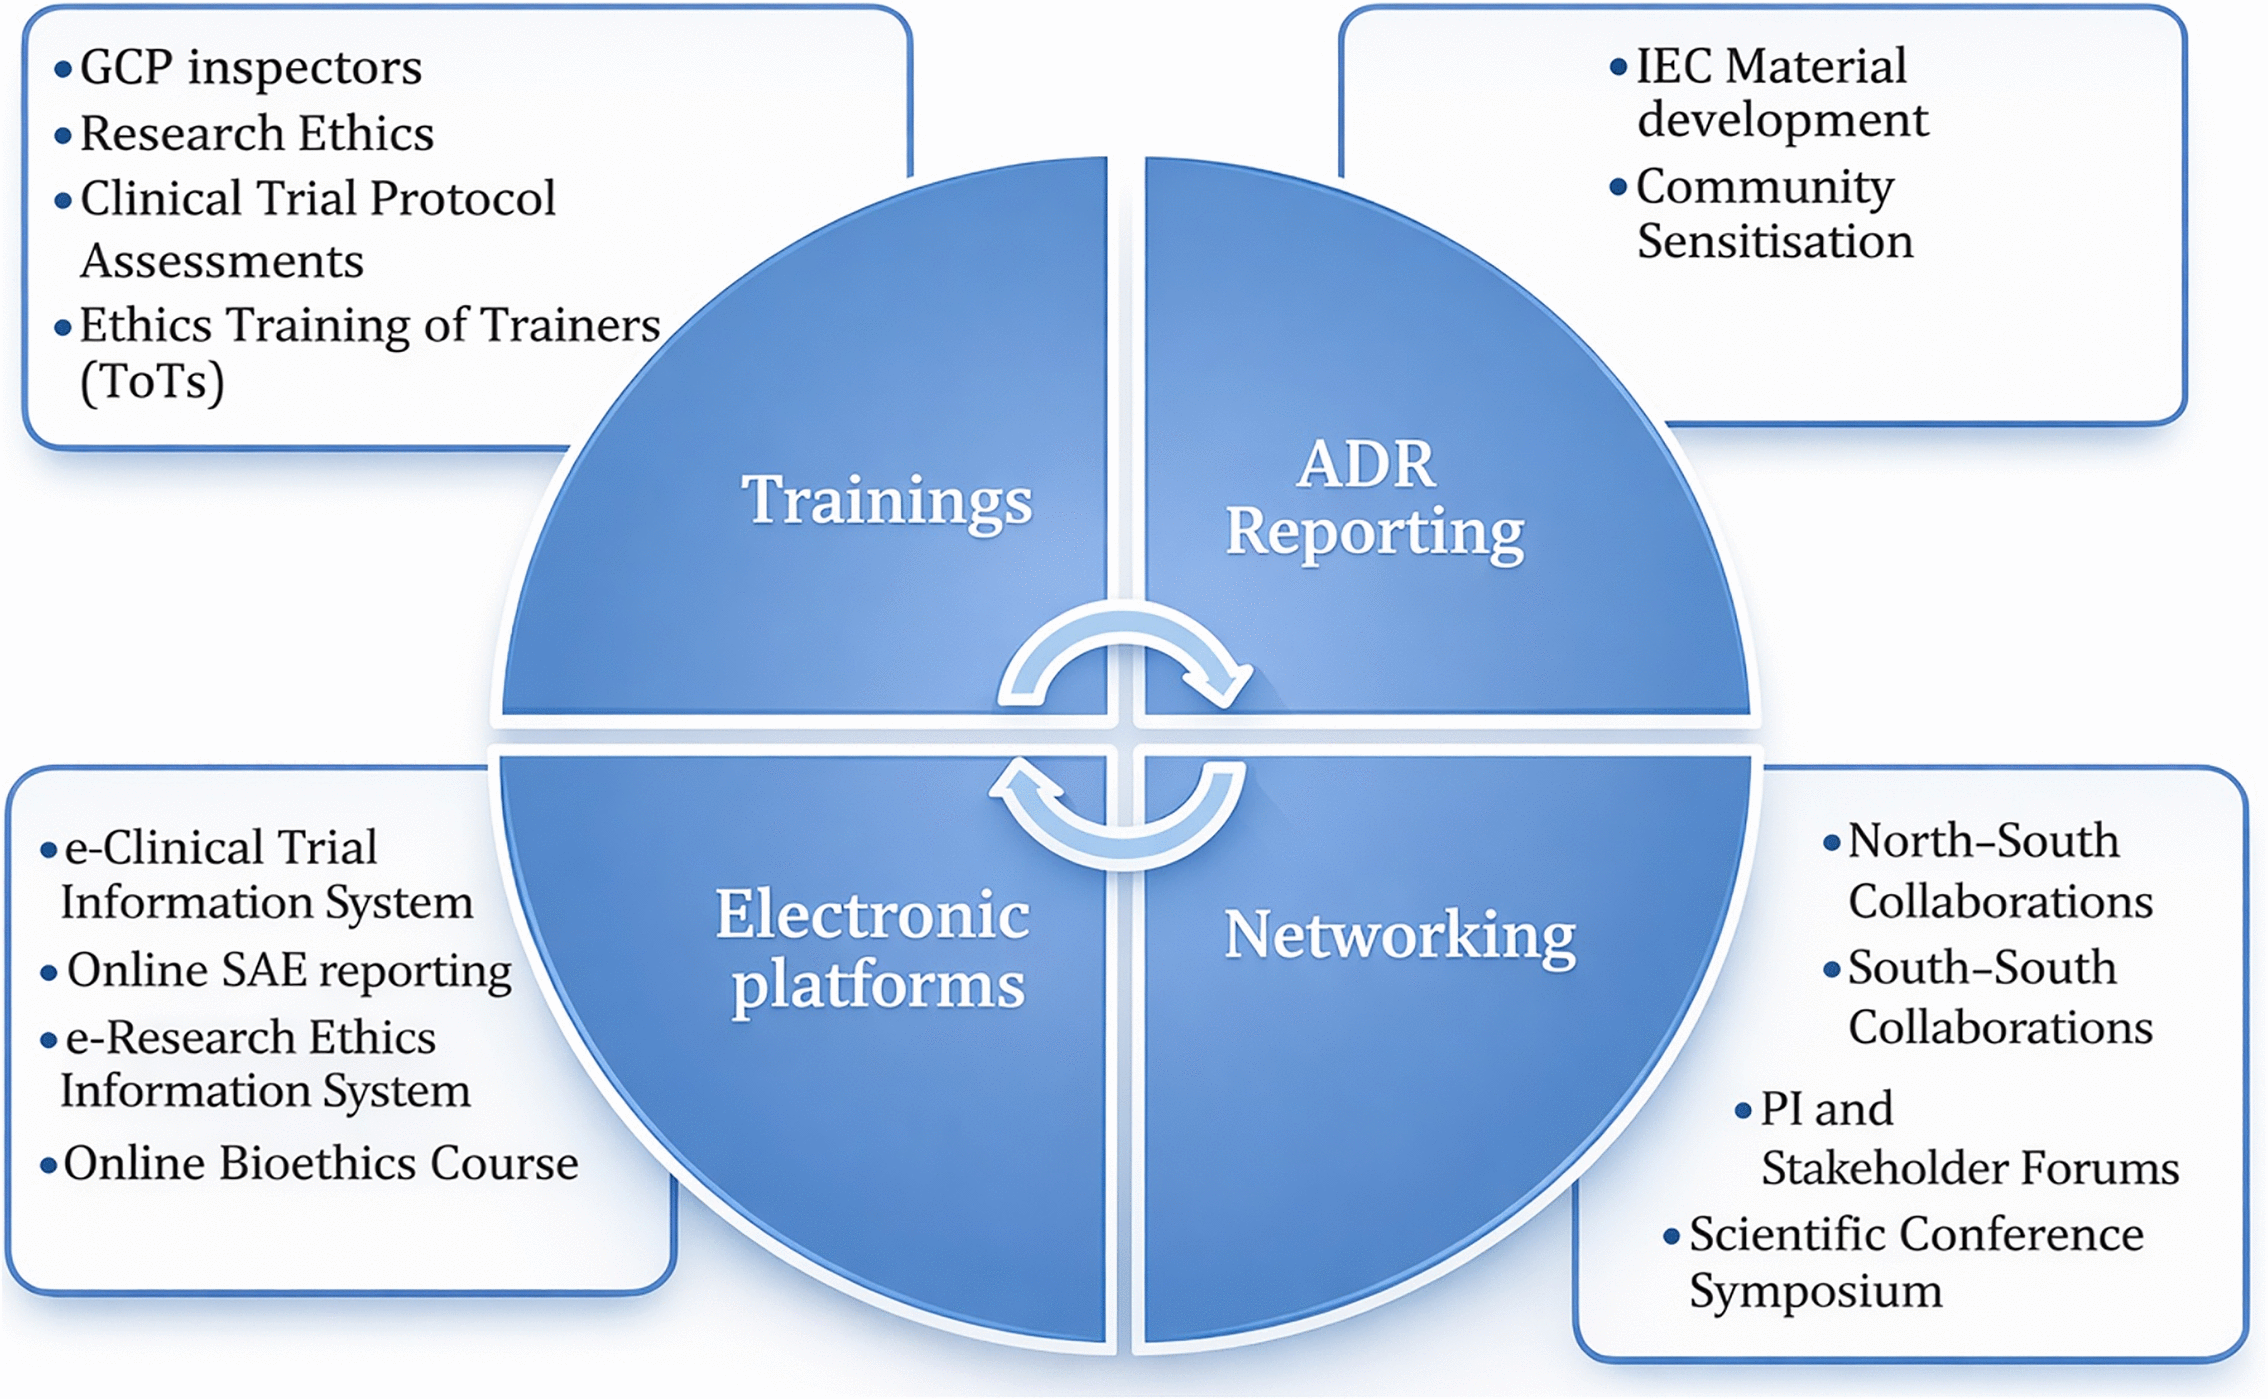
Figure 1. Core components of the ASCEND Project capacity-building interventions.
The figure illustrates the multi-component implementation approach of the ASCEND project, including training, digital systems development, community engagement for pharmacovigilance, guideline domestication, and stakeholder networking across Tanzania Mainland and Zanzibar.
The project was coordinated by the Tanzania Medicines and Medical Devices Authority (TMDA) and overseen by a steering committee chaired by the TMDA Director General, comprising one member from each partner institution, with a secretariat based at TMDA. Implementation was organized in seven work packages led according to institutional mandate. TMDA led the assessment of capacity needs and the domestication of AVAREF guidance, pharmacovigilance community engagement, networking, and project management. The National Institute for Medical Research (NIMR) led the electronic systems for ethics and pharmacovigilance. The Muhimbili University of Health and Allied Sciences (MUHAS), with the Kilimanjaro Clinical Research Institute (KCRI), led training, and the Zanzibar Health Research Institute (ZAHRI), with the Zanzibar Food and Drug Authority (ZFDA), led capacity building in Zanzibar. The University of St Andrews supported networking and doctoral supervision. Within this structure, regulatory approval of clinical trials is the mandate of TMDA in Tanzania Mainland and ZFDA in Zanzibar, while ethics review is overseen by NIMR, through the National Health Research Ethics Committee (NatHREC), and by ZAHRI, respectively.
ASCEND built on the earlier EDCTP-funded Streamlining Health Research Ethics and Medicines Regulation in Tanzania (SMERT) project, under which an electronic research ethics review system, an adverse drug reaction reporting system, and a bioethics curriculum had been developed. ASCEND operationalized, upgraded, and customized these resources and extended their use to Zanzibar.
No primary qualitative data, such as interviews, focus group discussions, or direct observations, were collected for the purposes of this study. We conducted a document-based case study using routine ASCEND project documentation generated by the implementing institutions during the project period. Documents reviewed included approved training curricula and materials, participant registers and attendance lists, training and mentorship reports, records of guideline domestication, including adopted guidance documents, assessment templates, and inspection checklists, consortium deliverables and reports submitted to EDCTP2, steering committee minutes, the end-term evaluation report, stakeholder forum reports, and digital system documentation such as system linkage and user acceptance testing reports, a system user manual, a user survey report, and records of system use where available. We included only documents produced between November 2020 and December 2023 that were directly related to ASCEND implementation. Documentation completeness was assessed by confirming that each major implementation component and planned deliverable had corresponding records. Where records were incomplete, we reported outputs conservatively. Output counts were verified by triangulating figures across at least two sources where possible and prioritizing signed registers, institutional logs, and the most contemporaneous implementation records. Where discrepancies were identified, they were reconciled using the most complete and contemporaneous records, with consultation with the relevant implementing institution when needed.
Training package development and delivery
Training activities were designed to strengthen competencies in clinical trial protocol assessment, Good Clinical Practice inspection, and research ethics review. A structured curriculum development process was used, including drafting of training content, review by subject matter experts, and validation steps to ensure relevance to national processes, alignment with international standards, and AVAREF guidance. The clinical trial assessment and Good Clinical Practice (GCP) inspection courses were designed from a training needs assessment of clinical trial assessors and ethics reviewers conducted in 202114 and were accredited by MUHAS as 70-hour (7-credit) short courses. Delivery combined classroom-based sessions, hands-on practice, mentorship, and a train-the-trainer approach for institutional ethics committees.
Digital systems for ethics review and safety reporting
Digital tools were operationalized, upgraded, or customized to support consistent workflows for ethics review and safety reporting, building on the systems developed under the SMERT project. Implementation included requirement definition with end users, tailoring of system modules, user testing, and integration into institutional workflows. Requirement definition and testing involved information and communication technology (ICT) and technical staff from the participating institutions representing ethics review, pharmacovigilance, and regulatory functions. User feedback informed system refinement: a user survey of the Research Ethics Information Management System (REIMS), conducted by NIMR in June 2021, identified priorities for the system upgrade, and the linkage between the ZFDA and ZAHRI systems underwent structured user acceptance testing against predefined test cases, with sign-off by both institutions, before going live in December 2023.
End-user training was conducted to support adoption, including for serious adverse event reporting and clinical trial application submission and review processes.
Community engagement for pharmacovigilance
Community engagement drew on a community engagement model in pharmacovigilance and was implemented through district and regional sensitization activities. The Pharmacovigilance Community Engagement Model (PCEM), developed by TMDA with partner experts in July 2023 and subsequently issued as a TMDA guideline, is a structured approach that identifies priority community stakeholder groups, selects appropriate communication channels, and links sensitization activities to clear reporting pathways for suspected adverse drug reactions and adverse events following immunization. The model was applied using multiple approaches during community sensitization activities, with the aim of increasing awareness and reducing fear related to reporting. The model was piloted in Dar es Salaam and Dodoma regions and was also applied in Unguja and Pemba, where it was adapted to reach health sciences students, community pharmacists, and the general public through radio and television. The full PCEM document is openly available (Extended data).15
Engagement aimed to increase public understanding of rights and responsibilities in research participation and to promote the reporting of adverse drug reactions and adverse events following immunization. Multiple communication channels were used to reach the community members and relevant local stakeholders.
Capacity strengthening in Zanzibar
A dedicated set of activities supported capacity strengthening for the Zanzibar Health Research Institute and Zanzibar Food and Drug Authority, including train-the-trainer courses, facilitated access to online ethics training resources, implementation of electronic systems for ethics review and serious adverse event reporting, and mentorship linkages with mainland institutions. This approach aimed to support both skill acquisition and institutionalization of processes.
Domestication of AVAREF guidance
The project supported the domestication of AVAREF guidance to harmonize ethical and regulatory review processes for clinical trials conducted in Tanzania Mainland and Zanzibar. Implementation included orientation for selected principal investigators and review and alignment of relevant guidelines, assessment templates, and inspection checklists within participating institutions.
Networking and stakeholder engagement
Networking activities convened forums for institutional review boards, national ethics committees, clinical trials and pharmacovigilance committees. Forums supported dialogue between researchers and regulators, promoted a shared understanding of requirements, and identified coordination improvements that could be implemented within existing mandates.
Ethics
Ethics clearance was obtained from ZAHRI under reference number ZAHREC/03/APRIL/2021/05. For the Tanzania Mainland, ethics clearance was obtained from NIMR under the reference number NIMR/HQ/R.8 a/vol. IX/3666.
This manuscript is a case study based on project documentation and does not report additional human participant data collection or post-project follow-up beyond the activities implemented during the ASCEND project period.
Results
Training outputs for protocol review, inspection, and ethics capacity development
Training materials for clinical trial protocol assessment and Good Clinical Practice inspection were developed and used to deliver capacity development activities for regulators and ethics reviewers. Thirty clinical trial protocol reviewers or assessors and 25 Good Clinical Practice inspectors were trained on international standards and AVAREF guidance. Three Zanzibar Food and Drug Authority inspectors received on-the-job exposure by participating in inspections at five clinical trial sites on Tanzania Mainland. The clinical trial assessment course was designed from a training needs assessment in which 90 of 128 targeted clinical trial assessors and ethics reviewers (70.3%) responded; the proportions rating themselves proficient were 20.0% for clinical, 8.4% for quality, and 10.7% for statistical assessment, and more than 90% reported a critical need for training in each area. Pre- and post-training tests of the assessor cohort showed that mean scores increased from 61 to 80 out of 100 (mean difference 18.96; 95% confidence interval 13.15–24.76; p < 0.0005).14 Learning outcomes were not assessed for the GCP inspector cohort.
Nineteen early- and mid-career researchers were trained in research ethics and clinical trial-related guidelines, application processes, and compliance. Fifty trainers drawn from institutional ethics committees were trained on research bioethics and clinical trial topics to support dissemination within institutional review structures in Tanzania Mainland and Zanzibar. A 40-hour (4-credit) bioethics short course was digitized and accredited by the Medical Council of Tanganyika for 20 continuing professional development (CPD) points.
Digital systems outputs
An online serious adverse event reporting module was operationalized within the national medicines regulatory authority online pharmacovigilance reporting system. Thirty-nine users, including scientists and research administrators, were trained to use this module. By August 2023, 112 serious adverse event reports had been submitted through the module. Zanzibar institutions customized and adopted electronic systems developed by sister institutions in Tanzania Mainland. These figures reflect the users reached during the project period for initial system operationalization and rollout, and do not represent full coverage of all potential end users nationally.
Community pharmacovigilance engagement outputs
The Pharmacovigilance Community Engagement Model was developed for use in Tanzania Mainland and Zanzibar. Sensitization activities using the model reached at least 718 people (218 in Tanzania Mainland and 500 in Zanzibar), as recorded in the project final report, focusing on adverse drug reaction reporting and adverse events following immunization reporting.
Networking outputs
The project convened two stakeholder forums and one principal investigator forum and organized a scientific symposium during the NIMR Annual Joint Scientific Conference 2022, chaired by the Chief Medical Officer from the Ministry of Health. Consortium visits to the Uppsala Monitoring Centre and Uppsala University supported exposure to pharmacovigilance system operations and contributed to networking activities.
Table 1 summarises, for each project component, the capacity gap addressed, the documented outputs, early adoption indicators, outcomes not measured, and proposed metrics for future evaluation.
Early adoption indicators were available for selected digital systems at project close. In Zanzibar, operationalization of the ZAHRI and ZFDA systems enabled receipt, review, and approval processes, and by project close, the system had been used to receive two protocols for review leading to approval. In addition, electronic submission workflows were linked between NIMR and TMDA, and between ZAHRI and ZFDA, establishing an operational pathway for digital submission and review intended to strengthen routine regulatory processes. Sustainability-linked adoption was also supported through the institutionalization of training resources, including accreditation of the Bioethics CPD course and availability of the online course on the KCMC University online learning platform in Moshi, Tanzania.
Table 1.
Project components, documented outputs, early adoption indicators, outcomes not measured, and proposed future evaluation metrics, ASCEND Project (2020–2023).
This table summarises, for each component of the ASCEND project implemented in Tanzania Mainland and Zanzibar between November 2020 and December 2023, the capacity gap addressed, the documented outputs, early adoption indicators, outcomes that were not measured within the project, and proposed metrics for future evaluation.
| Component (capacity gap addressed) | Documented output | Early adoption indicator |
Not measured within the project | Proposed future metric |
|---|
| Clinical trial protocol assessment training (limited protocol review capacity) | Accredited 70-hour (7-credit) course; 30 assessors trained | Mean test score increased from 61 to 80 out of 100 after training14 | Application of skills in routine reviews; review quality | Follow-up assessment of review quality and consistency |
| GCP inspection training (limited inspection capacity) | Accredited 70-hour (7-credit) course; 25 inspectors trained; three ZFDA inspectors joined inspections at five trial sites | ZFDA inspectors participated in TMDA-led inspections | Learning outcomes; inspection quality | Pre- and post-training tests; review of inspection reports; number of inspections led |
| Ethics training of trainers (limited ethics review capacity in institutional committees) | 50 trainers from institutional ethics committees trained | Not documented | Learning outcomes; onward training delivered | Number of onward trainings and trainees; pre- and post-training tests |
| Early- and mid-career researcher training (limited awareness of clinical trial requirements) | 19 researchers trained | Not documented | Learning outcomes; quality of applications submitted | Proportion of applications complete at first submission |
| Digitized bioethics course (limited access to ethics training) | 40-hour (4-credit) course accredited for 20 CPD points | Course available on the KCMC University online platform | Enrolment and completion | Enrolment, completion, and assessment scores |
| Serious adverse event reporting module (paper-based safety reporting) | Module operationalized; 39 users trained | 112 reports submitted by August 2023 | Completeness and timeliness of reports | Proportion of reports complete and submitted within required timelines |
| Electronic submission systems and linkages (fragmented ethics and regulatory workflows) | NIMR-TMDA linkage operational (October 2023); ZAHRI and ZFDA systems operationalized and linked (December 2023) | Two protocols processed through the Zanzibar system; user acceptance testing passed | Review turnaround times; user uptake | Time to acknowledgement and time to decision from system records |
| Pharmacovigilance Community Engagement Model (limited community awareness of safety reporting) | Model developed and issued as a TMDA guideline; at least 718 people sensitized | Model applied in Dar es Salaam, Dodoma, Unguja, and Pemba | Change in community awareness and reporting | Community adverse event reports before and after sensitization; awareness surveys |
| AVAREF domestication (limited harmonization of review processes) | Guidance documents, assessment templates, and inspection checklists adopted by TMDA and ZFDA | Documents in use at TMDA and ZFDA at project close | Consistency of reviews with adopted guidance | Audit of completed reviews against adopted templates |
| Networking (limited dialogue among researchers, ethics committees, and regulators) | Two stakeholder forums, one principal investigator forum, and a scientific symposium; study visits to Uppsala and St Andrews | Recommendations recorded at forums | Implementation of forum recommendations | Tracking of recommendations implemented |
User and stakeholder feedback recorded in project documentation
Project documentation recorded feedback from system users and stakeholders. In the REIMS user survey (June 2021; 19 respondents), most users were satisfied with ease of use (89.5%), first-time registration (84.2%), and form submission (84.2%), whereas satisfaction was lower for responding to reviewer comments (63.2%) and tracking application progress (55.6%). Users requested progress tracking, automated alerts when reviewer comments were posted, the ability to save draft applications, and linkage with other institutional review boards. Similar requests were raised at the principal investigator forum in July 2022, where participants also proposed a shorter version of the national research ethics guidelines and delegation of some reviews to NIMR research centers. Participants at a forum for regional and district medical officers in December 2023 reported unclear roles for regional health authorities in clinical trial oversight and the absence of formal communication channels with NIMR and TMDA. During community sensitization, participants cited fear of reporting, medicine information available mainly in English, and limited feedback after reporting as barriers to adverse event reporting.
Discussion
This case study documents the implementation of a multi-component capacity development initiative for research ethics oversight, clinical trial regulation, and pharmacovigilance in Tanzania Mainland and Zanzibar. The project combined training, digital tools, community engagement, and structured forums for engagement between the researchers and regulators.
Operational achievements included the delivery of training packages and trainer cohorts within institutional ethics committees, implementation of electronic workflows for ethics review and safety reporting, and development of a community engagement model for pharmacovigilance. These outputs reflect institutional ownership by anchoring activities within mandated institutions and using the internal technical capacity for system development and maintenance.10
Implementation considerations included sustainability planning for staff turnover, continued demand for refresher training, and routine budgeting for stakeholder engagement forums.11 The adoption of digital tools depends on user onboarding, clarity of roles, and maintaining data confidentiality through appropriate hosting, access control, and governance arrangements.10 Recent pharmacovigilance capacity-building efforts in East Africa, such as the PROFORMA project (focused on Ethiopia, Kenya, Rwanda, and Tanzania) have similarly emphasized short-term training, cascade models, and integration with national systems to achieve sustainable knowledge development and post-marketing surveillance.9 Likewise, the PAVIA project (2018-2023) demonstrated that blended e-learning and collaborative "triangle" models (linking regulators, public health programs, and research institutions) can lead to significant increases in adverse event reporting and knowledge gains in Tanzania and other countries, highlighting the value of structured, multi-stakeholder approaches, like those in ASCEND.8
After the grant ended, the electronic systems remained hosted on institutional servers and maintained by in-house ICT staff, with operating costs met through institutional budgets and the fees paid for ethical clearance and regulatory review. The accredited courses remain available through MUHAS and the KCMC University online platform as continuing professional development offerings, and the PCEM has been issued as a TMDA guideline. A lesson from ASCEND is that sustainability arrangements, including hosting, user support, and refresher training, and the indicators needed to monitor them, are best agreed at the design stage rather than at project close.
Implementation occurred in a context with established institutional mandates for clinical trial oversight and ethics review in both Tanzania Mainland and Zanzibar, which enabled the rapid integration of training and digital tools into existing workflows. An enabling factor was the presence and active role of the TMDA-MUHAS Regional Centre of Regulatory Excellence (RCORE) as a platform for developing and delivering training packages for assessors and inspectors, supporting institutionalization beyond single workshops.
The project also benefitted from the deliberate linkage of electronic submission systems between Mainland and Zanzibar institutions, supporting integration into routine processes rather than standalone project tools.
The resource requirements for similar initiatives include dedicated technical personnel for system development and maintenance, training design and delivery capacity, and coordination time across institutions. Implementation required adaptation to risks, including system compatibility, COVID-19-related disruptions, and the time required for institutional approval of system linkages, addressed by reviewing existing systems before linkage, involving IT experts, and using hybrid or virtual meeting modalities, where needed.
Transferability to other settings is more likely when enabling conditions are present, including clear institutional mandates for ethics and regulatory functions, willingness to align with regional harmonization mechanisms such as AVAREF, and availability of technical teams able to support the development and maintenance of electronic systems.5,12 Differences in the legal frameworks, staffing patterns, and resource availability should be considered when adopting this approach. Elements likely to be transferable include designing training from a formal needs assessment and accrediting it within existing institutions, linking ethics and regulatory submission systems so that each body can view the other’s decisions, and using a structured community engagement model with defined stakeholder groups and reporting pathways. The adaptation of the model in Zanzibar, where it was extended to health sciences students, community pharmacists, and mass media, illustrates this flexibility. Other enabling conditions were specific to the Tanzanian context, including the parallel regulatory and ethics mandates in Tanzania Mainland and Zanzibar, the electronic systems already developed under the SMERT project, and the established TMDA-MUHAS RCORE. These developments underscore the importance of building national projects to advance regional reliance and sustainability in pharmacovigilance and clinical trial oversight.13
This manuscript is limited to project documentation and project period outputs, and does not evaluate post-project outcomes, long-term effectiveness, or downstream impacts on review timelines or inspection performance. Learning outcomes were measured only for the clinical trial protocol assessor cohort; they were not assessed for the GCP inspector, ethics trainer, and researcher cohorts, and no follow-up assessment of the application of skills was undertaken. The REIMS user survey preceded the system upgrade, and no follow-up survey was conducted. Review turnaround times were not assessed as part of this project. The project’s monitoring framework was designed to track deliverable completion rather than regulatory performance indicators, and the electronic linkages between ethics and regulatory systems became operational only in the final quarter of implementation (October and December 2023), leaving no period within the project for before-and-after comparison. Stakeholders at the final project forum reported that approval delays had reduced but persisted; this perception was not verified against system data. Future capacity-building projects should define performance indicators, such as time to acknowledgement and time to decision, at baseline and plan for their extraction from electronic systems, and future work could build on this documentation through formal evaluation designs that measure sustained system performance and use of pharmacovigilance reporting over time.13
Conclusion
The ASCEND project implemented a coordinated set of activities to support research ethics oversight, clinical trial regulations, and pharmacovigilance in Tanzania Mainland and Zanzibar from 2020 to 2023. Documented outputs include trained reviewer and inspector cohorts, with measured knowledge gains among protocol assessors, operational electronic systems for ethics and safety reporting workflows, a Pharmacovigilance Community Engagement Model issued as a national guideline, and structured forums that supported interactions between researchers and regulators.
By documenting the implementation approaches and outputs, this case study provides practical information that may assist institutions in planning similar capacity development initiatives. The conclusions are limited to activities and outputs achieved within the project period and do not include post-project follow-ups.
Acknowledgements
We extend our heartfelt gratitude to the European & Developing Countries Clinical Trials Partnership (EDCTP) for their unwavering support and generous funding that made this project possible. We would like to express our sincere appreciation to all the trainers who played a pivotal role throughout the course of this project. We also extend our thanks to the administrative staff who provided essential logistical support, ensuring the seamless execution of the project. Furthermore, we acknowledge the crucial role played by IT developers Mr. John Maboko, Mr. Peter Agrea, and Mr. Ambele Mwafula, who supported the development and operationalization of online systems.
Data availability
Underlying data
The data underlying this article consist of internal ASCEND project documentation, including activity and deliverable reports, steering committee minutes, system reports, and training registers, held by the participating regulatory, ethics, and academic institutions in Tanzania Mainland and Zanzibar. Training registers and attendance lists contain personal data and cannot be shared. Activity and deliverable reports, the end-term evaluation report, and the REIMS user survey report are available on reasonable request to the corresponding author, subject to approval by the relevant institution. No additional human participant data were collected for this case study.
Extended data
Zenodo: Pharmacovigilance Community Engagement Model to Advance the Reporting of Adverse Events in Tanzania (TMDA/DMC/CTP/G/013). Tanzania Medicines and Medical Devices Authority, First Edition, 2023. https://doi.org/10.5281/zenodo.22975959. The document is openly accessible. Copyright is retained by TMDA, and reuse is subject to the terms stated on the Zenodo record.
Other project materials
The training needs assessment questionnaire and the pre- and post-training test for the clinical trial assessment course are available as supplementary files to the published training study.14 The digitized bioethics course is available on the KCMC University online learning platform (https://eboard.kcmuco.ac.tz). The accredited curricula for the clinical trial assessment and GCP inspection courses, held by MUHAS, and the domesticated AVAREF guidance documents, assessment templates, and inspection checklists, held by TMDA and ZFDA, are available on reasonable request, subject to institutional approval.
References
- 1.
Chaudhry I, Thurtle V, Foday E, et al.:Strengthening ethics committees for health-related research in sub-Saharan Africa: a scoping review.
BMJ Open.
2022; 12(11):e062847. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 2.
Cavaleri M, de Sousa CMA , Hacker A, et al.:A roadmap for fostering timely regulatory and ethics approvals of international clinical trials in support of global health research systems. Lancet Glob.
Health.
2025; 13(4):e769–e777. PubMed Abstract
| Publisher Full Text
- 3.
Amboka P, Kurui D, Wamukoya M, et al.:A landscape analysis of clinical trials and infant clinical trials in Kenya, Ethiopia, and Nigeria.
Front Epidemiol.
2024; 4:1417419. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 4.
Access to Medicine Foundation: Access to Medicine Index 2024.2024. Reference Source
- 5.
Akanmori B, Mukanga D, Bellah A, et al.:The Role of the African Vaccine Regulatory Forum (AVAREF) in the accelerated clinical evaluation of Ebola vaccine candidates during the large West Africa epidemic.
J Immunol Sci.
2018; 2(SI1):75–79. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 6.
Ncube BM, Dube A, Ward K:Establishment of the African Medicines Agency: progress, challenges and regulatory readiness.
J Pharm Policy Pract.
2021; 14(1):29. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 7.
Ndomondo-Sigonda M, Azatyan S, Doerr P, et al.:Best practices in the African Medicines Regulatory Harmonization initiative: perspectives of regulators and medicines manufacturers. PLOS Glob.
Public Health.
2023; 3(4):e0001651. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 8.
Schievano F, Mwamwitwa KW, Kisenge S, et al.:Development, assessment and educational impact of a blended e-learning training program on pharmacovigilance implemented in four African countries.
Front Med (Lausanne).
2024; 11:1347317. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 9.
van Puijenbroek E , Barry A, Khaemba C, et al.:Short-term training, a useful approach for sustainable pharmacovigilance knowledge development in Tanzania, Kenya, Ethiopia and Rwanda.
Drug Saf.
2024; 47(12):1193–1202. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 10.
Fimbo A, Mwalwisi YH, Matiko D, et al.:Lessons from enriching Tanzania’s clinical research ethics clinical trials oversight and pharmacovigilance through the ASCEND project.
Discover Public Health.
2024; 21(1):54. Publisher Full Text
- 11.
Fimbo AM, Sillo HB, Nkayamba A, et al.:Strengthening regulation for medical products in Tanzania: an assessment of regulatory capacity development, 1978– 2020.
PLOS Glob Public Health.
2024; 4(10):e0003241. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 12.
Abdulwahab AA, Okafor UG, Adesuyi DS, et al.:The African Medicines Agency and medicines regulation: progress, challenges, and recommendations.
Health Care Sci.
2024; 3(5):350–359. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 13.
Ndagije HB, Ampaire S, Sabblah GT, et al.:Advancing pharmacovigilance practice in Africa: moving from data collection to data-driven decision making—report from the 4th ISoP Africa chapter meeting.
Drug Saf.
2026; 49(1):129–135. PubMed Abstract
| Publisher Full Text
| Free Full Text
- 14.
Mwamwitwa KW, Munishi CG, Makoye PM, et al.:Training needs assessment and capacity building of clinical trial assessors and ethical reviewers to strengthen regulatory review in Tanzania.
Ther Innov Regul Sci.
2026; 60:1135–1143. PubMed Abstract
| Publisher Full Text
- 15.
Tanzania Medicines and Medical Devices Authority: Pharmacovigilance Community Engagement Model to Advance the Reporting of Adverse Events in Tanzania (TMDA/DMC/CTP/G/013). First Edition. [Dataset].
Zenodo.
2026. Publisher Full Text







